

Reviewed by Preston Hoang, AI-Lead, Topflight Apps
Updated on October 15th, 2026.
A useful conversational AI system gives a patient an appointment confirmation or helps a caregiver find the right instruction. For patient engagement, building conversational AI for healthcare starts with choosing that job and deciding what happens when the system gets it wrong.
What is conversational AI in healthcare?
Conversational AI in healthcare lets patients and staff use chat or speech to request information and complete defined tasks. A system might answer from approved documents or book an appointment through an authorized API. Its useful scope depends on the data it can access, the actions it can take, and the route to a person when it can’t help.
Key takeaways
- Patient access and staff knowledge retrieval are useful starting points. Give each workflow a defined action boundary and a staffed escalation route.
- Our published planning references start around $60,000 for a hosted-model RAG assistant. A custom pipeline with EHR access and regulated claims has a different scope, at $150,000 to $300,000+.
- Retrieval can ground an answer in approved material. Test unsupported answers and failed handoffs before you give the system patient-facing responsibilities.
Table of contents
- What is conversational AI in healthcare?
- How conversational AI works in 2026: LLMs, RAG, and speech
- Conversational AI use cases in healthcare (with examples)
- Case study: Mi-Life, a RAG assistant for caregivers
- Integrating conversational AI with EHRs and scheduling systems
- Safety, compliance, and risk
- Benefits of conversational AI for healthcare providers and patients
- How to implement conversational AI in healthcare: 8 steps
- How much does conversational AI cost in healthcare?
- How Topflight builds conversational AI for healthcare
- Frequently asked questions
What is conversational AI in healthcare?
The practical difference between healthcare conversational AI systems is how much freedom they have. A healthcare chatbot can follow a fixed decision tree, answer from a knowledge base, or use a language model. Healthcare AI agents can also call tools to carry out an approved task.
Voice describes how someone talks to the system. You can put a voice interface on a rules-based bot or an agent; a spoken conversation tells you little about what the software is authorized to do.
Chatbots, AI agents, and voice interfaces
| System or interface | What it does | Typical use | Build implications |
|---|---|---|---|
| Rules-based chatbot | Follows approved branches and fixed answers | Office hours or routing a request | Maintain the paths and their exceptions |
| LLM assistant | Interprets questions and drafts answers from allowed material | Staff policy lookup | Test retrieval and unsupported answers |
| AI agent | Uses authorized tools within a defined workflow | Checking availability and requesting an appointment change | Control permissions, confirmations and failed transactions |
| Voice interface | Carries a bot or agent conversation through speech | Patient phone calls or hands-free staff queries | Add speech handling and the relevant phone/recording controls |
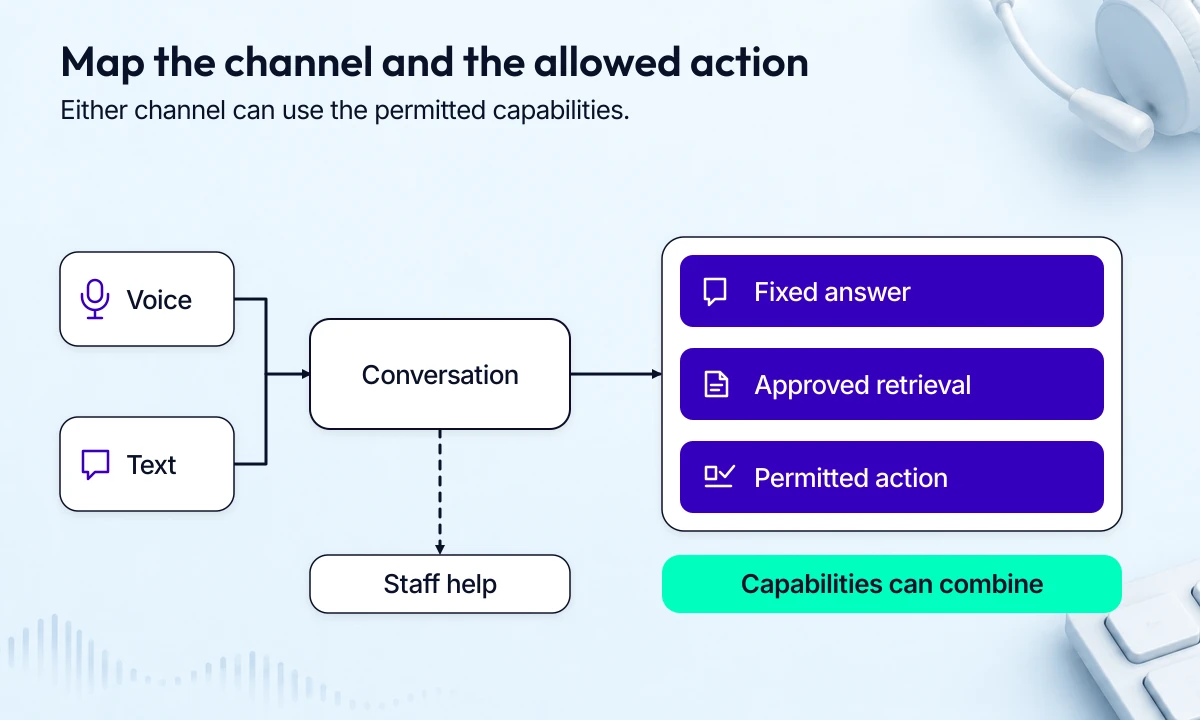
Choose the actions a workflow may take before choosing its conversation channel.
When a rules-based bot is still the right choice
Use fixed paths when the acceptable answers are short and the task has predictable branches. A clinic-hours FAQ is a reasonable example. You can approve every answer and send unexpected requests to staff.
A retrieval assistant earns its extra work when people need to ask varied questions across a large document set. Give an agent permission to take an action only when you can test the transaction and recover from a mistake. Our guide to chatbots in healthcare covers the narrower chatbot use cases.
How conversational AI works in 2026: LLMs, RAG, and speech
Language processing helps software interpret a request and produce a reply. Modern conversational AI for healthcare can combine large language models with document retrieval and tightly controlled access to external tools.
RAG gives large language models source material
With retrieval-augmented generation (RAG), the application finds relevant passages in an approved knowledge base and supplies them to the model with the question. For a caregiver assistant, that might mean retrieving a client’s current care instructions before drafting an answer.
Access rules belong in retrieval. Filter by the signed-in user’s permissions and the correct patient or client before material reaches the model. Keep a source reference and a document version with the answer so staff can check it.
RAG preparation means cleaning documents and testing which passages the system finds. Model training is a separate choice. Changes to the knowledge base still need evaluation, especially when an old policy has been replaced.
Speech recognition needs a fallback for voice agents
A voice conversation adds recognition errors and timing constraints. Test names and medication terms, background noise, interruptions and requests to repeat an answer. A phone workflow also has to cope with silence or a dropped connection.
- Confirm the patient’s identity before exposing patient-specific information.
- Read back a consequential action, such as an appointment change, before submitting it.
- Retain the request context when handing the caller to staff.
- Provide another route when speech recognition repeatedly fails.
Voice input inside a staff app and a patient telephone service need different designs. The telephone version adds call routing and controls specific to the phone service. Budget those components explicitly.
Guardrails need a tested route for human escalation
Give the system a short list of permitted actions, and enforce the workflow’s patient and role checks on every FHIR tool call. A scheduling tool can check an approved calendar; a clinical question outside the service’s scope goes to an appropriate staff queue. Record whether that handoff was accepted so a request can’t disappear between systems.
Test missing information and conflicting records alongside the easy questions. The NIST generative AI profile treats confidently false output as a risk to evaluate and manage. Retrieval and guardrails leave residual error risk.
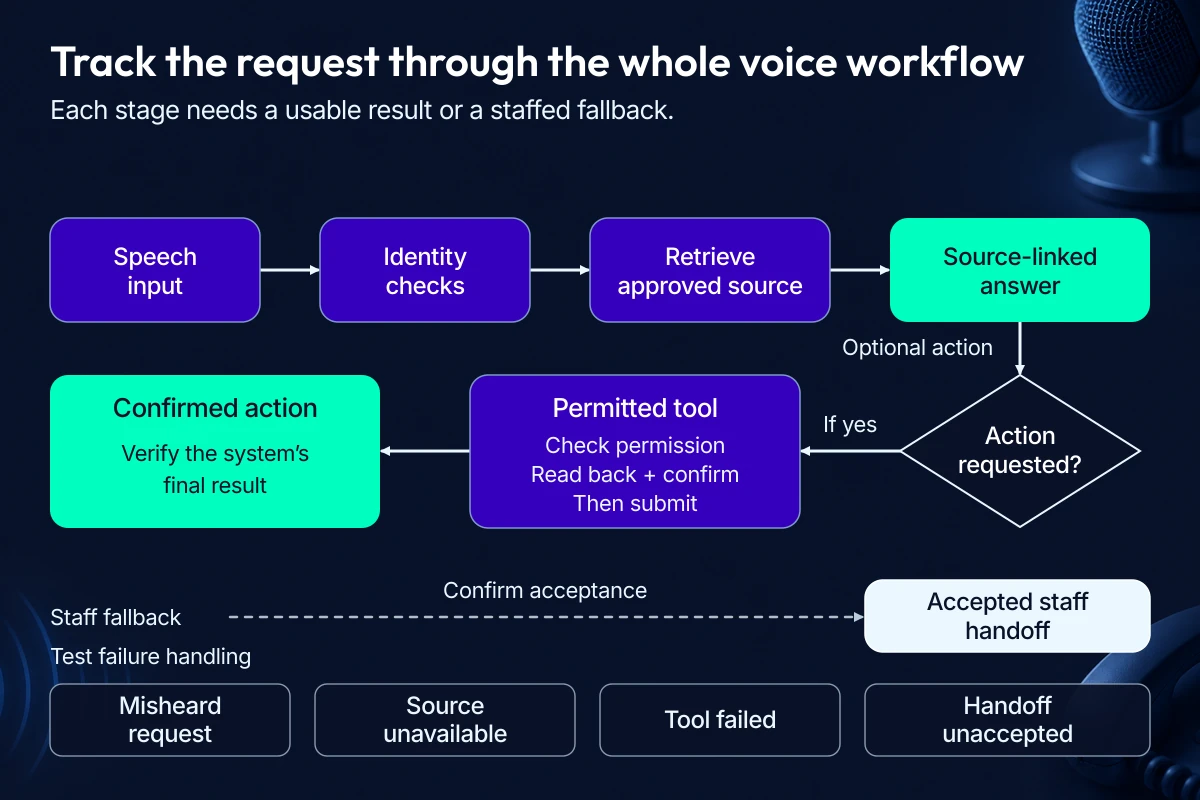
A sourced answer, confirmed action or accepted handoff gives the request a clear outcome.
Related: Generative AI in healthcare: architectures and delivery tradeoffs
Conversational AI use cases in healthcare (with examples)
Start with the work a patient or staff member is trying to finish. Conversational AI in healthcare is easier to evaluate when each use case has a measurable completion point and an owner for exceptions. For patient engagement, measure whether the person reaches the next step, including staff help when needed.
Patient access and appointment scheduling end with confirmation
In appointment scheduling, a patient asks to move an appointment. The system verifies identity, checks the permitted scheduling system and presents available slots. After the patient confirms a choice, it submits the change and returns the actual booking result.
For appointment scheduling, check the system’s booking result before telling the patient “you’re booked.” Route unavailable appointments and failed writes to the contact center with the conversation attached. For a wider care workflow, see our virtual nurse app guide.
Give intake and pre-visit questionnaires a correction route
Conversational intake can collect information before a visit and flag incomplete responses for staff. Agree which fields enter the record and which require review:
- Reason for the visit
- Current medication list as reported by the patient
- Required consent and contact preferences
- Questions the patient wants to discuss
Show patients what they’ve submitted and give staff a correction route. Our patient intake automation guide covers the workflow in more detail.
Medication reminders and post-discharge follow-up need a clinical owner
Reminders should use the care team’s approved instructions. A follow-up conversation can ask whether someone received those instructions and collect a request for help. Changes in symptoms or questions about dosing need a defined clinical response route.
Specify who receives an escalation and how quickly that queue is monitored. The patient needs clear directions for urgent concerns, including what to do while waiting for a response.
Measure AI patient engagement by the completed task
AI patient engagement can support a specific next step: completing intake, confirming a visit or responding to a follow-up request. Match the channel and timing to the patient’s recorded preferences.
- Measure completed tasks alongside opt-outs and requests for staff help.
- Check contact details and permission before starting an outreach campaign.
AI voice agents in healthcare also need the calling and recording review described in the safety section. A reminder’s clinical purpose doesn’t settle every communication requirement.
Keep sources visible for clinician and caregiver knowledge assistants
A clinician assistant can retrieve approved local guidance or locate a document within a user’s access rights. Put the source beside the response and make the version visible; staff need a way to inspect the underlying instruction.
Our Mi-Life case below concerns caregivers searching client information and policies. Its published scope gives you a concrete example of retrieval within a defined care setting.
Define the crisis boundary for mental health support
XZEVN is a Topflight project using voice or text to support a conversation about a user’s concerns. Keep the product’s clinical claims and crisis boundaries explicit. An app’s conversational tone establishes neither clinical effectiveness nor a reliable assessment of distress.

A mental-health support interface needs an explicit route for urgent concerns.
A mental-health support service needs a defined route to professional or crisis care. Confirm the product’s actual crisis response before relying on it to route urgent requests. For technical build detail, see healthcare chatbot development.
Case study: Mi-Life, a RAG assistant for caregivers
Goldie Floberg’s caregivers had about 1,300 pages of client information, policies and procedures to work through. A new staff member needed the right instructions for the person in their care, with access limited to the records they were allowed to see.
We built Mi-Life for that retrieval task. Topflight’s medical-chatbot development article puts the effort at about 1,100 engineering hours. That figure describes this build’s effort; a calendar timeline needs the staffing and scope behind it.
Client-scoped retrieval limits what reaches the answer
The published Mi-Life case study describes voice and text queries backed by RAG and a vector database. Documents are formatted for retrieval, and metadata filters narrow the source material to the relevant client. When information is unavailable, the assistant returns a fallback answer.
OTP sign-ins and role-based access govern who can retrieve client data. The case also describes de-identification during processing and reinsertion of PHI when needed, with Azure OpenAI and BastionGPT named in the architecture. Assess HIPAA duties and test those controls across the full data path, including logs and retrieved documents.
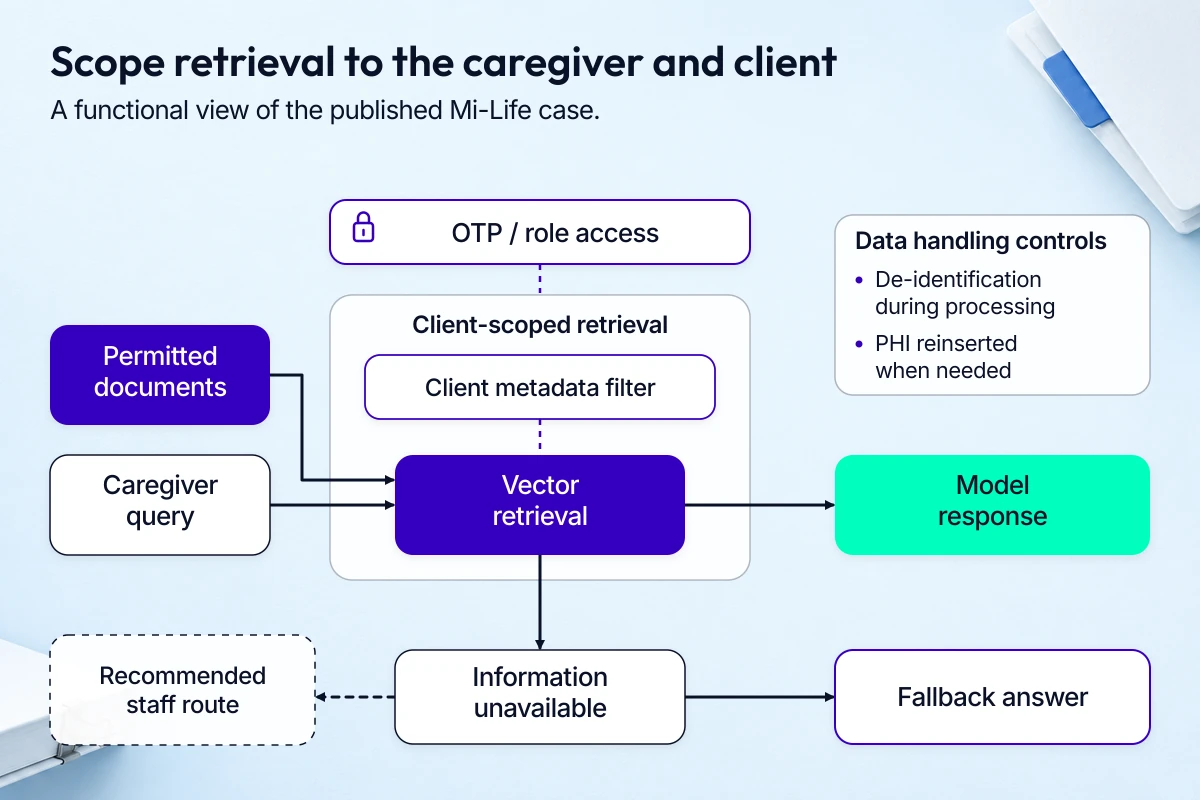
The published case supports scoped retrieval; confirm the deployment’s actual escalation path separately.
Read the reported outcomes with their evidence limits
Topflight’s public case reports a 72% drop in medication errors and staff NPS above 70. The page doesn’t disclose baseline counts, cohort size, measurement period or survey response rate, and it provides no independent validation. Treat these as first-party results from this deployment when assessing whether a caregiver retrieval assistant fits your workflow.
For your pilot, establish the baseline before rollout. Track retrieval errors and staff adoption alongside the workflow outcome you want to change, so you can tell whether the assistant earns its place on a shift.
Integrating conversational AI with EHRs and scheduling systems
An agent can only act through the interfaces your organization can access. Before you scope an EHR integration for appointment booking or chart updates, confirm the vendor’s available endpoints and the permissions your deployment can obtain.
Separate data exchange from permission to act
HL7 integration can connect existing clinical systems, while FHIR APIs expose defined resources. A read-only assistant might retrieve a medication list or prepare medical record summaries for clinician review. Writing to the chart adds a separate authorization and validation requirement.
SMART on FHIR is an established approach to app authorization and launch. The ASTP/ONC standardized API certification criterion references SMART App Launch for the relevant certified Health IT Modules. Your app’s granted scopes and the vendor’s supported operations determine what it can do.
Check access with the actual deployment identity. Confirm production write permission separately from sandbox read access, and keep an audit record for each permitted write.
Appointment scheduling ends with a confirmed system response
Appointment scheduling needs its own workflow contract: patient identity, appointment type, provider availability and the rules for changing an existing booking. Have the patient confirm the proposed slot before the tool submits it.
Read the scheduling system’s result and check booking status before retrying a timed-out request, so an uncertain response doesn’t become 2 appointments. A timeout or rejected request needs a clear status and a staff handoff; the patient must be able to tell whether an appointment exists. Put those failure paths into your healthcare app development scope alongside the successful booking flow.
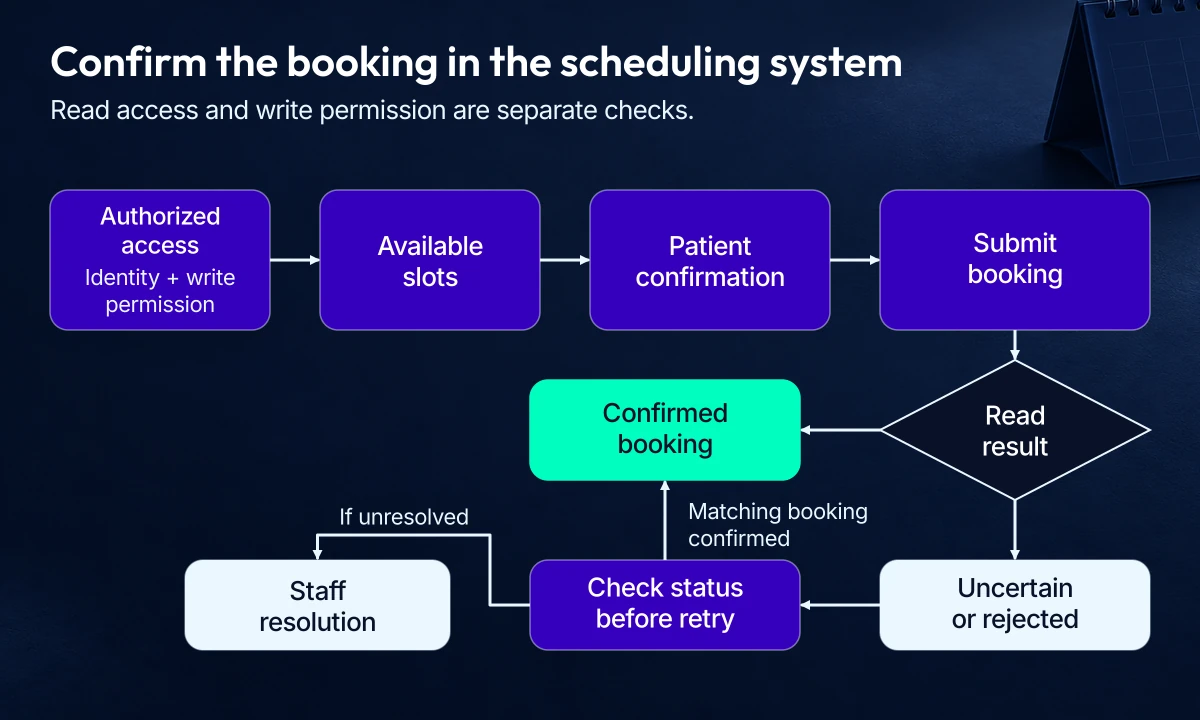
Check the system’s booking status before retrying an uncertain request.
Safety, compliance, and risk
Give every healthcare conversational AI workflow an owner who can pause it. Your healthcare app developers should be able to show where patient data travels and who handles a failed conversation.
HIPAA controls follow the PHI
Map the model, speech, telephony, storage and logging services before signing contracts. Under HHS cloud guidance, business-associate duties depend on what a provider does with ePHI; the transmission-only conduit exception is narrow.
- Put BAAs and the appropriate subcontractor agreements in place where those duties apply.
- Check the covered service and configuration, retention, permitted use, access controls and safeguards.
A signed BAA leaves you with engineering work, including restricted access and protected logs. Review de-identification against the actual data flow and re-identification risk. A cloud provider can have business-associate duties even when it stores encrypted ePHI without holding the decryption key.
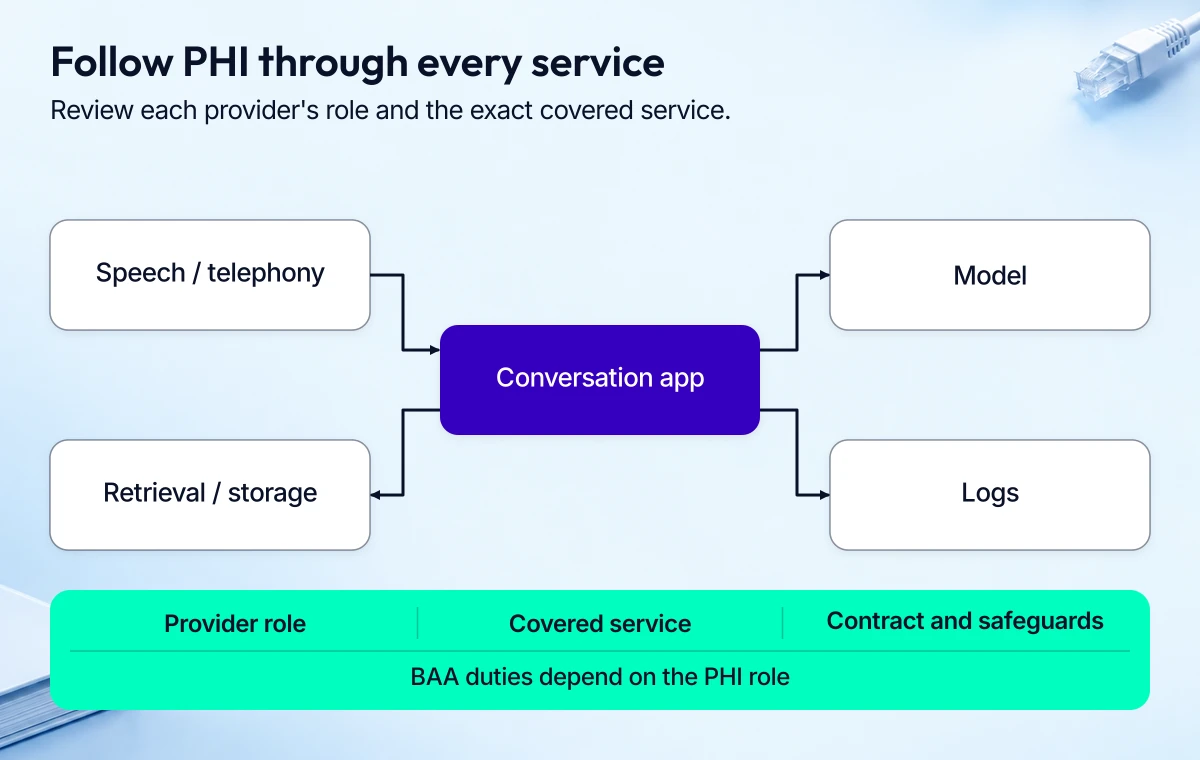
Include logs and subcontracted services when reviewing the PHI path.
Hallucination risk needs an answer policy
RAG can retrieve the wrong passage, and a model can misread the right one. NIST’s Generative AI Profile supports source checking and empirical evaluation of retrieval-grounded answers while recognizing residual error risk.
Set an approved knowledge scope and unknown-answer thresholds. Test citations against the answer they supposedly support, then route unsupported or high-risk requests to staff. Repeat evaluation when documents or model versions change.
Intended use sets the FDA boundary
Review symptom-checking and triage functions before treating them as routine access automation. FDA’s January 29, 2026 CDS guidance describes 4 criteria for the Non-Device CDS exclusion, including recommendations to healthcare professionals who can independently review their basis.
Patient-facing recommendations need their own intended-use assessment. Record the intended users, recommendations, clinical purpose, and basis for review before choosing a development pathway. Our SaMD development guide covers the product work that follows that assessment.
Recording and outbound calls need separate review
Plan separate reviews for recording/transcription, AI disclosure, privacy, and permission to place outbound calls. State rules differ: compare New York’s statute with Florida’s consent exception. Have counsel review the actual jurisdictions and notice flow, with a usable staff handoff.
The FCC treats AI-generated voices as artificial voices under the TCPA. Outbound follow-up needs a campaign-specific consent and exemption review alongside recording review.
Algorithmic bias and fairness need workflow tests
Measure failures across supported languages, accents, accessibility needs, and patient groups. Review:
- Misunderstood requests
- Abandoned conversations
- Repeated staff transfers
- Unequal waits for resolution
An aggregate completion rate can hide a group that repeatedly gets stuck.
After launch, give staff a way to report those patterns, correct the workflow and rerun the affected test cases.
Benefits of conversational AI for healthcare providers and patients
Choose a patient engagement or staff workflow measure before buying a conversational interface. Track repeat calls or the time staff spend searching approved instructions. Check whether patients complete the task and whether the work simply moves to another staff queue.
| Potential benefits for providers | Potential benefits for patients |
|---|---|
|
|
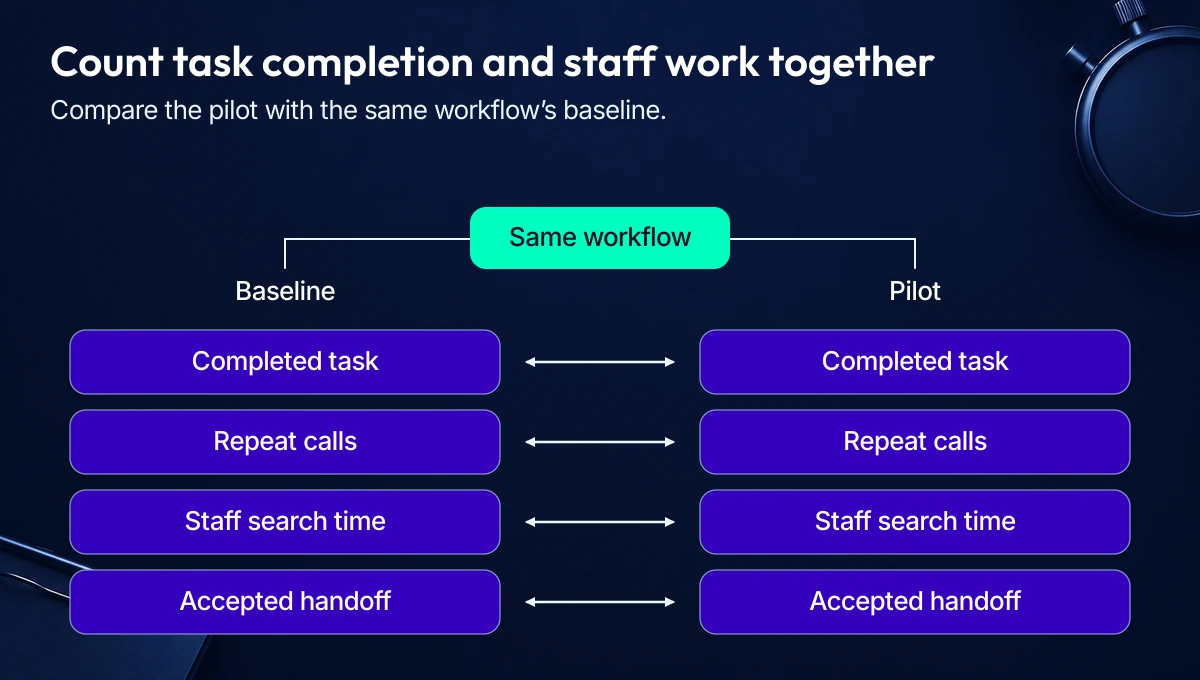
A pilot’s benefit depends on what patients finish and the work staff still have to do.
Availability depends on the service you actually staff and support. A 24-hour interface needs a clear explanation of when a person can respond.
In the Mi-Life deployment above, Topflight reports a 72% medication-error drop and staff NPS above 70. Both figures come from the same first-party case, with the measurement limits described there. Set your own baseline and success threshold for the task you’re deploying.
How to implement conversational AI in healthcare: 8 steps
For patient engagement, follow the workflow from the first request through staff resolution. The implementation sequence should make each release’s permissions and failure paths reviewable.
- Choose the use case and its handoff boundary. Write down the task, authorized users, success measure and situations that require a person. For appointment requests, define when identity is sufficient and who resolves an uncertain match.
- Decide what to buy and what to build. Compare the contract and operating model against 2 questions:
- Can the platform support your PHI flows and required permissions?
- Who owns changes when an EHR API or clinical policy moves?
- Prepare the knowledge source and retrieval rules. Assign document owners, remove obsolete material and scope access to the right patient or role.
Keep a small test set of questions with approved answers and source passages. You’ll use it again after every knowledge update.
- Connect the required systems and prove the permissions in a sandbox:
- Read operations should return only the records the user can access.
- Write operations need explicit authorization and a clear confirmation path.
Test retries and failed confirmations before booking real appointments.
- Evaluate the conversation and its guardrails. Include:
- Questions the source material can’t answer
- Requests outside the agent’s allowed actions
- Ambiguous identities and conflicting records
- Failed tools and staff handoffs
Score answer accuracy separately from action completion. A convincing reply can still conceal a failed booking, so check the system’s final state.
- Review security and vendor coverage. Check BAAs where required, least-privilege access, retention, audit logs and incident responsibilities. Include speech and telephony services in the data-flow review for voice deployments.
- Pilot with staff who own the workflow. Compare task completion and transfers with the existing process. Review a sample of failed requests.
Set launch and rollback thresholds before you see the pilot’s results. Start with a bounded user group and preserve a staffed route while you inspect failures.
- Assign monitoring and change control. Keep a record of the model, prompts, knowledge sources and tool permissions for each release.
- Rerun the relevant evaluation after changes.
- Give an accountable owner the authority to pause the workflow and restore a tested version.
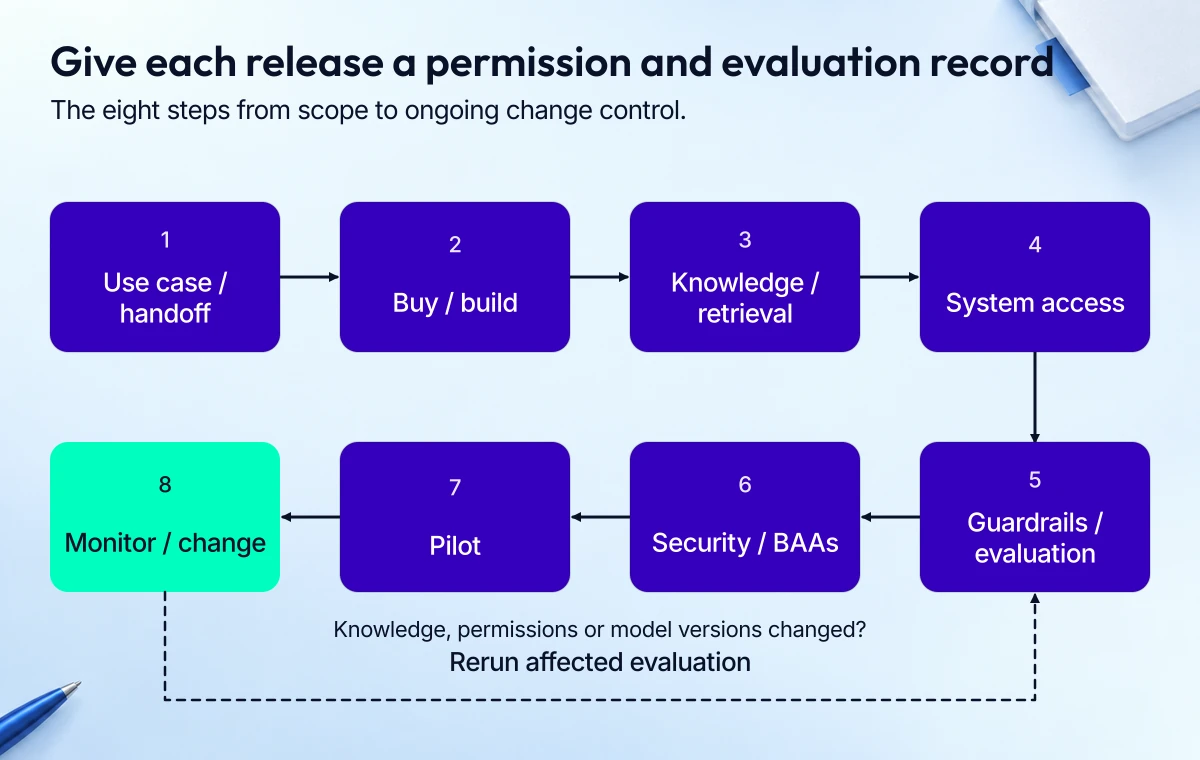
Recheck the affected evaluation cases whenever knowledge, permissions or model versions change.
For the broader operational work around these steps, see our guide to automation in healthcare administration.
How much does conversational AI cost in healthcare?
The cost of conversational AI in healthcare depends on the data it reads and the actions it can take. A public FAQ bot and an EHR-connected voice agent have different delivery scopes.
| Solution scope | Published planning reference | Scope boundary |
|---|---|---|
| Limited public-information rules bot | $10,000 to $15,000 in Topflight’s 2024 chatbot cost guide | Dated comparator for a narrow rules flow; excludes custom PHI, EHR and production voice work. |
| Hosted-model RAG assistant | Starting at about $60,000 in our GenAI healthcare guide | Retrieval over a defined knowledge source using a hosted model. Integration and validation scope still need estimating. |
| Custom pipeline with EHR connections and regulated claims | $150,000 to $300,000+ in the same GenAI guide | Custom data and system connections, with engineering and evidence requirements driven by intended use. |
| EHR-connected voice agent | Scoped estimate required | Telephony, identity checks, scheduling actions and safety validation change the scope. The RAG figures above aren’t a voice-agent quote. |
Use these Topflight references, checked in October 2026, to frame a scoped project estimate. Our broader healthcare app cost guide gives an $80,000 to $300,000+ envelope for whole healthcare apps, which can include much more than the conversation layer.
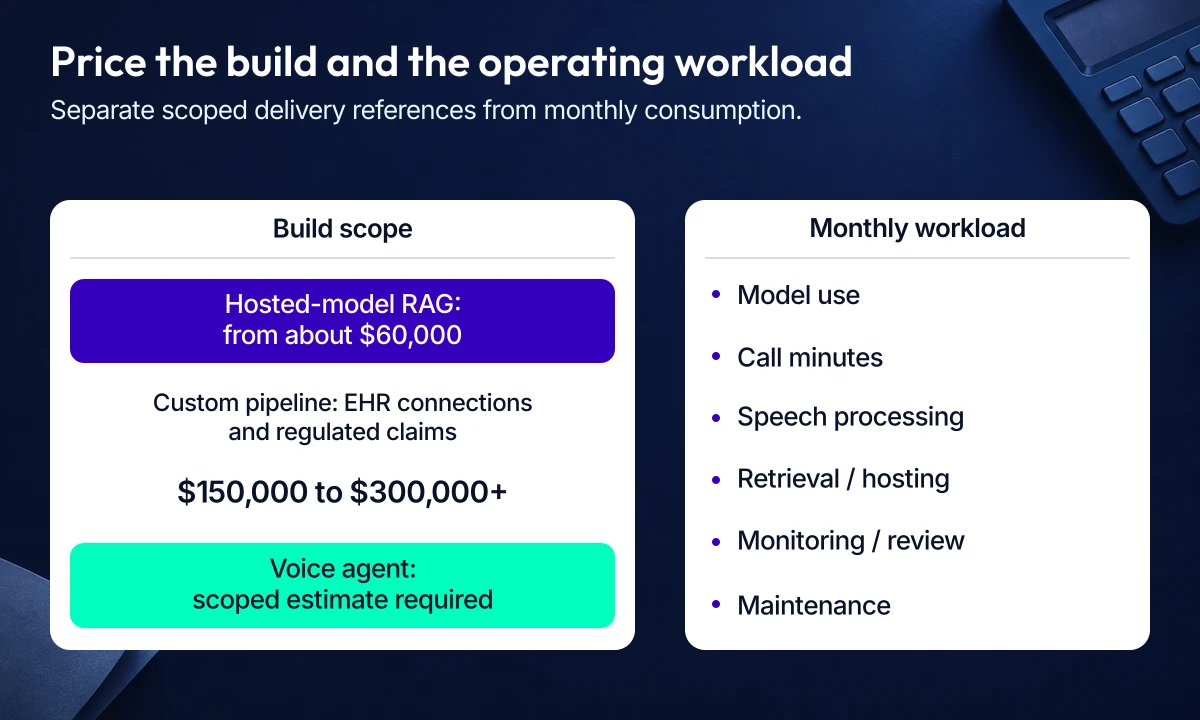
Scope the voice workflow separately and budget its operating workload alongside delivery.
Price the workload after launch
Build a monthly estimate from actual usage:
call minutes × telephony rate + speech usage × speech rates + model usage × model rates + retrieval/hosting + monitoring + human review + maintenance
Separate inbound and outbound call assumptions, and count silence or retries according to each vendor’s billing rules. Model tokens and speech processing can be separate charges; staff review belongs in the operating budget too.
Use the pilot’s measured minutes, tokens and escalation workload to replace assumptions. Check the covered vendor service and current rates before committing to a budget.
Ask for fixed fees and usage charges as separate lines in the estimate. Model the expected traffic and how many calls you’ll handle at once, then account for the vendor’s billing increments. Price a second scenario for higher volume or calls that run longer than the demo.
Choose who owns the changes
A purchased platform can reduce the infrastructure you build, but its contracts and supported interfaces set the workflow’s limits. Check how it handles PHI and how you’ll export your data. Ask what you’ll pay to change an integration.
Custom development gives you control over retrieval and tool permissions, and puts maintenance and evaluation on your team. Choose against the workflow’s requirements and the people available to run it.
How Topflight builds conversational AI for healthcare
Mi-Life shows the work behind a caregiver assistant: document preparation, client-scoped retrieval, a fallback for missing information and access controls. We’ll use that experience to review your source documents and plan access tests.
Start with one patient engagement workflow or staff retrieval task and the systems it touches. To scope an EHR assistant, bring the vendor’s API documentation and the actions you want to permit. For a voice project, bring the call flow and the staff handoff rules so we can estimate the integration and evaluation work.
Talk with Topflight about your conversational AI project to define a pilot, its data boundaries and the evidence you’ll need before expanding it.
[Updated October 2026]
Frequently asked questions
What is conversational AI in healthcare?
Conversational AI for healthcare lets patients and staff use chat or speech to get information or complete a defined task. Define its permissions and the route to staff help before putting it into a care workflow.
What's the difference between a healthcare chatbot and conversational AI?
A healthcare chatbot is one conversational interface; it can use fixed rules, retrieval or a language model. An AI agent also has permission to call specific tools, while voice is a channel that either design can use.
Can AI voice agents handle patient phone calls?
They can support bounded tasks such as appointment requests when identity checks, transaction confirmation and staff handoff are tested. Review the actual calling and recording permissions, including any outbound artificial-voice requirements, for the deployment.
Is conversational AI HIPAA compliant?
The deployment’s data flows and safeguards determine its HIPAA obligations. Check each provider’s role, obtain a business associate agreement where required, and confirm that the particular services and configurations are covered.
How much does conversational AI cost for a healthcare organization?
Our published reference for a hosted-model RAG assistant starts around $60,000; a custom pipeline with EHR access and regulated claims is $150,000 to $300,000+. An EHR-connected voice agent needs its own scoped estimate, with operating costs budgeted separately.
Can conversational AI work with existing healthcare systems?
Yes, when the EHR or scheduling vendor supplies the necessary access and permissions. Check the actual FHIR or other API operations, authorization and confirmation behavior before promising record updates or completed bookings.
What are the challenges of implementing conversational AI in healthcare?
The hard work includes permissions and source quality, plus evaluating unsupported answers and failed actions. Give staff ownership of exceptions and monitor completed handoffs after launch.