

You’ve sat through the generative AI in healthcare pitch at every conference and in every vendor deck this year. Every day another vendor claims genAI in medicine has solved something. From Google’s MedLM transforming chest X-ray analysis to AI-driven drug discovery at Eli Lilly, the headlines are impossible to ignore. Then there’s NVIDIA, launching dozens of gen AI microservices built for healthcare enterprises.
You might be wondering: Isn’t it time to put this to work in your own organization? Meanwhile you’re working against fixed budgets, regulatory review, an integration backlog, and clinicians who abandon any tool that adds clicks. Generative AI has to survive all four.
So here’s the practical version: what generative AI actually does in patient care and operations, what it costs, and where it still breaks.
What does generative AI actually do in healthcare, and what does it cost?
It drafts: clinical notes, billing codes, patient messages, synthetic training data, and increasingly it chains those drafts into workflows that a clinician approves. Half of US healthcare organizations have implemented it and 82% expect a positive return. A retrieval-based assistant on hosted models starts around $60,000 to build, with running costs from about $25 a month at pilot scale to six figures a year once you self-host.
Top Takeaways:
- Half of US healthcare organizations have implemented generative AI, up from 25% two years earlier, and every respondent in McKinsey’s latest survey now has some plan for it. Budgets grew hard in the early wave: 18% of technical leaders reported a 300%-plus increase back in early 2024.
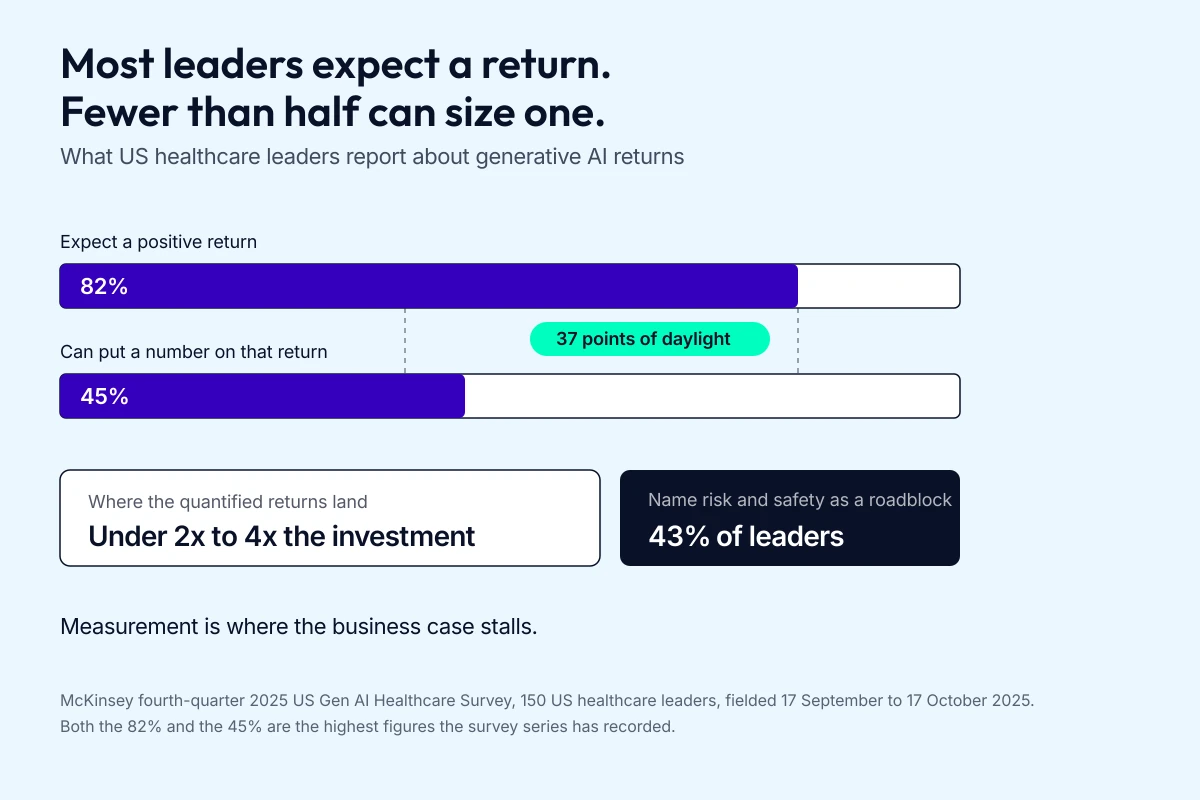
- Gen AI in healthcare earns its keep on documentation, coding, patient communication and synthetic training data, and gen AI in healthcare returns are real but unevenly measured: 82% of leaders expect a positive return and 45% can put a number on it.
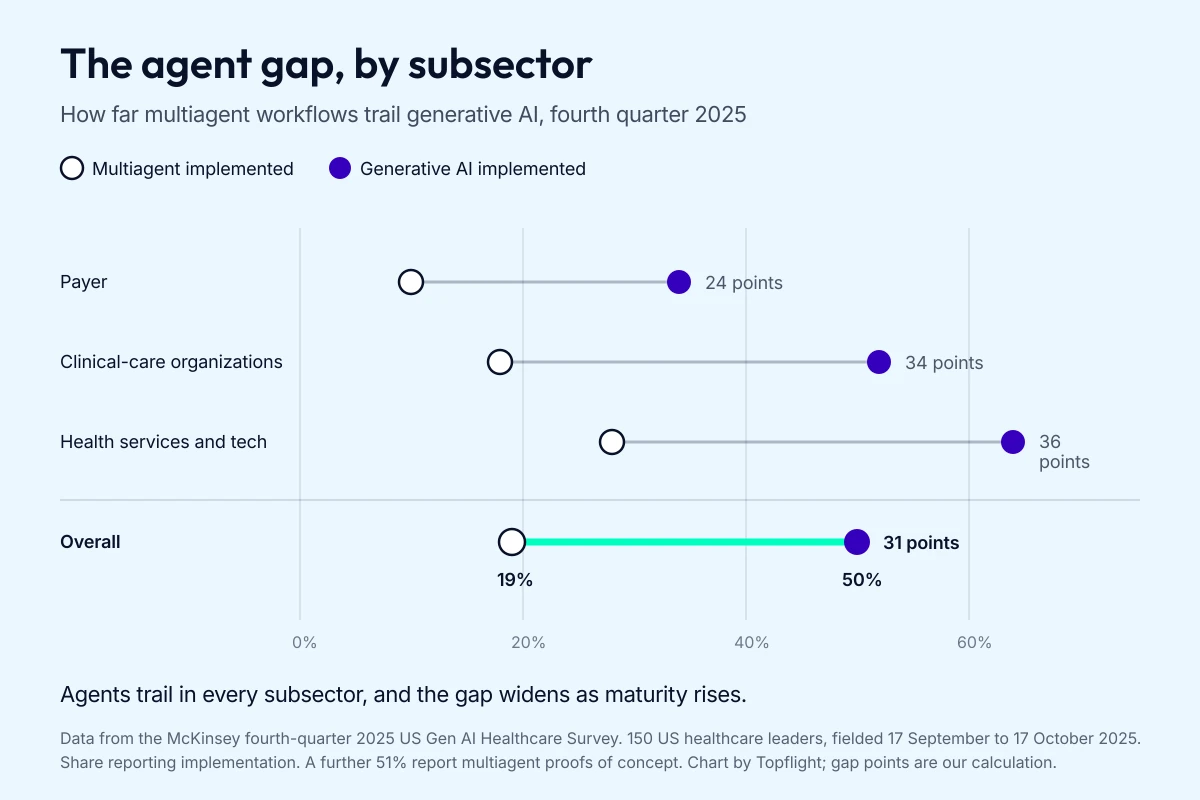
- AI agents have arrived and are early. 19% of healthcare organizations have implemented multiagent workflows and 51% are running proofs of concept, but every system shipping today stops for a human to approve the result.
Table of Contents:
- GenAI in healthcare: where it stands in 2026
- Addressing healthcare challenges with generative AI
- Benefits and ROI of generative AI in healthcare
- Generative AI healthcare applications that are already in use
- Multimodal gen AI in healthcare: standard input, unsettled accuracy
- From chatbots to agents: what shipped in 2025-2026
- Bringing GenAI to healthcare: overcoming implementation challenges
- Compliance: HIPAA, FDA, and the state laws now in force
- How much does a generative AI healthcare solution cost?
- Topflight’s approach to implementing generative AI in medicine
GenAI in healthcare: where it stands in 2026
Generative AI, a subset of artificial intelligence that involves creating new content based on existing data, is now doing real work in healthcare.
Defining generative AI in the medical context
When we talk about healthcare generative AI, we’re referring to AI systems capable of generating text, images, and other data that can improve patient care and cut the administrative work around it. In practice that means drafting the patient report and simulating outcomes for a new drug candidate.
Two neighbours to this page if you want to go deeper on the technology itself: large language models in healthcare covers the model layer these products are built on, and machine learning app development covers custom and on-device ML, which is a different build from anything in this article.
Current healthcare generative AI market size and growth projections
Market sizing for generative AI in healthcare is softer than the confident single numbers going around suggest, so here’s the range. For 2026, three research houses put the generative-AI-in-healthcare market between roughly $3.6 billion and $4.7 billion, a 32% spread driven by where each one draws the boundary. The Business Research Company, mid-band, has it at $4.44 billion in 2026 growing to $13.11 billion by 2030.
One caution if you’re collecting these figures yourself: the widely recirculated forecasts in the $20 billion-plus range for 2025 and 2026 measure all AI in healthcare, roughly eight times the generative-AI-specific market, and they get relabelled constantly.
On adoption, the figure most often quoted for 2024 traces back to a survey Gradient Flow ran for John Snow Labs between 12 February and 15 March 2024, with 304 respondents. It found 11% of healthcare organizations running multiple generative AI solutions in production, with another 14% having put their first one live. Statista repackages the same survey, so citing both is citing one source twice.
Adoption trends among healthcare organizations
Two surveys carry most of the weight in this area, and they’re worth separating, because they get cited as if they were independent.
McKinsey has tracked the same question annually, and the trend line is the useful part. Organizations reporting that they had implemented generative AI went from 25% in the fourth quarter of 2023 to 47% a year later and 50% in the fourth quarter of 2025, the first wave in which half the market was past piloting. In that same survey, for the first time, every respondent reported at least a plan. Counting everyone implementing, piloting or planning within a year, the figure is 95%. Read those two measures separately, because a 2024 headline about “70% implementing or testing” and a 2026 headline about “50% implemented” describe different things. (McKinsey, fourth-quarter 2025 US Gen AI Healthcare Survey, 150 leaders, fielded 17 September to 17 October 2025.)
The second is that same Gradient Flow survey, sponsored by John Snow Labs and fielded in February and March 2024. Among technical leaders specifically, 18% reported generative AI budgets rising more than 300% and another 16% reported a 100% to 300% rise. That survey was billed as inaugural and hasn’t been repeated, so treat the 300% as a snapshot of early-2024 enthusiasm.
The same survey found healthcare buyers leaning toward custom, task-specific models over general-purpose ones, at 36% of respondents. The applications they named most were answering patient questions (21%), medical chatbots (20%), and data abstraction (19%).
Technical leaders prioritize information extraction and biomedical research. Smaller companies, driven by agility, see significant potential in technologies like medical chatbots and transcribing doctor-patient conversations to gain a competitive edge.
Effective medical device integration decides how much patient data your generative AI system can see, and whether monitoring survives go-live.
Addressing healthcare challenges with generative AI
Generative AI does its best healthcare work wherever the job is producing text. With those content-generation tools, healthcare organizations can go after budget pressure, staff burnout, aging integrations, and the compliance review that gates all of it.
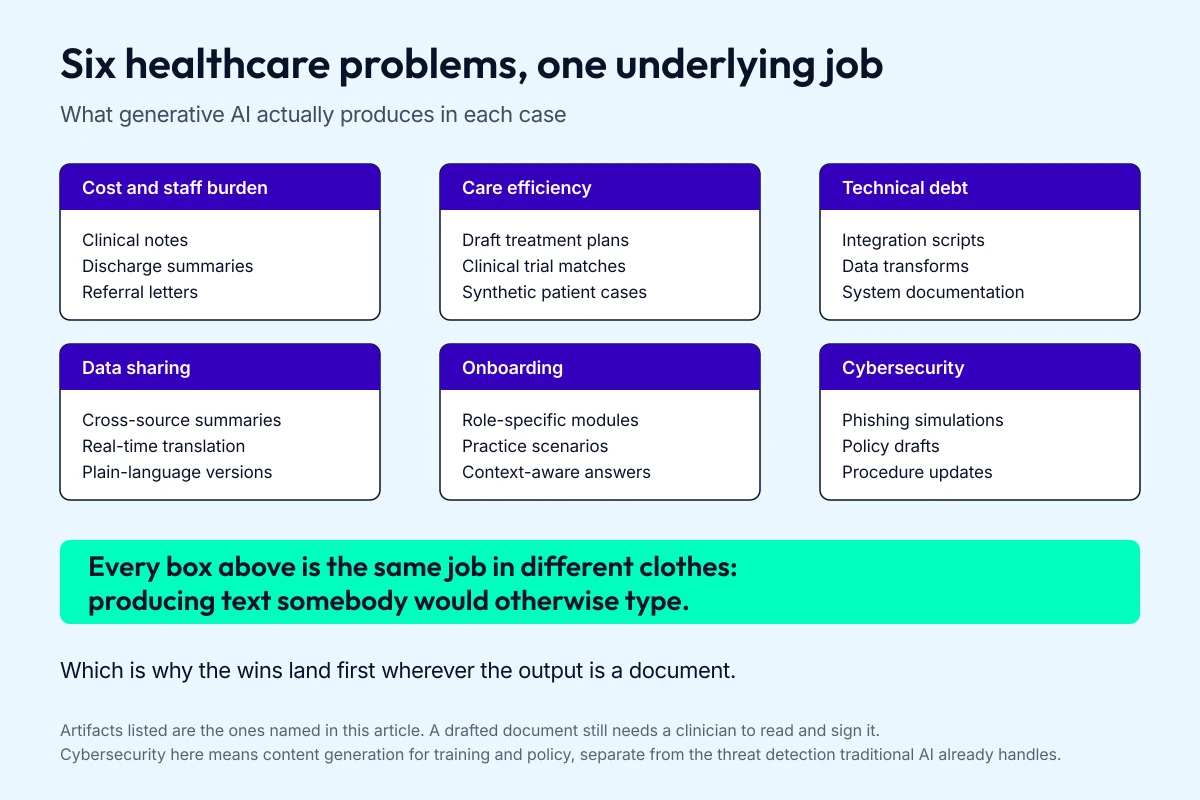
Six places where generative AI in medicine does real work:
Reducing costs and staff burden
Gen AI in healthcare cuts costs and staff workload most in content-heavy tasks:
- Automated Documentation: Generative AI can whip up clinical notes, discharge summaries, referral letters, and after-visit instructions from a short dictation, which cuts the hours clinicians spend in the chart.
- Smart Scheduling: A scheduling model can build staff and resource schedules that balance call coverage, room turnover, and no-show rates at once.
Generative AI can rework medical patient scheduling software, packing appointment slots tighter and cutting wait times.
- Personalized Patient Communications: Generative AI can churn out tailored discharge instructions, follow-up messages, refill reminders, and reading-level-matched education, without adding to staff workload.
Improving medical care efficiency
GenAI in medicine takes steps out of clinical workflows by drafting the content a decision needs:
- Treatment Plan Generation: AI can draft a personalized treatment plan from the patient’s chart and the published literature, then leave the clinician to sign or reject it.
- Clinical Trial Matching: Generative AI can produce detailed patient profiles and pair them with suitable clinical trials, speeding up research and getting patients into trials they’d never hear about otherwise.
- Synthetic Patient Cases: AI can generate synthetic data for training and quality review, so residents practice on realistic cases that contain no real patient records.
Addressing technical debt
Generative AI helps you modernize the systems your technical debt is sitting in:
- Legacy System Integration: Generative AI can craft APIs and data transformation scripts to bridge old and new systems, easing transitions.
- Documentation Generation: AI can auto-generate up-to-date system documentation, making it simpler to maintain and upgrade existing infrastructure.
Improving data sharing and communication
Gen AI excels at creating content that facilitates better communication and data sharing:
- Automated Report Generation: AI can compile and summarize data from various sources into coherent, shareable reports.
- Multilingual Communication: Generative AI can produce real-time translations and culturally appropriate health information, knocking down language barriers in diverse healthcare settings.
Getting new staff productive faster
GenAI can shorten onboarding by writing the material for each new hire:
- Role-Specific Training Materials: AI can generate tailored training modules and quizzes based on a new hire’s role and existing knowledge.
- Virtual Mentoring: A medical chatbot trained on your own protocols answers the questions new hires would otherwise save up for their preceptor.
Strengthening cybersecurity
Generative AI has two security jobs worth funding, both of them content generation:
- Phishing Simulation: Generative AI can create realistic phishing scenarios for staff training, bolstering overall security awareness.
- Policy Generation: AI can draft and update cybersecurity policies and procedures, ensuring they stay current with evolving threats and regulations.
Generative AI in medicine earns its budget where it takes documentation and coordination work off clinical staff. The payoff shows up as fewer hours in the chart and fewer handoffs dropped between departments.
These tools buy back staff hours, and you still work inside the same insurance rules and compliance review you had before.
When considering the cost of EHR implementation, factor in the potential long-term savings and efficiency gains that integrating generative AI can bring to your healthcare practice.
Benefits and ROI of generative AI in healthcare
The honest answer on ROI is that most healthcare leaders now expect one and a minority can prove it. That gap is the whole story of 2026.
- Sharper diagnoses and treatment plans: GenAI reads labs, notes, imaging reports, and prior visits in one pass, so the differential and the treatment plan come back with more of the patient in them. This leads to improved patient outcomes.
- Lower operating costs: By automating routine tasks such as documentation and billing, GenAI gives those hours back to staff, and the overhead comes down with them.
- Faster R&D cycles: GenAI takes the first pass at candidate generation and protocol drafting in drug discovery, which is usually where the R&D calendar goes.
|
What leaders report |
Q4 2025 |
|---|---|
|
Expect a positive return on generative AI |
82%, the highest the survey has recorded |
|
Can put a number on that return |
45% |
|
Size of the quantified return |
Under 2x to 4x the initial investment |
|
Name risk and safety as a roadblock to scaling |
43% |
Figures from McKinsey’s fourth-quarter 2025 US Gen AI Healthcare Survey, fielded 17 September to 17 October 2025 across 150 healthcare leaders.
Our own build gives the cleanest version of that arithmetic. GaleAI, the AI medical coding platform we took from prototype to market, costs less than 1% of the revenue it recovers: in a one-month audit it identified 7.9% more billable codes than human coders, which for a single organization works out to $1.14M a year that was being left on the table.
AI-driven medical billing software development cuts the admin load and the error rate in revenue cycle management.
Generative AI healthcare applications that are already in use
Gen AI in healthcare covers a lot of ground. At Topflight we build these systems, so we see which generative AI healthcare use cases make it past the pilot and into daily use. The use cases of generative AI in healthcare below are the ones we keep running into on client builds.

Synthetic data generation for AI model training
One of the most promising generative AI applications in healthcare is the creation of synthetic medical data by using such AI models as Generative Adversarial Networks (GANs) or Variational Auto-encoders (VAEs). This tackles a major industry challenge: the scarcity of diverse, high-quality data for training AI models.
- Realistic Patient Records: Generative AI can produce synthetic patient records that mimic real-world data distributions, so you can train and test clinical decision support systems before any real PHI is in play.
- Rare Disease Modeling: For uncommon conditions, generative AI can augment limited datasets by creating synthetic cases, improving the accuracy of AI models for rare disease diagnosis and treatment.
- Demographic Diversity: Synthetic data generation can address biases in existing datasets by creating diverse patient profiles, ensuring AI models perform equitably across different populations.
Generative AI is doing real work in clinical decision support system implementation.
Personalized medicine and treatment plan generation
Generative AI is reshaping personalized medicine by creating tailored treatment plans and patient-specific recommendations in real time.
- Customized Treatment Protocols: By analyzing vast amounts of medical literature and patient data, generative AI can produce personalized treatment plans that consider the patient’s genetic profile and treatment history.
- Drug Interaction Predictions: Generative models can simulate potential drug interactions and side effects, aiding clinicians in making more informed decisions about medication regimens.
- Rolling Care Plans: As patient conditions evolve, generative AI can continuously update and refine treatment plans, so the plan keeps up with the patient’s current state.
At the University of North Carolina Lineberger Cancer Center, AI-generated treatment suggestions matched oncologists’ decisions in 97% of rectal cancer cases and 95% of bladder cancer cases. Check the date: that’s a 2023 result, and matching a tumour board is a different test from working unsupervised.
Drug discovery and molecular design
In drug development, generative AI is speeding up the discovery process and opening new avenues for innovation.
- Novel Molecule Generation: AI models can generate and evaluate millions of potential drug candidates, which shortens the early stages of drug discovery.
- Target Identification: Generative AI can predict potential drug targets by analyzing biological pathways and generating hypotheses about disease mechanisms.
- Repurposing Existing Drugs: By generating new applications for existing medications, AI can identify potential treatments for different conditions, saving time and resources in drug development.
Insilico Medicine is the most-cited proof point here, and the figure gets repeated without its scope. Its 18-month drug discovery figure covers going from target to a nominated preclinical candidate, on about $2.6M. That candidate, rentosertib, entered Phase III in July 2026 across 47 centres in China after a Phase 2a trial in 71 patients showed lung function improving against placebo. No AI-discovered drug has been approved anywhere yet, which is the honest state of the field as of September 2026.
Administrative task automation
Most of the admin load is text moving between systems, which is exactly what generative AI is good at.
- Automated Report Writing: AI can generate comprehensive medical reports, discharge summaries, and referral letters based on clinical notes and patient data.
- Smart Documentation: Generative AI can create and update medical records in real time during patient consultations, reducing the administrative burden on clinicians.
- Intelligent Billing Systems: AI-powered systems can generate accurate billing codes and insurance claims, minimizing errors and improving reimbursement rates. See our breakdown of AI medical billing software for what actually moves first-pass yield.
Our medical records automation guide covers the full stack behind these workflows.
The Permanente Medical Group reported that ambient AI scribes saved its physicians an average of one hour a day on documentation, from its 2024 rollout. Later controlled trials have landed lower, which is the pattern worth expecting: a randomized trial at UCLA Health published in late 2025 measured a 9.5% reduction in time spent in notes.
Generative AI is already inside the best telemedicine apps.
Patient communication and virtual health assistants
Patient engagement is mostly messages your staff has no time to write, and that’s the work generative AI takes on.
- AI-Powered Chatbots: Advanced chatbots can provide 24/7 patient support, answering queries and booking appointments.
- Personalized Health Information: Generative AI can create tailored educational materials for patients, considering their specific conditions, literacy levels, and cultural backgrounds.
- Virtual Health Coaches: AI assistants can generate personalized wellness plans, medication reminders, and lifestyle recommendations to support patient adherence and health outcomes.
The most-quoted study here is worth handling carefully. A 2021 study of 36,070 Woebot users found they formed a working bond with the app within 5 days, comparable to what people report with a human therapist. Two caveats travel with that number now. Woebot ran on scripted, rule-based dialogue written by clinicians, so it’s evidence that a conversational agent can build rapport. Whether a generative model holds up in the same seat is still an open question. And Woebot Health retired the consumer app on 30 June 2025. Treat the finding as a useful baseline for patient-facing design, with the product itself as history.
Augmented medical imaging for training and analysis
Generative AI is already doing real work in medical imaging.
- Synthetic Image Generation: AI can create realistic medical images for training purposes, addressing the shortage of diverse imaging data, especially for rare conditions.
- Image Cleanup: Generative models sharpen low-dose and fast-acquisition scans, so fewer patients get called back for a repeat.
- Progression Simulation: AI can generate visual predictions of disease progression, aiding in treatment planning and patient education.
Medical imaging is its own discipline, and our guide to computer vision in medicine is the better starting point if that is your use case. Research on generative adversarial networks has shown they can produce synthetic brain MRI images that expert radiologists cannot reliably separate from real scans. That work predates the current multimodal models and still holds for training-data generation, which is where it is used.
Personalized patient education materials
Generative AI is transforming patient education by creating customized, engaging content.
- Reading-Level Matching: AI rewrites the same explanation at the reading level a patient actually has, and moves on as they pick it up.
- Multi-format Content Creation: Generative AI can turn one set of discharge instructions into a plain-language handout or a short video, matched to how the patient prefers to take it in.
- Real-time Translation and Localization: AI can instantly generate culturally appropriate health information in multiple languages, improving access to care for diverse populations.
The Center for Health Care Strategies reports that almost 90% of US adults struggle to understand health information, which is the problem this use case exists to attack.
If you want patients to control who sees their records, web3 development in healthcare is the architecture to read up on next.
Multimodal gen AI in healthcare: standard input, unsettled accuracy
Multimodal AI stopped being a differentiator some time in 2025. Every current frontier model from OpenAI, Anthropic and Google accepts images alongside text as a baseline capability. For a healthcare build, the question is how much you can trust what the model reads off a scan.
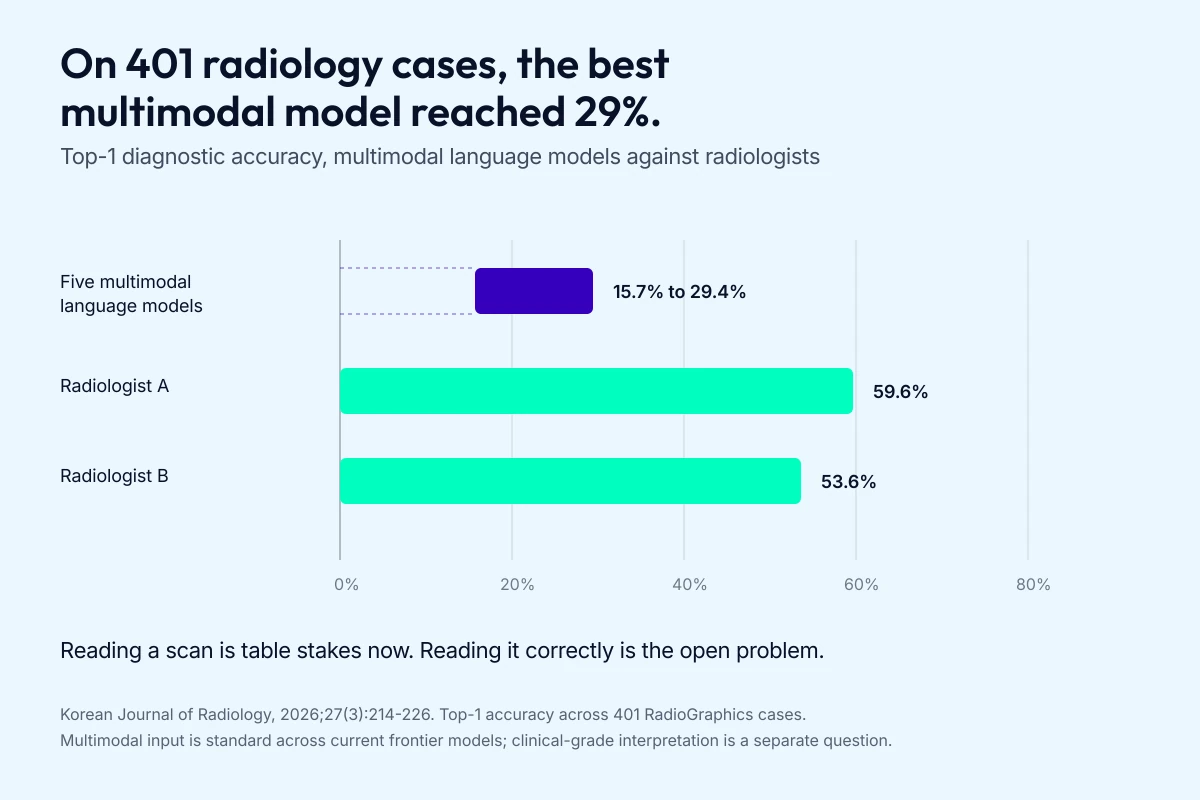
On the trust question the published evidence is thin and unflattering. In a 2026 study in the Korean Journal of Radiology, five multimodal language models worked through 401 RadioGraphics cases and reached top-1 diagnostic accuracy of 15.7% to 29.4%. Two radiologists on the same cases scored 59.6% and 53.6%. Multimodal input is standard; clinical-grade multimodal interpretation is a research problem.
Three input streams feed a multimodal healthcare system:
- Natural Language Processing: A speech model reads what the patient actually says, including the detail a written note leaves out.
- Computer Vision: Vision models mark anomalies in a scan for a radiologist to confirm.
- Real-Time Environmental Data: Cameras and sensors read the patient’s environment in real time.
A multimodal system runs those streams through generative AI and lands on one view of the patient’s condition. In practice:
- Earlier Detection: Patterns in radiology images, and shifts in a patient’s voice, flag a condition while it’s still developing.
- Improved Monitoring: Remote patient monitoring feeds telemedicine, so the clinician sees the change before the next visit.
Putting generative AI into a mobile product runs through your healthcare mobile app design decisions, so settle those first.
From chatbots to agents: what shipped in 2025-2026
Agents are in production now. The live question is where AI agents in healthcare stop.
The adoption numbers set the scale. In McKinsey’s fourth-quarter 2025 survey of 150 US healthcare leaders, 19% had implemented multiagent workflows against 50% for generative AI overall, with another 51% running proofs of concept and just 1% reporting no plans. Agentic AI is real and roughly two years behind the broader curve.

Which AI agents are actually running
Ambient documentation is the use case that scaled first. Microsoft Dragon Copilot passed 100,000 clinicians in March 2026. Abridge reported 300+ health systems and more than 100 million annual conversations by June 2026. Oracle’s Clinical AI Agent reached general availability across three 2026 releases covering order creation, note generation, and coding. Inside Epic, Art Insights runs more than 16 million uses a month and the Penny coding assistant is live in 200+ organizations.
Beyond scribing, the workflow AI agents are younger. Epic’s Agent Factory is still an early-adopter program: Advocate Health runs autonomous AI agents for inpatient pharmacy and infusion chart prep, and ECU Health runs AI chart summaries across all nine of its hospitals. Treat anything you read about Agent Factory at scale as a pilot until Epic says otherwise.
Every shipping system stops at a human
The pattern below holds across every vendor of healthcare AI agents we checked.
Scope your build around it. Epic’s AI charting queues up orders for a clinician to review; placing them stays a human action. CMS’s WISeR model, which runs AI-assisted prior authorization in six states from January 2026, requires that every recommendation for non-payment be made by a licensed clinician. The VA’s ambient scribe pilot requires providers to review, edit and approve each note, and the patient’s verbal consent before recording.
So the autonomy on offer today is drafting autonomy. AI agents can assemble the work; a person still signs it.
Where the hype outruns the evidence
Benchmarks built for agentic healthcare tasks are sobering. On HealthAgentBench, 54 tasks drawn from real clinical workflows, the best agent tested scored about 42%. An audit of 14,400 multi-agent cases found the agents repeated their own initial view in 98.42% of discussions, and deference to whichever agent spoke with most authority climbed from 35.30% to 68.75% across rounds of synthesis. Adding a second agent to review the first one’s output mostly adds agreement.
A separate evaluation of 21 frontier models on 29 clinical vignettes found differential-diagnosis failure rates above 0.80, even where final-diagnosis performance was far better. AI agents inherit that. If your design assumes the model reasons its way to the answer, test that assumption before it reaches a patient.
Bringing GenAI to healthcare: overcoming implementation challenges
Implementing GenAI for healthcare runs into five problems, and they show up in a predictable order. The first one decides how much the other four cost you.
1. Identifying use cases and setting priorities:
- Start by pinpointing specific areas where gen AI can make the most impact. Ambient clinical documentation, prior-auth drafting, patient messaging, and coding support are the usual starting points, and each one drags in a different compliance review.
2. Addressing data reliability and confidentiality concerns:
- Gen AI systems, particularly those powered by large language models and large medical models, rely heavily on data. Data that’s clean but six months stale fails a clinician the same way wrong data does. The governance question that matters is which subprocessors touch the PHI in your prompts and whether your BAA names them. That chain is where HIPAA compliance gets decided.
During the transition to AI-powered systems, proper EHR data migration decides whether the model sees a complete record or a truncated one.
3. Navigating legal and regulatory requirements:
- The legal environment for AI in healthcare is continually evolving. Decide early whether your gen AI feature meets the FDA’s device definition, because that answer sets your evidence burden and your timeline. Guessing wrong there means rebuilding your evidence package after you’ve already shipped.
As generative AI becomes more prevalent in healthcare, understanding SaMD certification requirements is essential for ensuring regulatory compliance and patient safety.
4. Strategies for smooth integration with existing systems:
- Integration with your existing IT stack is the part that slips. Phase the rollout by service line, and prove the workflow in one department before you widen it. Collaborate with IT and clinical staff to address potential technical and operational issues.
5. Measuring and projecting ROI for GenAI initiatives:
- Establish clear metrics to evaluate the performance and return on investment (ROI) of genAI initiatives. Track documentation minutes per encounter, denial rates on AI-drafted prior auths, clinician override rate, and the edit distance between the model’s draft and what gets signed. Without an owner for those numbers after launch, the pilot quietly becomes permanent and stops being measured.
Work through the five in order and the GenAI build stops being the risky part. Skip one and you’ll meet it again during procurement.
Compliance: HIPAA, FDA, and the state laws now in force
Compliance is the part that decides whether generative AI in healthcare can touch a real patient record. Most of it changed in the last 18 months, so anything you read from 2024 is now wrong in at least one direction.
BAA coverage runs service by service
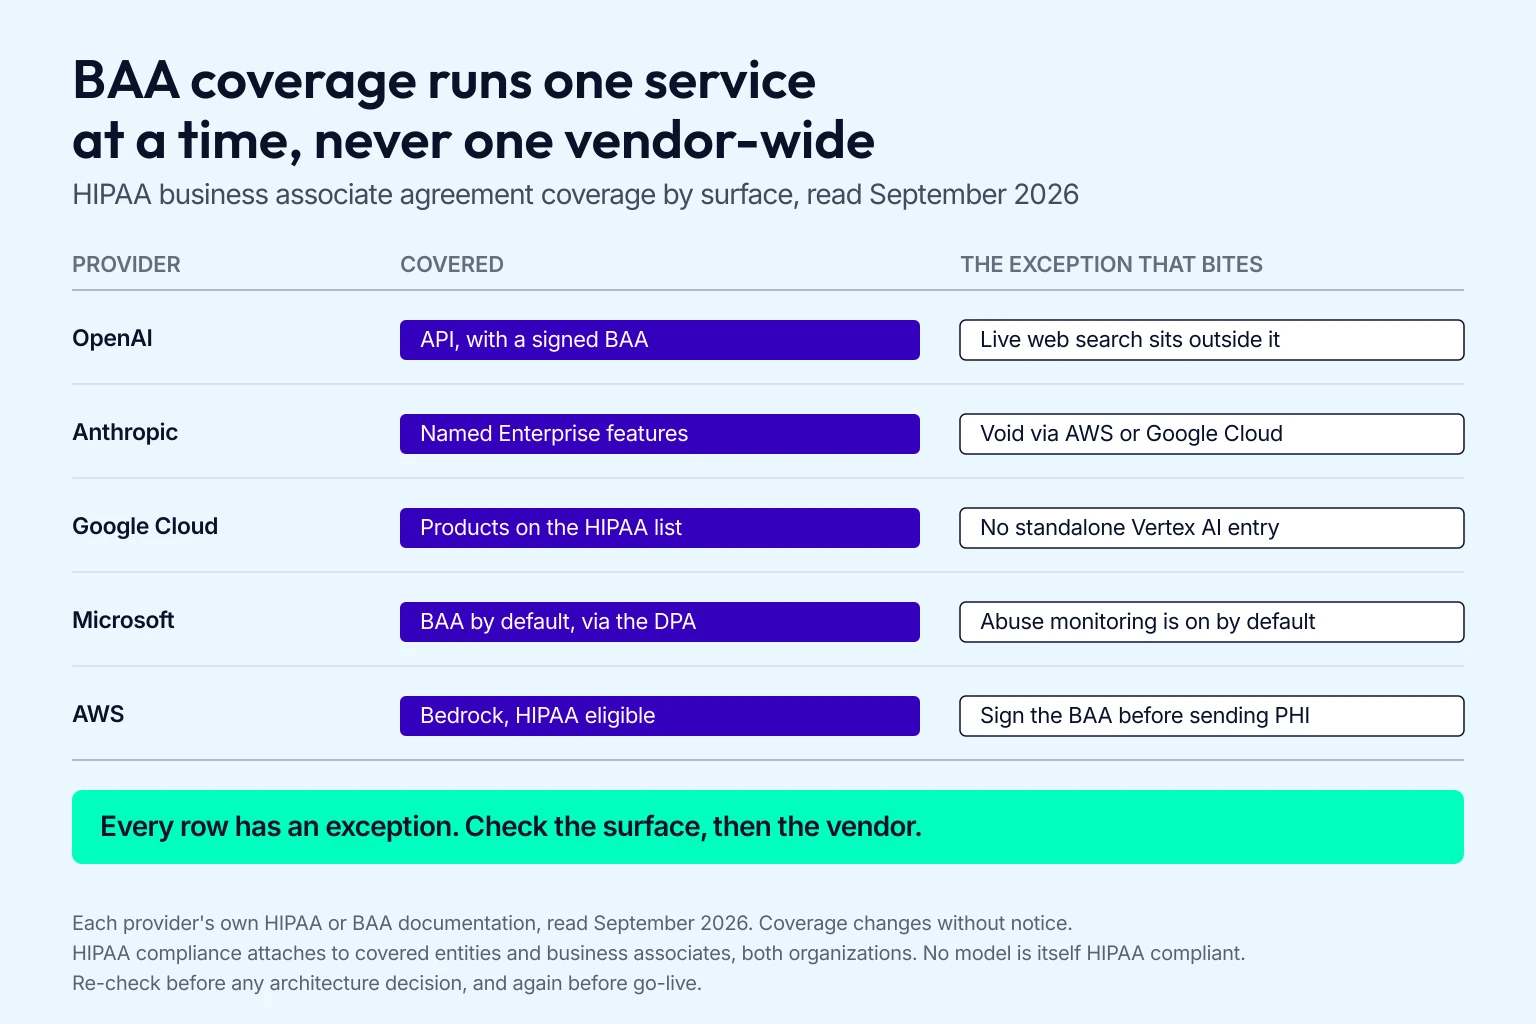
HIPAA compliance attaches to covered entities and business associates, both of which are organizations. A model is software, so the phrase “HIPAA-compliant model” describes nothing you can buy. What you need is a signed BAA covering the exact service you call, and coverage runs service by service.
Three examples worth checking against your own architecture, all read in September 2026. OpenAI will sign a BAA for its API, but live-internet web search sits outside it. Anthropic’s BAA doesn’t extend to Claude bought through AWS or Google Cloud, because those are the cloud provider’s services. Google’s HIPAA covered-products list no longer carries a standalone entry for Vertex AI, so a 2024 architecture diagram citing it needs a second look.
Redaction and de-identification are also different things. The rule at 45 CFR 164.514(b) recognizes two methods, Safe Harbor with its 18 identifiers and Expert Determination, and a regex PHI scrubber satisfies neither on its own. Our Mi-Life build handles this by stripping PHI before inference and reinserting it downstream, which keeps identifiers out of the model call without losing them from the workflow. If you want the wider pattern, our guide to HIPAA compliant app development covers the rest of the stack.
FDA has no rules specific to generative AI yet
That sentence surprises people, so here’s the evidence. FDA’s final guidance on predetermined change control plans, the document everyone cites when a model keeps changing after clearance, contains zero occurrences of “generative”, “large language model” or “foundation models”. Its January 2025 draft guidance on AI-enabled device software is still draft. In August 2026 FDA posted a discussion paper on generative AI devices that states on its face that it doesn’t propose or implement policy, with comments open until 19 October 2026.
Two facts are worth carrying into a board conversation. FDA has never authorized an unlocked AI-enabled device, meaning every one of the 1,614 AI/ML-enabled devices on its published list is frozen at the version that was reviewed. And a model that changes its own behavior in production reaches the market through a predetermined change control plan or not at all. If your roadmap includes a regulated claim, you are on the FDA SaMD path, and our SaMD certification guide is the next thing to read, and what the first FDA-cleared LLM clinical AI actually cleared.
The state laws arrived while everyone was watching Washington
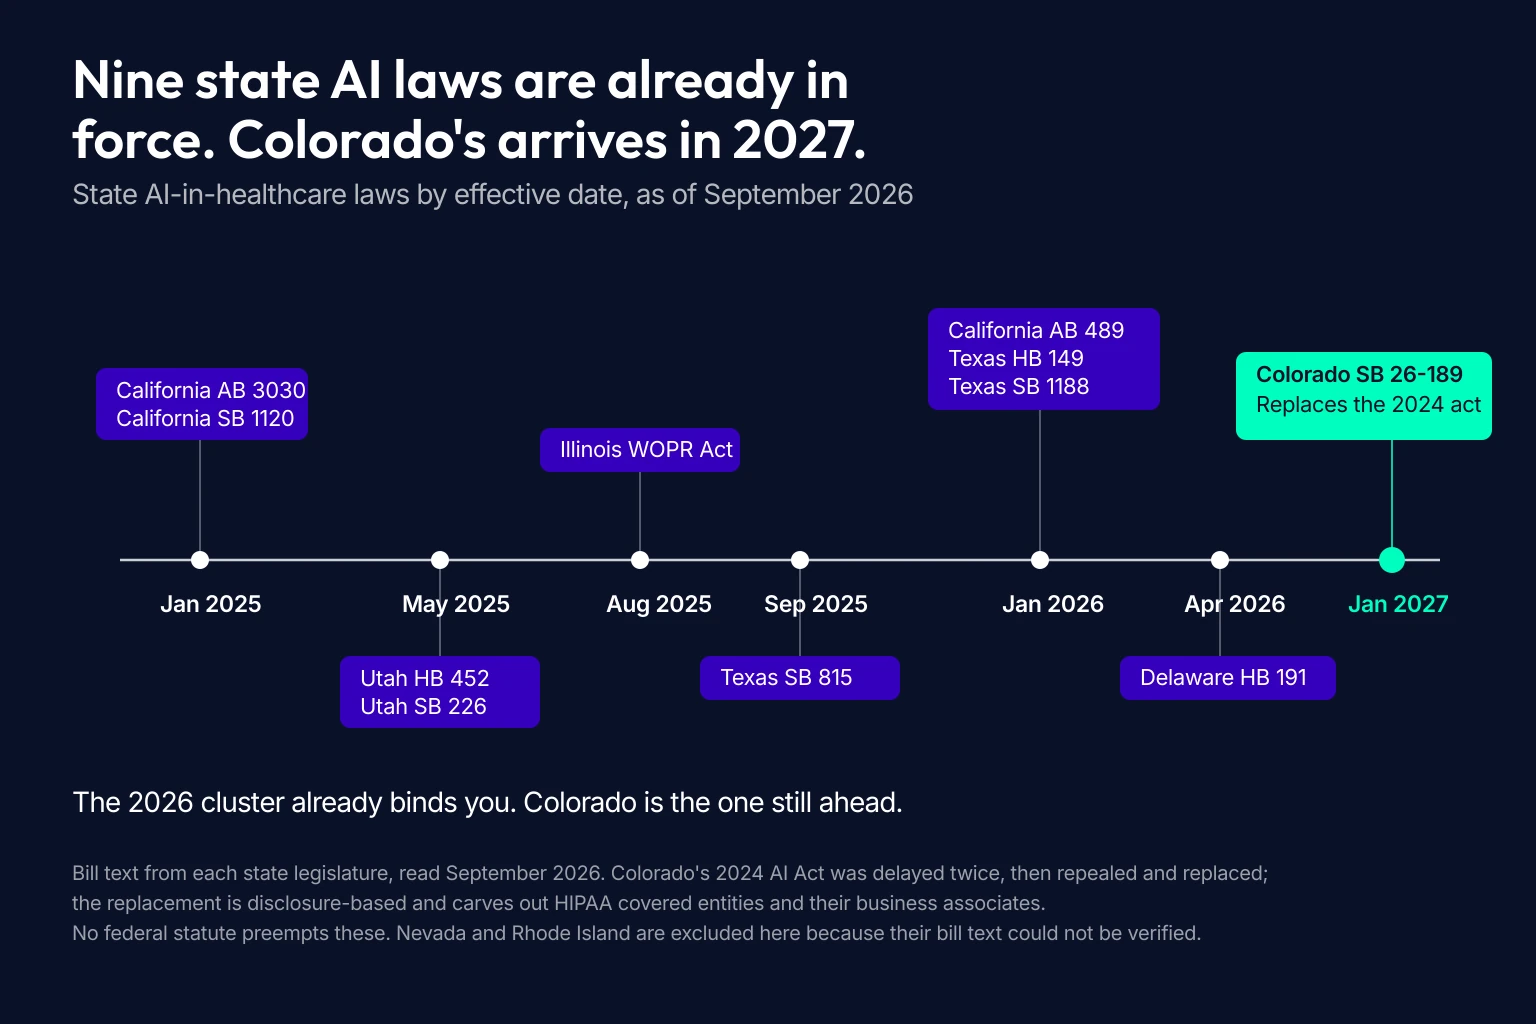
There’s no federal statute preempting state AI law. A December 2025 executive order set up a task force to challenge state laws in court, which is a litigation strategy. Meanwhile the states moved. In force as of September 2026:
|
Law |
In force |
What it asks of you |
|---|---|---|
|
California AB 3030 |
Jan 2025 |
Generative AI patient communications about clinical information carry a disclaimer plus instructions for reaching a human clinician. |
|
California SB 1120 |
Jan 2025 |
AI may assist utilization review but may not supplant a provider’s decision. |
|
California AB 489 |
Jan 2026 |
An AI system may not imply licensed-professional status in how it advertises or communicates. |
|
Texas HB 149 (TRAIGA) |
Jan 2026 |
Healthcare providers disclose AI use to patients. Attorney General enforcement only, with a mandatory 60-day cure period and no private right of action. |
|
Texas SB 815 |
Sep 2025 |
A utilization review agent may not use an automated decision system for adverse determinations. |
|
Texas SB 1188 |
Jan 2026 |
Electronic health records are physically maintained in the United States, cloud storage included. |
|
Illinois WOPR Act |
Aug 2025 |
AI may not provide mental health or therapeutic decisionmaking. |
|
Utah HB 452 and SB 226 |
May 2025 |
Mental health chatbots disclose they are AI; licensed occupations disclose generative AI use. |
|
Delaware HB 191 |
Apr 2026 |
An AI agent may not be licensed as a nurse, APRN or physician assistant. |
Colorado is the one most summaries still get wrong. Its 2024 AI Act was delayed twice, then repealed and replaced by SB 26-189, which takes effect 1 January 2027, is built around disclosure obligations, and carves out HIPAA covered entities and their business associates. A federal court has also barred the Colorado Attorney General from enforcing the old version. So Colorado has no operative AI act today, and a different one arrives in 2027.
What the safety evidence actually supports
No published study shows that any guardrail stack makes generative output safe for clinical use without a human reading it. A JAMA systematic review of 519 studies found only 5% used real patient-care data. An evidence map published in June 2026 covering 55 studies and registered trials found none that addressed the management of patients. In a production ambient-scribe deployment, hallucinations appeared in 11.5% of the notes evaluated.
Hallucination mitigation is where most of the engineering budget goes, and retrieval grounding helps less universally than vendors suggest. An evaluation with 18 medical experts and more than 80,000 annotations found that standard RAG often degraded performance, while a narrower radiology study found it eliminated hallucinations on a constrained task. The pattern that holds up: grounding works when the question space is narrow and the source documents are the answer. Treat it as a design constraint.
Which is why every system in the next section stops at a human.
How much does a generative AI healthcare solution cost?
Generative AI in healthcare cost splits in two, and build cost and running cost behave differently, and teams that budget only the first one get surprised in month four. Our app development costs guide carries the full model, and AI app development covers how these builds are put together.
By pattern
A retrieval-based assistant on hosted models, which covers most clinical documentation and knowledge-lookup work, starts around $60,000 at our minimum engagement. A custom pipeline with EHR integration and a regulated claim behind it runs $150,000 to $300,000+, the band healthcare builds land in. Fine-tuning is the option to reach for last, because it earns its cost only when you can measure a gap that retrieval didn’t close, and it adds a permanent premium on every inference afterwards.
Running it is where the money moves
At pilot scale, roughly 1,500 sessions a month, a managed API costs about $25 to $30 a month. Self-hosting the same workload runs about $800 a month, billed whether anyone uses it or not, because the GPU doesn’t care that it’s idle. That gap runs 25 to 30 times, and it closes only at volume: the break-even against managed APIs lands somewhere around 70,000 to 80,000 sessions a month.
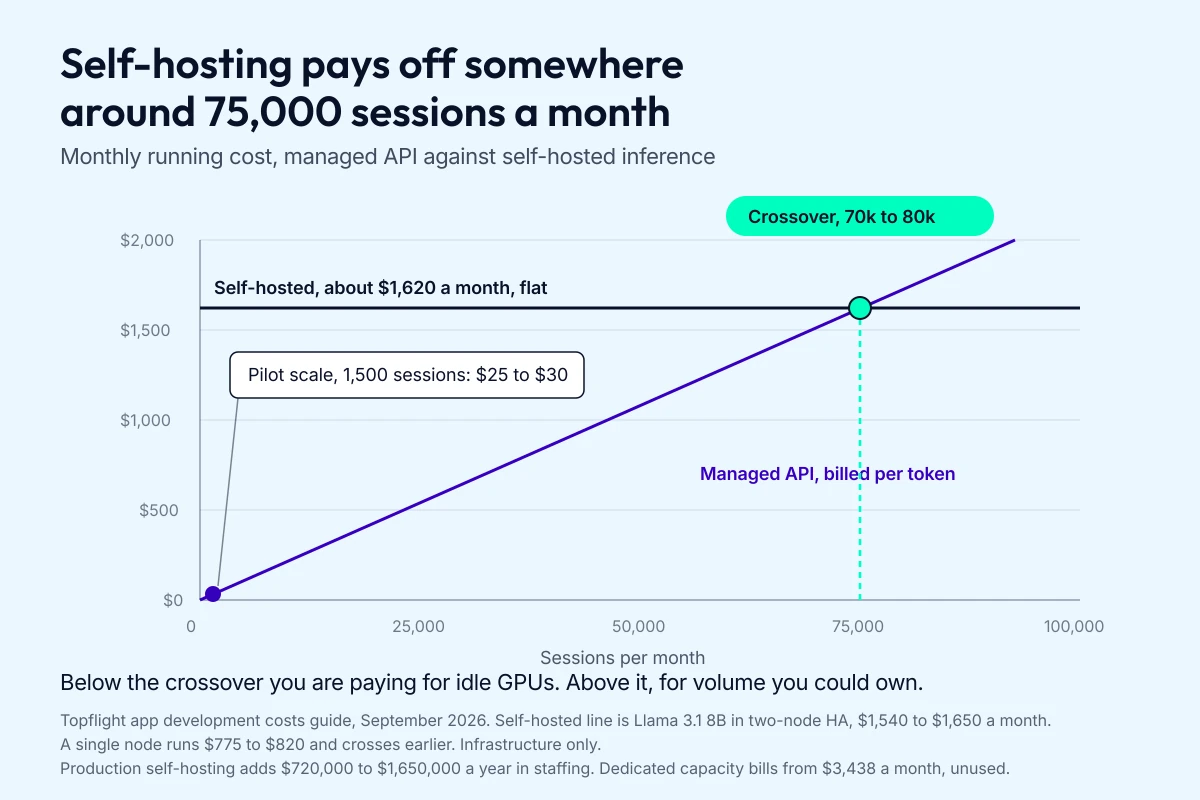
Two line items catch teams out. Dedicated capacity, which you buy for guaranteed throughput or to serve a fine-tuned model, bills a floor regardless of traffic: AWS Bedrock custom model units run about $3,438 a month each, and Azure provisioned throughput starts near $10,800 a month. A self-hosted production setup also needs people, and a minimal team of AI infrastructure, DevOps and evaluation staff runs $720,000 to $1,650,000 a year fully loaded.
Then the quiet ones: a vector database ($0 to $50 a month self-hosted at small volumes, $70 to $500 managed at 10 million vectors and up), evaluation harnesses, and manual review of an extra 15% to 20% of interactions for anything high-stakes. That review line is a compliance cost as much as a quality one.
Topflight’s approach to implementing generative AI in medicine
We build generative AI into healthcare products that have to hold up in production: under HIPAA, inside an EHR workflow, in front of clinicians who will stop using anything that wastes their time. Two of those builds run below. GaleAI is the revenue case, and Mi-Life is the safety case.
And it all starts with scheduling a free AI consultation to work out what you actually need before anyone writes code.
Here’s how we do it:
AI strategy development
We start with your goals and the workflows you already run, then name the places where AI earns its cost. You leave with a ranked list of what to build first and what to skip.
AI-powered data analysis and insights
Your data quality is the ceiling on what any of this can do. So we look at what you actually have and which clinical decisions and operational questions it can already inform. Often the honest answer is that half the work is data cleanup before any model runs.
Custom AI solution design
We design each AI build around the workflows your organization already runs. That work has included chatbots for patient care, AI-driven diagnostic tools, computer vision for remote diagnostics, and document processing your team would rather not do by hand.
AI ethics and compliance guidance
In healthcare the ethics and compliance questions land before the model does. We tell you which data flows you can defend in an audit, and where your pipeline touches PHI in ways HIPAA cares about. This helps you maintain patient trust and avoid legal pitfalls.
To get generative AI running in your medical practice, partnering with an experienced healthcare app developer saves you the integration surprises that eat timelines.
Key activities
AI readiness assessment
We start with an AI readiness assessment to evaluate your current systems and the shape of the data inside them. This assessment helps us determine the best strategies for integrating AI into your existing infrastructure, considering factors like your electronic medical records (EMR) systems and data structures.
Custom AI solution design
Our custom AI solution design process involves creating tailored AI systems that address your specific business needs. For document processing and computer vision, we build against the workflow your clinicians already run, then measure whether it saves them time.
AI model development and training
We focus on developing and training AI models using your data, employing techniques like retrieval-augmented generation (RAG) to ensure accurate and context-specific responses. We test them against your own cases before a clinician sees the output.
AI integration and implementation
Integration is where most AI pilots stall. We ensure that our AI solutions are compatible with your current workflows, including EMR systems and mobile applications. Our implementation process prioritizes data security and HIPAA compliance.
Ongoing tuning and support
We stay on after launch. We monitor the systems we build and tune them when the data underneath changes. That means regular updates and someone responsible when accuracy starts drifting.
Featured case study: GaleAI, AI-powered medical coding platform
A team of industry veterans set out to fix medical coding with an AI platform. They needed a partner who could take the concept to a shipping product, and Topflight built it. Key features:
- Identifies CPT codes in seconds from medical notes
- Accessible on any platform (web, mobile, tablets)
- Integrates with major EHRs like EPIC and Athena
- Avoids under-coding, potentially increasing revenue by up to 15%
To maximize the benefits of generative AI in healthcare, it’s important to integrate health app with Epic EHR/EMR systems, allowing for comprehensive data analysis and improved patient outcomes.
What we built:
- Natural Language Processing for code lookups using common language
- Deep Neural Network for continuous learning and improvement
- Optical Character Recognition for instant analysis of handwritten notes
- HIPAA-compliant with full data encryption and PHI de-identification
Benefits for healthcare providers:
- Reduces coding time by 97%
- Cuts administrative overhead
- Standardizes coding practices across organizations
- Minimizes PHI exposure risks
How we built it:
- Rapid prototyping and MVP development (6-9 months)
- Cross-platform accessibility (web, iOS, Android)
- EHR integration with FHIR compliance
- AI/ML technologies: NLP, Deep Neural Networks, OCR, GenAI for interfacing with providers
Measurable outcomes:
- Identified 7.9% more codes than human coders in a 1-month audit
- Potential to recover $1.14M in lost revenue per year for a single organization
- Cost of implementation less than 1% of gained revenue
Second case study: Mi-Life, a clinical assistant that says “I don’t know”
Caregivers at Goldie Floberg, a disability services provider, worked from roughly 1,300 pages of client plans, policies and procedures. New staff carried the worst of that load, and the information they needed most sat in a binder while they were mid-shift.
We built a HIPAA-compliant chatbot they query by voice or text during a shift. RAG (retrieval-augmented generation) over a vector database keeps every answer tied to that client’s own documents, metadata tagging stops one client’s records surfacing under another, and when the documents don’t cover the question the assistant says it has no information rather than inventing an answer. PHI is stripped before inference and reinserted downstream, on Azure OpenAI and BastionGPT.
Medication errors fell 72%, and staff rated it above 70 NPS.
Connect with our team to see more of what we’ve built with generative AI. Ask us about the builds that aren’t in this post.
Book a call with our experts today to ensure your application of generative AI in health generates real traction.
[Reviewed September 2026]
Frequently Asked Questions
What exactly is generative AI and why is it important in healthcare?
Generative AI refers to a type of AI that creates new content such as text and images, based on existing information. In healthcare, this technology is critical because it can draft documentation, support diagnosis, and generate personalized patient care plans. It’s transforming how healthcare providers deliver and manage care by making operations faster and cheaper to run.
How can generative AI improve patient care?
Generative AI can enhance patient care in several ways:
- Treatment Plans: It helps create tailored treatment plans based on a patient’s unique medical history and conditions.
- Patient Communication: AI-driven tools provide patients with personalized communication, like follow-up instructions and reminders.
- Diagnostic support: by reading patterns across patient histories and imaging, generative AI shortens the path to a precise diagnosis.
Is generative AI cost effective for healthcare organizations?
Yes, generative AI can reduce operational costs by automating time-consuming tasks such as clinical documentation and patient scheduling. That frees staff for direct patient care and cuts administrative spend. The technology has proven ROI potential, especially when it reduces the need for repetitive manual tasks.
What are the main challenges of implementing generative AI in healthcare?
Key challenges include:
- Data Security: Ensuring patient data remains private and compliant with regulations like HIPAA.
- System Integration: Integrating new AI systems with legacy healthcare systems, such as EHRs, requires careful planning.
- Legal and Regulatory Compliance: Navigating evolving regulations for AI in healthcare is essential for avoiding compliance risks.
How is generative AI used for administrative tasks in healthcare?
Generative AI is ideal for automating administrative functions, including:
- Medical Report Generation: Creating detailed summaries and documentation with minimal input.
- Billing and Coding: AI helps ensure accurate billing and insurance claims, reducing human errors.
- Staff scheduling: AI builds schedules that balance availability, patient need and workload at once.
Can generative AI support multilingual communication with patients?
Absolutely. Generative AI can produce real-time translations and culturally appropriate health information, which matters most in multilingual communities where language is the thing standing between a patient and care.
How secure is generative AI in handling patient data?
Generative AI applications in healthcare prioritize data privacy and security, often employing encryption, de-identification of personal health information (PHI), and HIPAA-compliant practices. However, organizations must implement strict data governance frameworks to fully protect patient information and comply with regulations
What is the difference between generative AI and AI agents in healthcare?
Generative AI produces content: a clinical note, a draft reply to a patient message. An agent chains those outputs into a workflow and hands the result to a clinician for approval. That approval step is where healthcare agents currently stop. Epic queues orders for clinician review rather than placing them, and the CMS WISeR model requires a licensed clinician on every recommendation for non-payment. As of the fourth quarter 2025 McKinsey survey, 19% of US healthcare organizations had implemented multiagent workflows against 50% for generative AI.
How much does it cost to build a generative AI healthcare solution?
A retrieval-based assistant running on a hosted model starts around $60,000, our minimum engagement. Running it is the part teams underestimate. A pilot-scale assistant costs roughly $25 to $30 a month on a managed API, while self-hosting the same workload runs about $800 a month whether anyone uses it or not, and a self-hosted production setup adds $720,000 to $1,650,000 a year in staffing. Our app development costs guide has the full breakdown.
How do you keep generative AI HIPAA compliant?
HIPAA compliance attaches to covered entities and business associates, both of which are organizations. A model is software, so “HIPAA-compliant model” carries no meaning as a claim. What matters is a signed BAA covering the exact service you call, and coverage is per-surface: OpenAI’s live web search sits outside its BAA, and Anthropic’s BAA doesn’t extend to Claude bought through AWS or Google Cloud. Then de-identify before inference. Our Mi-Life build strips PHI during processing and reinserts it downstream.