

To build a mental health chatbot that survives production, you design for the conversations you hope never happen.
This is how to create a mental health chatbot that holds up: mental health chatbot development for product teams, therapist practices, healthcare orgs, and the solo clinicians who can’t staff a compliance problem.
How do you build a safe mental health chatbot in 2026?
Put a deterministic safety gate and a human handoff in front of the LLM, ground its answers in clinician-reviewed content, and let a licensed clinician own anything that needs clinical judgment. Classify the product before you build: a wellness tool, a HIPAA-covered healthcare tool and an FDA-regulated device carry very different compliance loads, and Illinois, Nevada and Utah each have their own AI therapy laws. A focused MVP with one workflow and basic escalation runs $30,000 to $80,000 over 12 weeks.
Top Takeaways:
- Budget the safety layer first; it’s the product. A mental health chatbot is a layered system: LLM, retrieval grounding, deterministic safety policy, human handoff, audit logs.
- Licensed clinicians handle anything needing clinical judgment; the bot handles intake, triage, psychoeducation, and between-session continuity. Hybrid care is what works in 2026.
- Every compliance layer has its own trigger: HIPAA when you handle ePHI, FDA/SaMD if you make clinical claims, state consumer health data laws, the FTC Health Breach Notification Rule, AI transparency rules, and SOC 2 Type II for enterprise deals.
- A focused MVP (one workflow, basic escalation, minimal data retention) lands at $30,000 to $80,000 in 12 weeks.
- Where your users live decides your monetization model: Illinois and Nevada restrict offering AI therapy to consumers, Utah bars advertising against conversation content and bars selling or sharing what users say, and Medicare reimbursement needs FDA clearance no generative-AI mental health product has received. Selling workflow tools to licensed practices is the one model open everywhere.
Table of Contents:
- What is a mental health chatbot?
- How do mental health bots work?
- Why build a mental health chatbot in 2026?
- Mental health chatbot use cases and limitations
- Essential features of a safe mental health chatbot
- How to build a mental health chatbot MVP in 12 weeks
- Safety and ethical considerations for mental health chatbots
- Regulatory compliance guide for mental health chatbots
- Mental health chatbot architecture and tech stack
- Best tools and platforms for mental health chatbot development
- Which mental health chatbot platform should you choose?
- Mental health chatbot examples: what product teams can learn from them
- What does a mental health chatbot cost to build?
- Mental health chatbot monetization models in 2026
- How to measure mental health chatbot ROI
What is a mental health chatbot?
A mental health chatbot is an AI-powered conversational program that provides mental health support, psychoeducation, self-assessment, mood tracking, and coping exercises through text or voice. It’s a front-door layer that routes people to mental health professionals when clinical judgment is needed.
These products carry ordinary weight: stress, anxiety, sleep problems, low mood. People searching for an AI therapy chatbot mean one of two things: a consumer support tool, or a workflow tool a clinic runs behind a licensed human. Neither is designed to diagnose or treat mental illness on its own, and the better products say so out loud.
Where the chatbot’s capabilities meet a user is a product decision you can’t quietly reverse. Four surfaces cover almost every build:
- a custom mental health mobile app
- a web portal (employer and clinic rollouts)
- an instant messenger integration (WhatsApp, Messenger, SMS)
- an avatar-based or voice-based experience
Pick the channel your users already live in, then work backward: what clinical oversight sits behind it, and what data you can safely put through it. That’s where SMS and WhatsApp get expensive.
How do mental health bots work?
Most mental health chatbots run on a five-stage dialog system. In older rule-based bots each stage is a discrete component. In modern LLM-based bots several stages collapse into a single model call, but the conceptual pipeline still holds and is the easiest way to reason about where things go right or wrong.
Stage one exists only in voice products, where off-the-shelf speech-to-text (STT) transcribes voice into text. Text-only bots start at NLU.
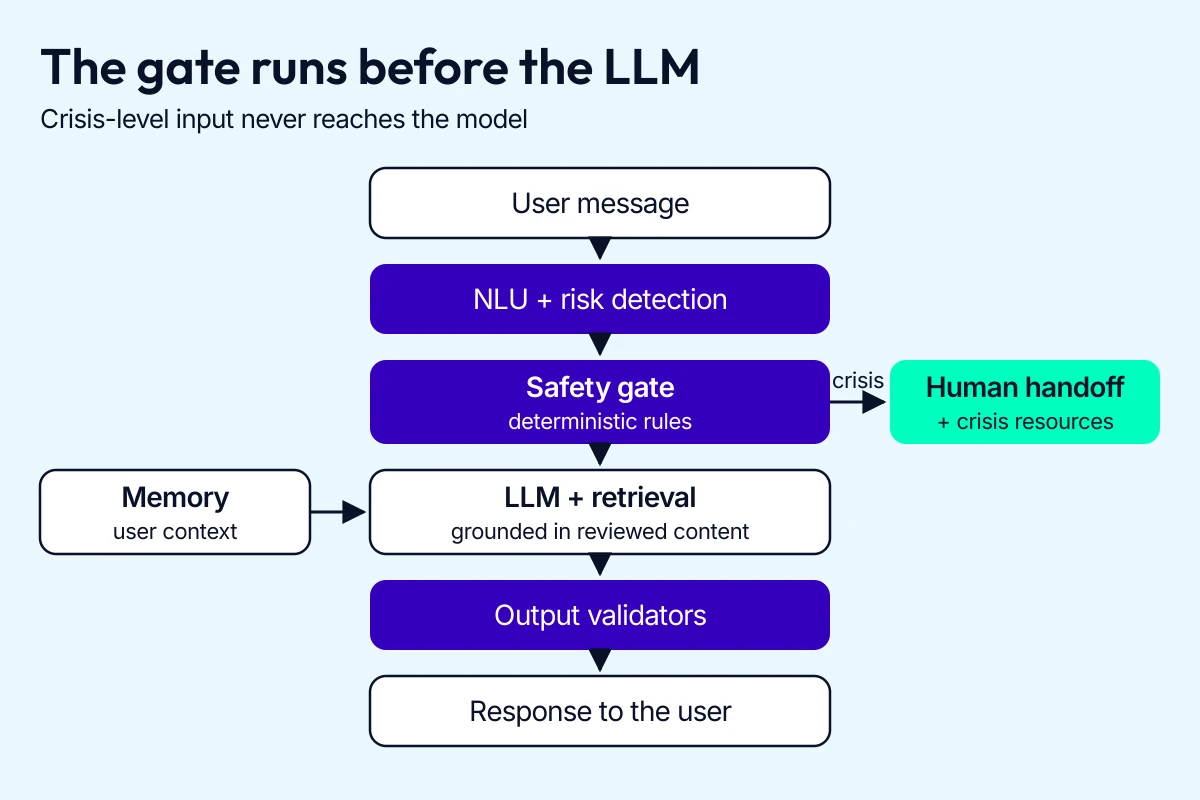
Modern mental health chatbot architecture: NLU and a deterministic safety gate sit in front of the LLM, with retrieval grounding, memory, and output validation around it. Crisis-level inputs bypass the LLM entirely.
Natural language understanding (NLU) decides what the bot thinks you said
In a CBT-style flow, NLU decides whether the user is venting, asking for a coping exercise, or showing distress signals that need an escalation. To tell those apart, it extracts four things from the user’s input:
- intent (what they want)
- entities (the parameters buried in the message)
- sentiment
- risk signals
Weak NLU is why the chatbot’s responses come back identical when a user phrases the same worry two different ways.
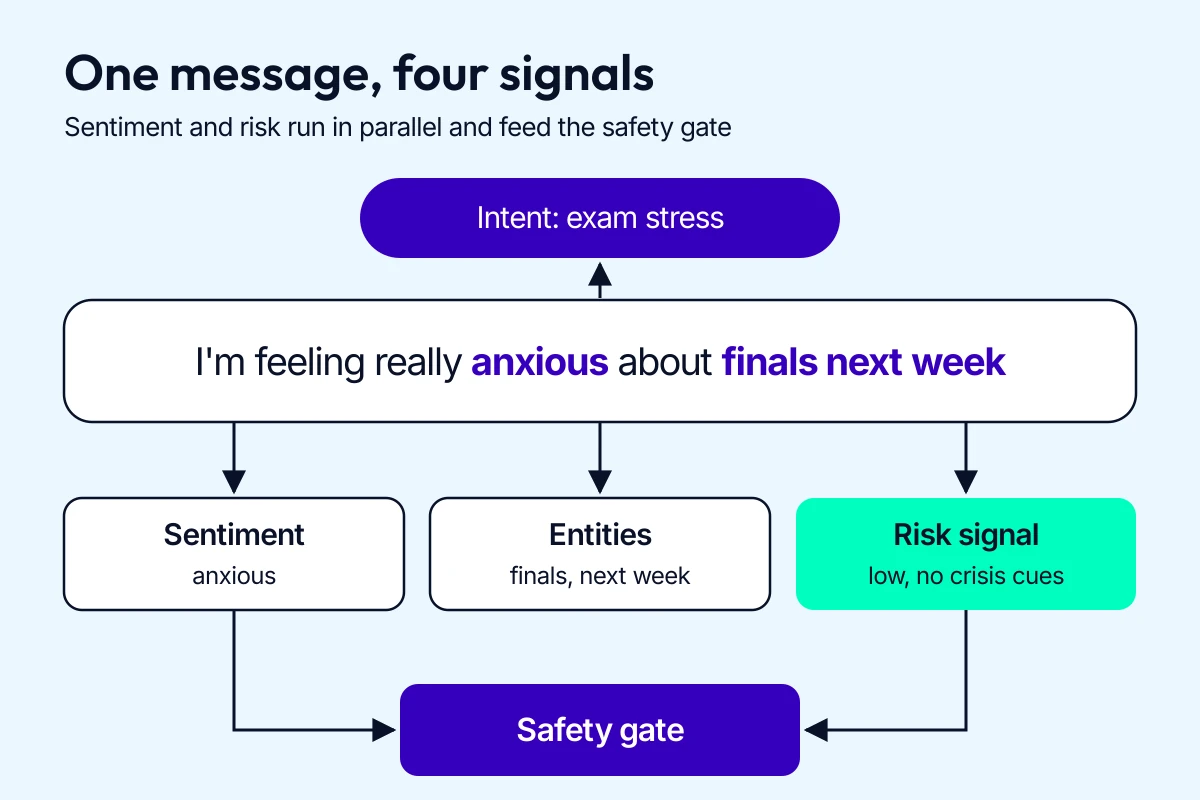
Modern NLU extracts more than just intent and entities. Sentiment and risk signals run in parallel and feed the safety gate downstream.
The dialog and task manager decides when to call a human
The dialog manager is where a safety-first mental health chatbot keeps its deterministic policy gates (more on that in the Safety section). It tracks context across turns (what the user said earlier, what’s already been collected) and decides what happens next:
- ask a follow-up
- run a coping exercise
- hand off to a clinician
- trigger a safety protocol
Teams that treat the dialog manager as plumbing rebuild it the first time a conversation goes somewhere the prompt didn’t anticipate.
Natural language generation (NLG) is the only layer your users ever see
Users judge the chatbot’s capabilities by this layer, so NLG wears the blame for mistakes made three stages upstream. Once the dialog manager decides what to say, how the NLG module says it depends on the bot you built:
- rule-based systems fill in a predefined template
- LLM-based systems generate a response constrained by prompts, retrieved context, and runtime guardrails
For voice bots, a speech synthesis module converts that text back into audio.
Why build a mental health chatbot in 2026?
If you run a therapist practice, sit inside a healthcare org, or are building a consumer-facing product, mental health chatbot development now sits in your ordinary build queue. It closes access gaps, cleans up intake, protects clinician time, and produces engagement numbers a payer will actually read.
Mental health chatbots help close access gaps
Capacity is the bottleneck in mental health support, and a mental health chatbot gets people around it with a 24/7 entry point. Waitlists run long, in-network panels are closed, and plenty of people give up before they ever reach a clinician. With the bot, four barriers drop out at once:
- the clock, for the client whose only free hour is 11pm after a night shift
- the map, for the client in a county where face-to-face counseling barely exists
- the phone, for the client who called four practices and found no availability
- the insurance question, which the bot never has to ask
Stigma is a different kind of barrier, and it moves too. Clients often feel more comfortable starting with a chatbot because it reads as anonymous, and they’ll disclose sensitive information earlier than they would across a desk in a first session. That pattern shows up across more than one recent study. Plenty of them end up with a human clinician anyway. The bot is what got them to start.
Hybrid care: chatbots improve intake, triage, and between-session continuity
Hybrid care is becoming the practical model: the bot is allowed to collect, suggest, and follow up. It’s not allowed to decide on a plan of care. That line is what keeps the system safe.
- Cleaner intake. The bot runs self-assessment prompts, collects basics, and summarizes what matters, so your practitioner isn’t burning 15 minutes on admin before therapy starts. Clients also arrive at the first session less “cold”, so the clinician spends that hour on the actual problem.
- Better triage. Higher-acuity users reach a human faster.
- Between-session continuity. Mental health professionals extend support between sessions without burning evenings and weekends, and the next session starts from what actually happened during the week.
Read more on chatbot development cost
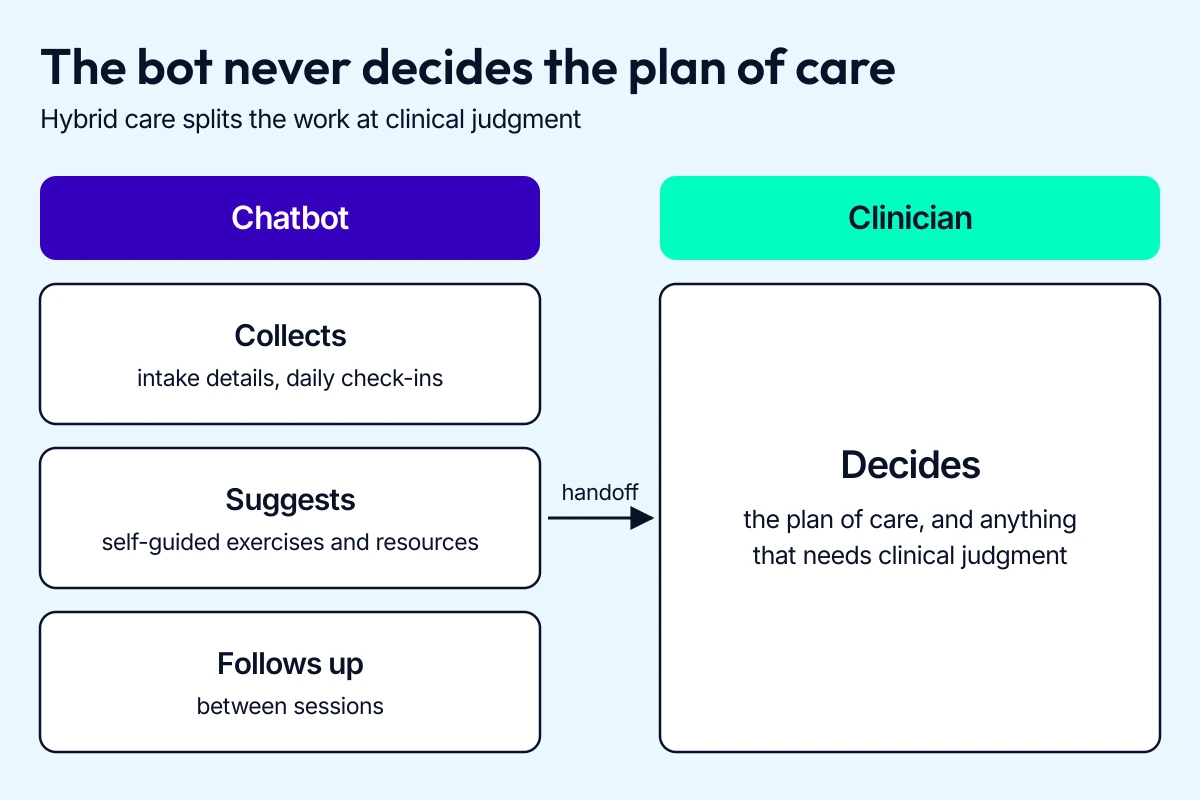
Mental health chatbots can reduce provider burnout, and the ROI adds up
You can read the 2026 therapist shortage straight off your calendar: late cancellations and clinicians spending their best hours on things that don’t require a license. The ROI story is a stack of small wins, boring on their own and together enough to cover the build:
- A bot handles the FAQ layer and basic triage, so per-user support cost drops and licensed hours, your most expensive resource, stay pointed at the clients who need them.
- Clients travel less and call less.
- Lower drop-off in the first 2 to 4 weeks of care.
- Fewer no-shows through structured reminders and pre-session prep.
- Stronger employer or payer outcomes data when the bot is part of a measured program.
What the evidence actually supports
The honest framing in 2026 is “promising, not magical.” The clinical signal is real but modest, and most of the well-supported outcomes come from structured, time-limited interventions paired with clear escalation and human oversight.
What the evidence supports today:
- Modest, measurable improvements in symptoms of depression and anxiety from structured CBT-style chatbots.
- Reduced feelings of isolation when the chatbot is positioned as a low-pressure first step.
- Higher engagement than information-only controls in several randomized trials, particularly with younger users and university populations.
- Healthcare professionals are warming to chatbots as a supervised piece of mental health support, as long as a clinician stays in the loop (see this recent survey).
Those trials mostly run 2 to 8 weeks, shorter than the care episode you’re pricing.
What the evidence does not support:
- Replacing licensed mental health professionals.
- Treating acute mental illness without clinical involvement.
- Long-term outcomes claims from short-term studies.
Related: Machine Learning App Development Guide
Mental health chatbot use cases and limitations
The mental health chatbots that hold up in production are narrow on purpose: two or three high-value use cases, clinical input on each, and a hard line against drift once they ship.
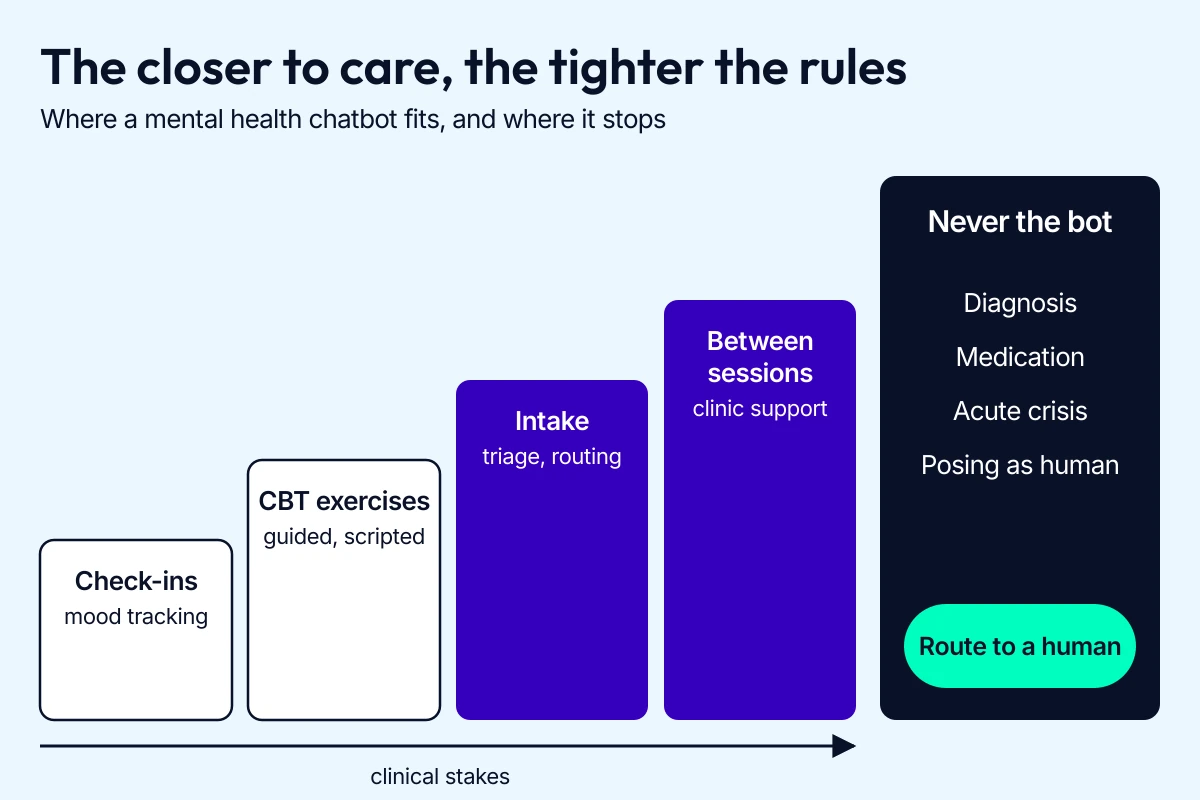
Daily emotional check-ins and mood tracking
The most reliable use case is also the cheapest to build: a daily or weekly check-in that captures a mood score and plots it over time. Low clinical risk, and people come back, which is more than most engagement features manage. Use a short structured prompt (mood, energy, sleep, stress), because an open “how are you” produces unplottable free text.
The chatbot’s responses should reflect what it heard and surface the trend line. When a pattern looks concerning, offer the door to a person: “would you like to talk to someone about this.” Naming candidate disorders puts you in regulated territory with no evidence behind it.
Guided CBT, mindfulness, and coping exercises
Structured, time-limited interventions have the strongest evidence base of anything the bot does, because they’re already scripted and skill-based.
Once a model generates clinical content on the fly, you can’t tell a reviewer where advice came from, which is why the shipped library stays small and boring:
- Thought reframing (identify the thought, evaluate the evidence, generate a balanced alternative).
- Grounding for acute anxiety (5-4-3-2-1 senses, paced breathing).
- Short mindfulness prompts users can run in 2 to 5 minutes.
- Sleep hygiene protocols and behavioral activation plans.
Intake, triage, and routing to human support
If you’re building inside a clinic, healthcare org, or B2B platform, intake and triage is often the highest-ROI use case. The bot collects basics, runs a structured screen, and routes them to self-guided resources, an appointment, or a higher-acuity escalation. Three things pay for it:
- Clinical time saved on admin and basic screening.
- A more productive first appointment, because the clinician already holds the context.
- High-risk users surfaced earlier than a manual intake queue catches them, which is usually what wins the clinical side over.
Clinical leadership owns the decision logic, and routing rules belong in deterministic code they’ve signed off on, where you can point at the branch that fired and say why. An LLM’s judgment gives you nothing to point at.
Between-session support for clinics and therapy practices
Therapy works when something happens between the weekly hour, and no clinician has room to chase every client manually. A chatbot can carry that work under a therapist’s eye, on four unglamorous jobs:
- Homework reminders and check-ins on assigned exercises.
- Mood and symptom tracking that feeds the next session as a clinical summary.
- Crisis-aware nudges that escalate to the clinician (or to crisis resources) when patterns shift.
- Psychoeducation that repeats what the clinician covered in session, in smaller pieces. The repetition is the point.
The bot never contradicts the plan of care, so mental health professionals decide in advance what happens when a client tells the bot something they haven’t told their therapist.
Employee wellness and student mental health support
Employee wellness programs and student mental health services have a large user base and a procurement path that already exists. Four things decide whether anyone uses the bot:
- Anonymous or pseudonymous access (employees and students are often hesitant to use named services).
- Skill-based modules tied to common life stressors (work pressure, exams, sleep, relationships).
- Clear escalation to in-network EAP providers or campus counseling services.
- No individual-level disclosures to employers or universities.
Where mental health chatbots should not be used
The list of things a mental health chatbot should not do is shorter than the list of things it can, and it matters more:
- Diagnosing mental illness or any mental health disorders. The bot can reflect, validate, and route. It cannot label.
- Recommending or adjusting medication. Any medication-related question routes to a clinician, with no exception for how reasonable the question sounds.
- Acting as the sole source of support for someone in acute crisis. Crisis flows must escalate to a human (or to crisis resources). A bot is not a clinician on call.
- Replacing therapy for severe or complex mental health disorders. Bots are useful adjuncts for many people, but they are not a substitute for treatment of severe depression, suicidality, psychosis, or trauma.
- Pretending to be human. Users should know they’re talking to AI. Pretending otherwise is both an ethical failure and, in a growing number of jurisdictions, a regulatory one.
A useful gut-check before you ship: if a clinician wouldn’t feel comfortable defending a specific bot behavior in a case review, that behavior shouldn’t be in production.
Essential features of a safe mental health chatbot
The key features below are the floor for any mental health chatbot you’d put in front of vulnerable users.
Clear role, boundaries, and user disclaimers
A disclaimer works only if it’s in plain English a user understands in five seconds, placed where decisions happen:
- On first launch: what the bot does, what it doesn’t do, what to do in an emergency.
- Before sensitive flows (mood check-ins, crisis-related topics, anything that could be mistaken for clinical advice).
- In the bot’s persistent identity: it says it’s AI, every time. No “I’m your therapist” cosplay.
- A settings-page footer is not a disclaimer.
- Consistent voice on every redirect to professional help.
Crisis detection and human handoff to therapists or support teams
Crisis detection separates a wellness chatbot from a liability: a deterministic workflow that runs on every message, before any LLM response is generated (§7 Safety covers the deeper architecture). It has to include:
- Risk signals with simple severity scoring.
- A clear escalation threshold that triggers a different response mode, not “more empathetic” replies.
- Hard-coded crisis resources that surface immediately when escalation triggers.
Escalation then needs a real handoff path that holds after hours, and what “real” looks like depends on who owns the bot:
- For practice-owned bots: a live clinician, an on-call workflow, or a warm transfer to your support channel.
- For B2B and consumer bots: crisis resources, an in-network EAP provider, or a callback flow with explicit timing.
- Always: the bot says what just happened (“I’m connecting you to a person”) and what comes next.
Consent, privacy, and data retention controls
Mental health data is among the most sensitive categories you can handle, and users notice when a product treats it casually. Consent and data controls need an owner and a roadmap slot:
- consent that spells out what you collect, how it’s used, who can see it, and how a user revokes it
- separate retention rules for transcripts, mood data, journal entries, and aggregate analytics
Compliance scaffolding is covered in §8 Regulatory Compliance. What a user should be able to do without asking anyone:
- export your data
- delete your data
- reset memory
- end your session
Mood tracking, journaling, and guided exercises
Each self-help tool stays small and easy to put down, with no manipulative engagement loops:
- Structured mood and symptom tracking with simple visualizations (weekly, monthly trends).
- Lightweight journaling with optional AI-assisted prompts that ask what the user noticed and stop short of interpreting it.
- Guided exercises from the §4 library, 2 to 10 minutes each.
- Personalized reminders and streaks, used carefully.
The retention curve you want flattens because people needed the app less.
Admin dashboard, analytics, and clinical review tools
Everything above is user-facing. The rest decides whether your team can run the thing on the Tuesday after launch, starting with the two screens buyers ask to see:
- Conversation review, with every view and the reviewer’s reason written to an audit log you can pull up in under a minute.
- Safety incident dashboards: every escalation event with timestamps, triggers, and outcomes.
Clinical oversight is a staffing decision before it’s a tooling one. Name one clinician before launch who owns review on a calendared cadence and signs off on content changes that touch clinical language.
- Content management: update guided exercises, prompts, and crisis resources without redeploying code.
- Aggregate, de-identified analytics for product owners and B2B buyers, with strict guardrails against re-identification.
How to build a mental health chatbot MVP in 12 weeks
A step by step guide to creating a mental health chatbot MVP: 12 weeks of mental health chatbot development in 6 two-week blocks, each ending in a stakeholder-ready deliverable.
Healthcare app development services matter here because the MVP carries privacy, security, escalation logic, and an audit trail from week 1. Teams that park compliance until week 12 spend week 13 rebuilding the data model.

| Weeks | What you cover | What you walk out with |
|---|---|---|
| Weeks 1-2: define scope, risk boundaries, and success metrics | Use cases (crisis support, daily check-ins, intake and triage, between-session support)
A “do not attempt” list (diagnosis, medication advice, any positioning as clinical authority) Flow maps for your top scenarios (happy path, confused user, angry user, drop-off, re-engagement) Technology direction via the two filters in §11 Platform Choice Pilot metrics (completion rate, handoff rate, safety flag rate, retention) |
Scope doc
Flow diagrams Risk register A first-pass safety policy: what triggers escalation, what gets blocked, what goes to a human |
| Weeks 3-4: design conversation flows and clinical content | 100+ therapeutic responses by intent (validation, reframing, grounding, next-step prompts)
Crisis escalation protocols (when to stop, when to hand off, how to route the user to real-time help) Refusal patterns for diagnosis and medication questions |
Response library
Intent taxonomy Escalation decision tree A review log of approvals, rejections, and sign-offs |
| Weeks 5-6: build the core chatbot architecture | NLP/LLM platform setup
Conversation state model and flow implementation Fallback handling Logging and analytics baseline Admin tooling for content updates One pilot channel (multi-channel too early is a tax) |
A conversation engine in staging that a teammate can break on purpose |
| Weeks 7-8: add safety guardrails and human handoff | The six safety layers in §7 Safety, risk detection through escalation logging
All of it on the working chatbot before any real user sees it |
Safety pipeline wired end to end
Documented escalation routing, 2 AM behavior included Audit-ready logs Clinical sign-off on the implemented safety policy |
| Weeks 9-10: test edge cases, safety, and user experience | 50+ test scenarios (adversarial inputs, slang, ambiguity, “user says nothing useful”)
Clinical review of responses as implemented Edge cases (retries, escalation loops, refusal behavior, safe exits) User acceptance testing with the intended audience |
Scenario test suite
Issue backlog tagged by severity Approved release criteria A “known limitations” statement you’re willing to publish Stakeholder sign-off |
| Weeks 11-12: launch a controlled pilot | HIPAA compliance audit, or a dated memo on why HIPAA doesn’t apply
Terms of service and user-facing disclaimers Support docs for escalation routing, incident response, and on-call ownership Soft launch to a capped beta cohort, with monitored hours, a documented rollback plan, and a daily transcript read for the first 2 weeks |
Pilot release
Monitoring dashboard Support runbook An iteration plan built on those transcripts and the week-1 metrics |
Weeks 1-4 happen on paper, before you write a single prompt or wire anything into a platform, because each piece gets slower to change inside a tool. Scoping runs $5,000 to $10,000, the cheapest place to change your mind, and the content weeks run $8,000 to $15,000, mostly clinician hours. The sign-off belongs to a licensed clinician on your side of the table.
Fallback handling for off-topic messages and repetitive loops decides how week 9 goes. Date the HIPAA call either way, because auditors ask which call you made and when. Reading transcripts daily is the part teams skip, and the fastest way to learn which week-3 responses land.
Safety and ethical considerations for mental health chatbots
If your bot is allowed anywhere near mental health, safety is the product. Everything else is UI.
You’re building a system that will sometimes meet users on their worst day, and the bot saying the right thing isn’t a plan.
Safety protocols and crisis escalation logic
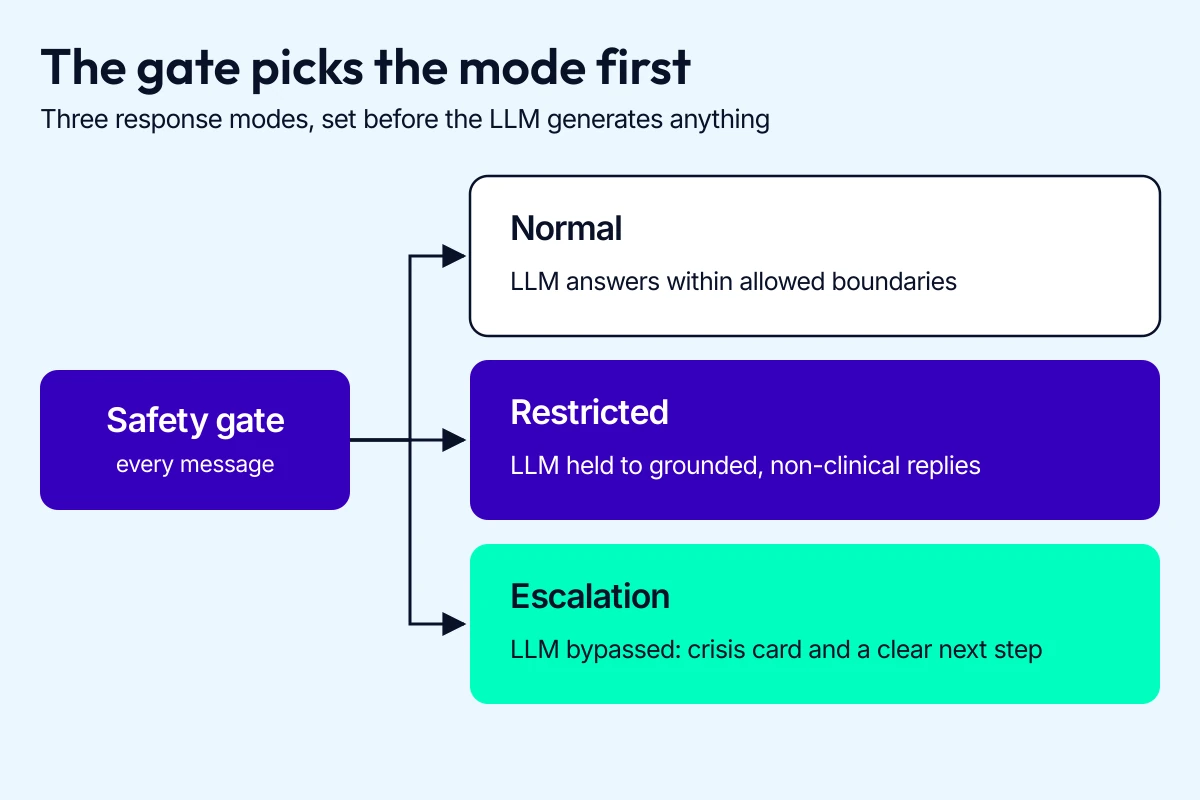
A safety-first mental health chatbot hands control to code you wrote on a calm afternoon the moment risk goes up. Six layers, in the order a message passes through them:
| Layer | When it runs | What it does |
|---|---|---|
| Intake, risk signals, and early detection | Every turn | Keyword hits: fast and dumb, but reliable on obvious phrases.
Intent and phrasing patterns: indirect distress and “coded” language. Sentiment and urgency: the turn where only tone moved. |
| Policy gates and deterministic overrides | Before any response | A rules and policy layer. High-risk conditions switch the mode before the model gets another turn. |
| Response mode selection: normal, restricted, and escalation modes | Set by the gate, before generation | Normal: the LLM answers, but only within allowed boundaries.
Restricted: the LLM is held to a narrow set of grounded, non-clinical responses that never diagnose. Escalation: the LLM is bypassed for a hard-coded crisis resources card and a clear next step. |
| Human-in-the-loop handoff | When escalation fires | Routes the user to a real person or a real workflow, depending on who owns the bot (§5 Features lays out both setups). |
| Guardrails against unsafe output | After generation, before the user sees the text | Validators and content filters block categories such as diagnosis, medication recommendations, and content that reinforces delusional beliefs.
Buy this layer or write it; §10 Tools and Platforms compares the frameworks. |
| Logging, review hooks, and audit trails | Events: every escalation and override
Transcripts: every session |
Logs each event’s trigger and outcome, so next month’s rules beat this month’s.
Keeps transcripts for clinical review only if secured: strong access controls, minimal retention, audit trails for access. |
Detection runs on every turn, so it has to be cheap enough that sampling never looks tempting next to scoring. The policy gate lives in code, with no inference anywhere in the path, because the one decision you can’t afford to leave to a probability distribution is whether this conversation is still safe to have.
The escalation path has no bargaining, no “are you sure?” loops, no confirmation dialogs, and no delays. Crisis hotline options stay in plain view, one tap away in any “unsafe” path. Location-aware routing or a regional selector picks the number; a hard-coded one fits only one country.
Six months of escalation logs will tell you more about how your mental health chatbot actually behaves than any eval set you can buy.
Ethical guidelines for mental health chatbot development
A mental health chatbot without ongoing clinical review drifts from these guidelines, and the first person to notice is usually a user.
- Never diagnose or prescribe. Your bot can reflect what a user brings to it and point at a next step. It cannot label conditions, recommend meds, or claim clinical authority.
- Always identify the bot clearly. Users should understand they’re interacting with software, every time, including the users who would rather not be reminded.
Privacy by design, HIPAA-grade where HIPAA applies. If there’s any chance you’re handling PHI, architect for it from day one.
Informed consent is a content problem before it’s a legal one. Make it explicit and specific; §5 Features covers what goes in it.
Regular clinical oversight is the line item that gets cut first, so set a cadence:
- clinician review of sampled transcripts
- incident triage
- content updates
- a re-read of the escalation rules after every edge-case failure
Regulatory compliance guide for mental health chatbots
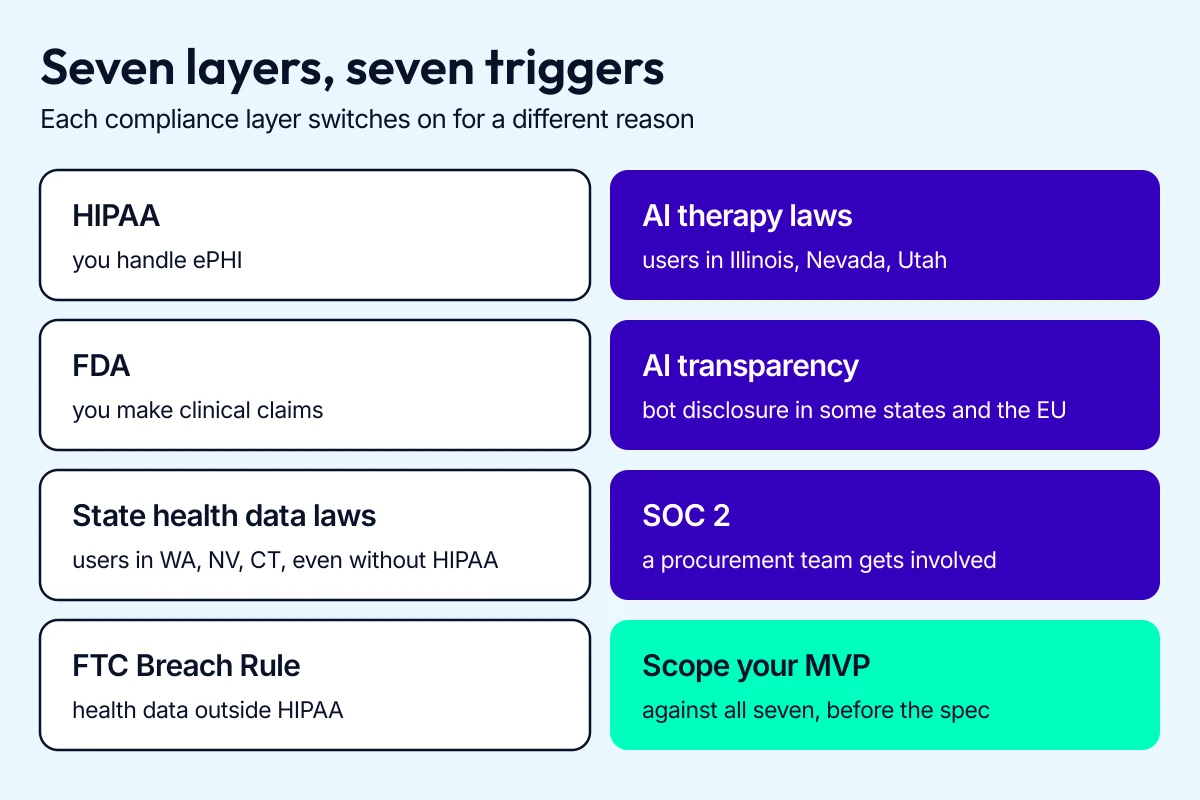
Compliance for mental health chatbots in 2026 stacks seven deep: HIPAA when you handle ePHI, FDA when you make clinical claims, state consumer health data laws regardless of HIPAA, the FTC Health Breach Notification Rule, AI therapy laws in three states (Illinois, Nevada, Utah), AI transparency laws in select states and the EU, and SOC 2 once a procurement team gets involved. Scope your MVP against all seven. Counsel handles the rest.
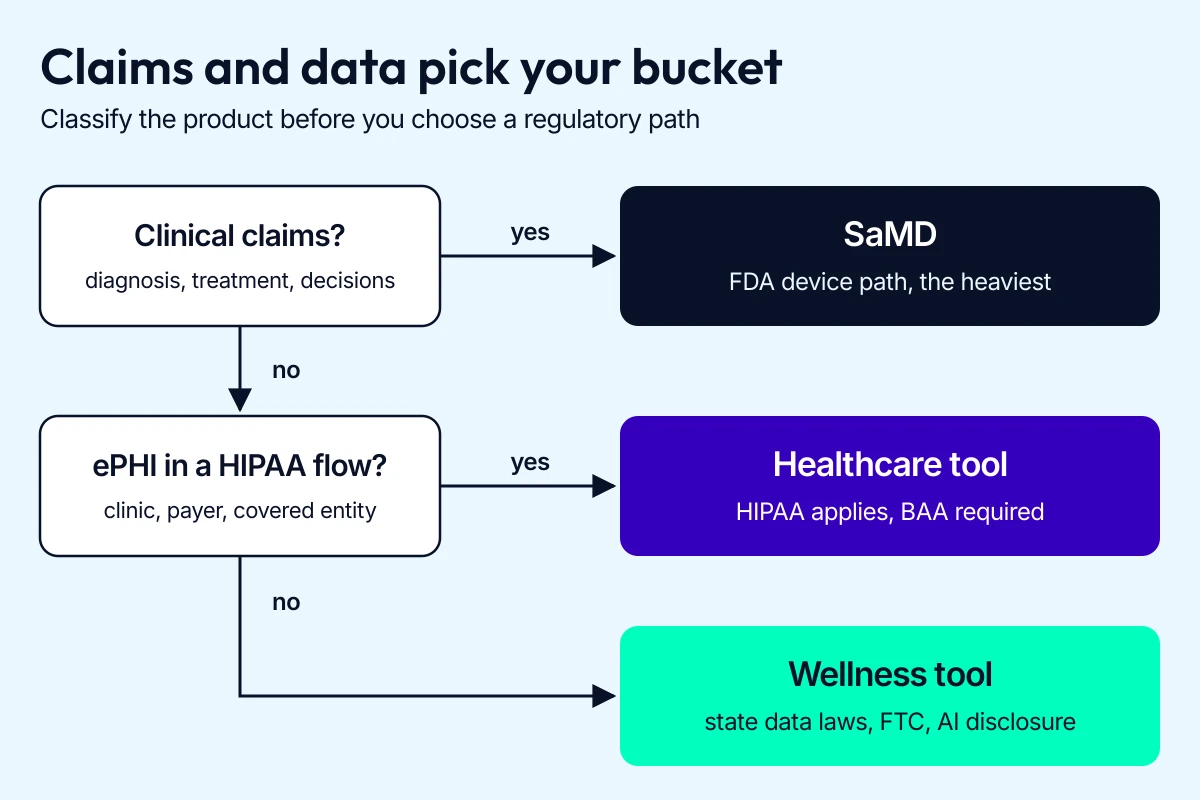
Start with product classification: wellness tool, healthcare tool, or SaMD?
Most teams pick a regulatory path before classifying the product. Three buckets.
Wellness tool. General mental wellness positioning, nothing that reads as diagnosis or treatment. Lighter load: state consumer health data laws, FTC, AI transparency requirements.
Healthcare tool. Used inside a HIPAA-regulated workflow (a clinic, a payer, a covered entity), even if the product makes no clinical claims. Once ePHI flows through your system, HIPAA applies and you need a BAA.
Software as a Medical Device (SaMD). The product makes clinical claims (diagnosis, treatment, clinical decision support) or otherwise meets the FDA’s device definition. The heaviest path.
Selling B2C or to employers as a wellness perk leaves you in wellness territory unless your claims push you into SaMD.
General Wellness: Policy for Low Risk Devices was re-issued in January 2026, replacing the 2019 version. Relaxation and stress management are among the claim areas it enumerates. Its own worked examples put “may help living well with anxiety” inside the policy and “helps treat an anxiety disorder” outside it.
Disqualifiers that void it: references to specific diseases or diagnostic thresholds, prompts that recommend or require clinical action, treatment guidance meant to direct medical management.
A consumer-facing chatbot has exactly two non-device routes: the 21st Century Cures Act software-function exclusion, and General Wellness. Clinical Decision Support is not one of them.
FDA’s CDS guidance, re-issued in January 2026, says software functions supporting or recommending to patients or caregivers rather than to health care professionals “meet the definition of a device,” and that a function must satisfy all four criteria to sit outside device regulation.
HIPAA requirements when you handle ePHI
A mental health chatbot that handles ePHI is a HIPAA chatbot, and HIPAA’s Security, Privacy and Breach Notification Rules all land on it as engineering work.
Technical safeguards
- Encryption in transit (TLS 1.2+) and at rest (AES-256 or equivalent).
- Access controls with least-privilege defaults, MFA for any human accessing PHI.
- Audit logging of every read, write, export and admin override against ePHI.
- Secure session handling with automatic timeouts and re-authentication.
- Backup and disaster recovery procedures you have actually restored from, with the last restore test dated.
Process and governance requirements
- A formal risk analysis and risk management program.
- A named security official, workforce training with sign-off, a written sanction policy, and a rehearsed incident response plan.
- A breach notification process that meets the 60-day requirement.
BAAs go with every vendor that touches ePHI on your behalf, LLM providers included. Get the subprocessor list in writing too, because a vendor who can’t name whose infrastructure your PHI lands on is a gap you inherit.
Practical data handling rules
Enforce minimum necessary at every hop, so the bot, the LLM provider, your support team’s tooling and your analytics stack each see only the fields they need.
De-identify anywhere you can, because aggregate analytics and model improvement run fine on de-identified data. And write a retention and deletion policy, then enforce it in code with a scheduled job you can point an auditor at.
Also Read: How to Develop a Natural Language Processing App
FDA considerations for AI mental health chatbots
Whether the FDA cares about your chatbot comes down to intended use: what you and your marketing say it does, who you let use it, and what happens when it goes wrong.
In the executive summary for its November 2025 advisory committee meeting on generative-AI mental health devices, FDA wrote: “Although the Agency has authorized over 1200 AI-enabled medical devices (encompassing a wide range of AI technologies), none of those AI-enabled devices have been authorized for mental health uses. To date, FDA has authorized fewer than twenty digital mental health medical devices that encompass non-AI technologies.”
The November 2025 committee took evidence on a hypothetical prescription LLM therapy chatbot for depression and concluded current AI cannot reliably detect suicidality or rule out co-occurring conditions. FDA’s August 2026 discussion paper proposes no policy.
Low-risk guardrails if you want to stay in wellness territory
- One wellness position across the product, the marketing site, onboarding and the sales deck, with no therapeutic claim anywhere in that set.
- No personalized treatment recommendations. Psychoeducation and skills practice sit inside the line; anything a user reads as their own treatment plan sits outside it.
- Disclaimers that the product is not intended to diagnose, treat, cure, or prevent any disease, surfaced where users form expectations and not buried in legal pages.
- An audit trail for how you reached “wellness,” marketing review included.
What changes if the product may be regulated as SaMD
In the SaMD bucket, the bar jumps:
- Risk classification on the IMDRF framework.
- A QMS that meets FDA expectations, in practice ISO 13485-style.
- Software lifecycle controls: design history, verification and validation, traceability, change management.
- Premarket submission: 510(k), De Novo, or PMA depending on classification.
- Real-world performance monitoring and post-market surveillance.
Get FDA’s read through a Q-Submission before you build the submission. The Pre-Cert pilot that older write-ups still cite closed in September 2022 and is no longer available.
Any ML-based model will change after clearance, so the Predetermined Change Control Plan decides your roadmap: agreed in the submission, a PCCP lets you ship the changes it describes without filing again. It cannot expand your intended use, and that ceiling sits in the statute, so FDA has no discretion to widen it. The guidance never mentions generative AI, LLMs or foundation models, so PCCP coverage for retraining or swapping a frontier model is open.
Rejoyn (K231209, March 2024, Otsuka with Click Therapeutics) and Motivista (K254038, July 2026, Click Therapeutics), plus Daylight (K233872, August 2024) and Sleepio (K233577, August 2024) from Big Health, are 510(k)-cleared prescription digital therapeutics for depression, anxiety or insomnia. All four are cleared rather than approved, the lower bar, and none is generative AI.
If you’re not certain whether you’re SaMD, get a regulatory consult before you ship. Reclassifying under deadline costs several times more.
State privacy laws and not-HIPAA traps
“We’re not HIPAA, so we’re fine” is the most expensive misread in this space. Several state laws and one federal rule reach this data anyway.
Consumer health data laws
Washington’s My Health My Data Act defines “consumer health data” broadly enough to cover mood data and inferences drawn from chatbot conversations. It has been fully in force since June 2024 and reaches a non-HIPAA chatbot serving Washington users at any size. Expect opt-in consent before collection, a separate consumer health data privacy policy, hard limits on selling or sharing it, and rights to access, correct, delete and withdraw consent.
Washington routes enforcement through its Consumer Protection Act, which is how private plaintiffs get in. Nevada’s SB 370, Connecticut and Colorado give no private right of action.
Two rules hit product decisions:
- Nevada forbids conditioning goods or services on the user authorizing a sale of their health data, so a free tier that trades access for consent to sale is unlawful there.
- Connecticut treats consumer health data as sensitive data requiring opt-in consent, and since July 2026 processing sensitive data alone pulls a company inside its privacy law with no volume threshold.
Colorado is where the trap is. Its AI Act gets described as live everywhere; it never became enforceable, was repealed and reenacted in 2026, and now starts 1 January 2027.
FTC Health Breach Notification Rule
The FTC’s amended Health Breach Notification Rule took effect on 29 July 2024 and reaches vendors of personal health records and related entities, which covers most consumer mental health apps outside HIPAA:
- Affected users get notice within 60 days. At 500 people or more, FTC notice is contemporaneous with user notice rather than inside that 60-day window, and media notice can apply.
- A breach of security includes unauthorized disclosure as well as hacking, so an analytics SDK that leaks health data can qualify with no attacker involved.
- Under Section 5 of the FTC Act, the FTC has brought multimillion-dollar actions against mental health companies over tracking pixels and analytics SDKs that leaked health data to ad platforms. Then in September 2026 it withdrew its 2021 policy statement on this rule. The rule text was untouched, unauthorized disclosure included, but the withdrawal reads as a signal of narrower enforcement, so do not treat ad-SDK sharing as settled grounds for a notifiable breach.
The defense hasn’t changed since the pixel cases: audit every SDK, pixel, tag manager and analytics integration for what it can see, and re-run it on every new dependency.
Telehealth, minors, and special data categories
Telehealth-specific state rules apply once the product sits in a clinical workflow, and mandatory reporting duties for suicide-related data and abuse disclosures turn on jurisdiction and on the clinician-versus-consumer role.
COPPA applies if any part of your product targets users under 13. Substance use disorder records fall under 42 CFR Part 2, stricter than HIPAA on consent and disclosure, so if recovery is your use case, see our guide to addiction recovery app development.
Three states go further than disclosure
Illinois, Nevada and Utah went past disclosure, and all three are already in force. Two of them limit whether a mental health chatbot can operate at all, so market scoping comes before the product spec.
Illinois: a licensed human has to be the one doing therapy
Section 20(a) of the Wellness and Oversight for Psychological Resources Act, in force since 1 August 2025, bars anyone from providing, advertising, or otherwise offering therapy or psychotherapy services in Illinois, “including through the use of Internet-based artificial intelligence,” unless a licensed professional conducts them. “Therapeutic communication” is defined broadly enough to cover offering emotional support, reassurance, or empathy in response to psychological distress, which is what a mental health chatbot does by design.
Section 20(b) binds licensees and bars them from letting AI:
- Make independent therapeutic decisions.
- Interact with clients directly in any form of therapeutic communication.
- Generate recommendations or treatment plans without the licensee reviewing and approving them.
- Detect emotions or mental states.
That last one has no review-and-approval escape hatch. If your product scores sentiment or infers mood, that feature cannot run for an Illinois licensee.
Penalties run to $10,000 per violation. For scribes and note-takers, Section 15(b) requires written, purpose-specific notice and the patient’s consent before AI touches a recorded or transcribed session, and a broad terms-of-use checkbox does not count as that consent. Illinois has no research exemption either: the attempt to create one died in March 2026.
Nevada: no purpose-built systems, and no claiming to have one
NRS 433.567 took effect on 1 July 2025 and bars making available in Nevada an AI system “specifically programmed” to provide services that constitute the practice of professional mental or behavioral health care. That qualifier matters, and intended use is the test.
Representing that an AI system can provide those services is its own violation, so careful engineering that stays outside the prohibition still breaks Nevada law if the landing page says “AI therapist.” Penalties reach $15,000 per violation.
NRS 433.567(6)(b) allows AI built for a provider’s administrative support, and NRS 629.610(4) requires the clinician to independently check AI-generated billing and session-note output. If that is your market, make the review a blocking state.
Utah: you can ship, under disclosure and real limits on the business model
HB 452 has been in force since 7 May 2025, codified in Utah Code chapters 13-72a and 13-77 with an affirmative defense at 58-60-118. A mental health chatbot has to disclose that it is AI before a user accesses its features, again after a gap in use, and whenever asked.
Utah also bars using what a user tells the bot to decide whether to show an ad, what to advertise, or how to present it, and bars selling or sharing a user’s health information or conversation input with third parties.
Filing a policy with the Division of Consumer Protection buys a defense against unlicensed-practice claims, and that policy has to commit in writing to putting user safety ahead of engagement metrics or profit. The defense is narrow: the division can still sue you, and the advertising and data rules apply in full either way.
AI transparency and bot disclosure requirements
2025 and 2026 added a second stack of rules, aimed at the bot itself.
EU AI Act: if you plan European markets
The AI Act sorts systems by risk tier, and for a mental health chatbot the live exposure is the prohibitions, which apply whatever tier you land in:
- Most products fall in the “limited risk” tier: clear disclosure that the user is interacting with AI, a duty in force since August 2026.
- High-risk classification turns on narrow triggers: a regulated medical device above Class I, emotions inferred from biometric data such as voice or face, or a use Annex III names outright, such as a public body deciding who gets healthcare or an emergency patient triage system. Typed words don’t count as biometric data, so a text chatbot with no clinical claim and no such deployment sits outside, though the Commission’s classification guidelines are still in draft.
- High-risk duties were originally due in August 2026. A July 2026 amendment pushed them to December 2027 for the Annex III categories and August 2028 for the medical-device route.
- The prohibitions have bound since February 2025, and the Commission’s prohibited-practices guidance uses an AI well-being chatbot, a therapeutic chatbot aimed at people with mental disabilities, and a companion app built to deepen emotional dependency as its worked examples.
Bot disclosure laws and companion AI rules
Several US states now require bot disclosure, so always identify the bot as AI, in plain language, on first interaction and whenever the user might reasonably forget. California’s SB 1001, in force since July 2019, gets cited most, though it only requires disclosure for bots used to incentivize purchases or influence votes.
California’s SB 243 reaches a mental health chatbot. In force since 1 January 2026, it requires a published protocol for handling suicidal ideation and self-harm, referral to crisis services, and disclosure that the user is talking to AI where a reasonable person would otherwise be misled. Four details decide how hard it lands:
- it applies to all users of a companion chatbot, not only minors, with extra duties for known minors
- it carries a private right of action at $1,000 per violation
- reporting to the Office of Suicide Prevention begins 1 July 2027, so that duty is not yet live
- it exempts customer-service bots, in-game characters, and voice assistants, and nothing else
SOC 2 and enterprise trust requirements
If you plan to sell to employers, payers, health systems, universities, or any decent-sized B2B buyer, you’ll be asked for a SOC 2 report. Procurement requires it even though no statute does, which makes it the cheapest deal-blocker on this list to clear.
SOC 2 is a third-party attestation that you actually do what you say you do for security and (optionally) availability, processing integrity, confidentiality, and privacy. Health systems and payers ask for SOC 2 and HIPAA evidence in one questionnaire and expect both. In mental health chatbot development, employer wellness buyers care most about the privacy and confidentiality criteria, so scope them in.
SOC 2 Type I vs SOC 2 Type II
Most teams do Type I first to unblock early enterprise deals, then Type II as soon as they have a clean operating window.
- SOC 2 Type I: a point-in-time assessment of whether your controls are designed appropriately. Faster and cheaper.
- SOC 2 Type II: an assessment of whether your controls operated effectively over a period (typically 6 to 12 months). This is what serious enterprise buyers want.
The whole compliance posture needs a review at least annually and after every material product change, which is the one line of this that teams skip and then discover during diligence.
Mental health chatbot architecture and tech stack
A modern mental health chatbot runs as a layered system, and each layer has one job you can name out loud. The diagram earlier in this guide shows how the pieces fit.
Core architecture: from user message to safe response
A message takes a five-step route through a production-grade mental health chatbot, and the LLM owns one of those steps, arriving later than the diagrams suggest.
- User input lands: typed text, voice through STT, or a webhook from whatever channel you’ve wired up.
- NLU and risk detection run together on the message.
- The policy and safety gate runs before the LLM, applying deterministic rules rather than model judgment, so the same message gets the same verdict on every run. The gate answers, in order:
- Is this a crisis?
- Is this a disallowed topic (diagnosis, medication)?
- Should we restrict, escalate, or proceed?
- If the gate clears, the request goes to the LLM with retrieval-augmented generation (RAG) and memory context.
- The LLM’s draft response runs through output validators that block unsafe or out-of-scope content, and the validated response goes back to the user. If the gate triggered escalation in step 3, none of that runs: a deterministic crisis or handoff flow runs instead.
LLM layer: response generation and reasoning
Start with a hosted LLM for response generation: fluent, contextually appropriate, on-brand replies. Where you run it changes your cost structure and your compliance paperwork.
- Hosted frontier model. GPT-4 / GPT-4o, Claude, or Gemini. For HIPAA workflows you need a BAA from the provider. What you give up is control over everything between the request and the response, plus per-token pricing that adds up at scale.
- Self-hosted open-weight model. Llama 3, Mistral, or similar. Cheaper per message, and you own the infrastructure, the latency curve, and the safety tuning.
- Fine-tuning on top of either. Approved clinical content and tone examples locked into the weights, at the cost of another tuning cycle per base-model upgrade. Later than most teams plan for.
Keep the model behind a system prompt you’ve stress-tested, retrieval over reviewed content, runtime guardrails, and logging a clinician can read. That wiring is where most of the effort in healthcare AI integration goes.
RAG layer: grounding responses in approved clinical content
Done well, RAG is your strongest anti-hallucination mechanism, because every sentence the user reads traces back to material your clinical reviewers signed off on. Every turn pulls from your own approved knowledge base first. A practical RAG layer for a mental health chatbot is four unglamorous pieces of plumbing.
- A curated content library of clinically reviewed material: psychoeducation, CBT exercises, grounding scripts, mindfulness prompts, escalation copy, FAQ.
- An embeddings pipeline that vectorizes each piece of content into a vector database (Pinecone, Weaviate, pgvector, Qdrant).
- Retrieval logic that pulls the most relevant chunks each turn for the current user state and intent.
- A prompt template that tells the LLM to answer from the retrieved content and refuse when it doesn’t cover the question.
Retrieval is a product problem wearing infrastructure clothes.
- Chunk quality, chunk metadata, the query you build each turn, and whether a clinician ever reviewed what came back all matter more than which vector DB you picked.
- Frameworks like LangChain and LlamaIndex move fast, and the abstraction hides what you most want to inspect: which chunks came back, why, with what scores. Build for retrieval visibility from day one.

Memory layer: what the bot should remember and forget
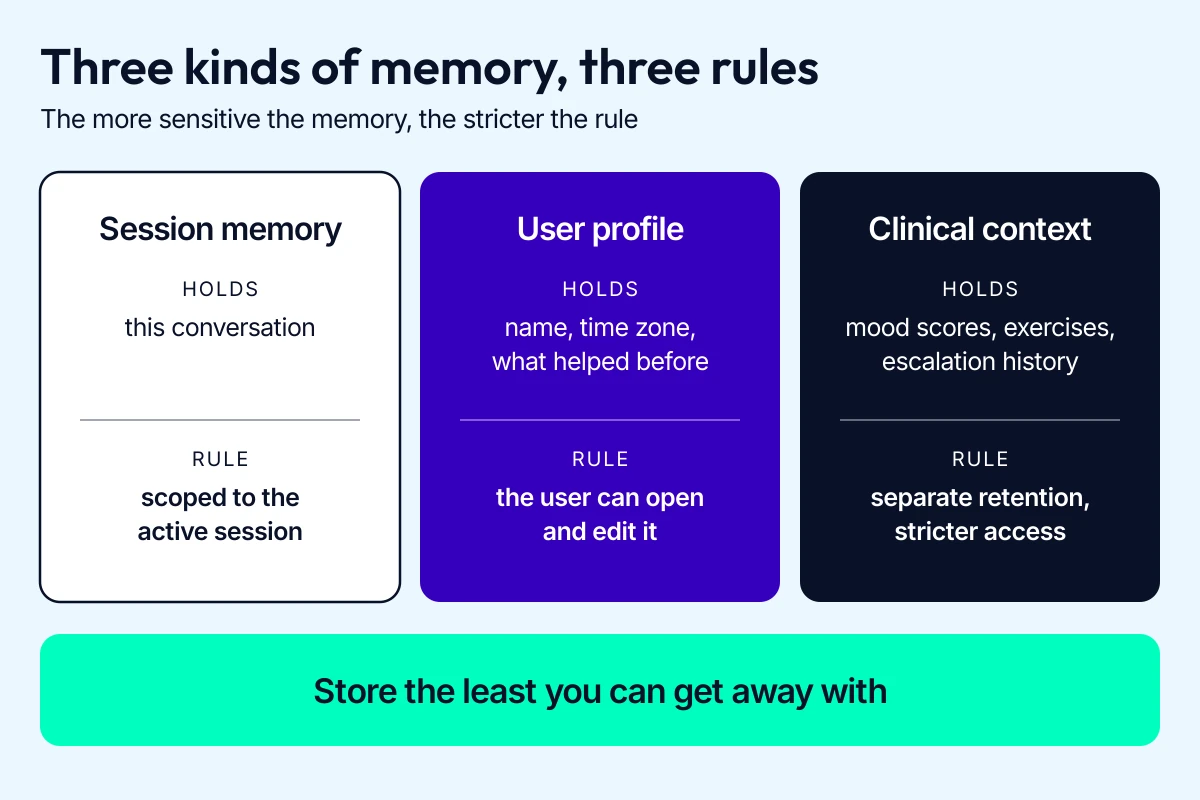
A workable memory model puts different kinds of memory on different rules. Without one, teams remember too little (the bot feels like a stranger every session) or too much (a large pile of sensitive data with unclear retention rules).
- Session memory. What the user said in this conversation, scoped to the active session.
- User profile memory. Stable preferences and high-level context: preferred name, time zone, what’s helped them before. Users can open this and edit it.
- Clinical context. Things that matter clinically (recent mood scores, completed exercises, escalation history). Should be on a separate retention policy from chat history, with stricter access controls.
Store the least you can get away with: memory you don’t have can’t turn up in a discovery request two years later.
Safety and monitoring layer
In mental health chatbot development the safety layer is what clinicians and legal counsel read first, and not one of its six components trusts the model.
- Pre-LLM policy gate. Step 3 of the route above.
- Runtime guardrails. A layer constraining what the LLM can say; §10 Tools compares the frameworks.
- Output validators. Step 5 of the route above.
- Crisis routing. Hard-coded flows that surface approved crisis resources when escalation triggers.
- Logging and audit trail. Every escalation event, every blocked output, every handoff, with enough detail for clinical review.
- Continuous monitoring. Dashboards for safety incidents, drift in model behavior, and unusual conversation patterns.
Read more on conversational AI in healthcare.
Integration layer: apps, EHR, scheduling, and support tools
The last layer, how your chatbot connects to the rest of the world, is light for a wellness app and a meaningful chunk of the engineering work for a clinical product.
- Front-end channels. The surfaces from §1, plus widgets embedded in patient portals.
- EHR and clinical systems. FHIR-based integration so chatbot summaries and risk events land in the chart the clinician already has open. For Epic sites, our Epic EHR integration guide covers the FHIR APIs and the app approval steps.
- Scheduling and triage. Calendar systems, on-call rotations, EAP partner APIs, warm-transfer flows.
- Support tooling. Ticketing, case management, and human handoff routing for non-crisis but high-touch situations.
- Analytics and BI. De-identified pipelines feeding aggregate reporting, with separate views for the product owner and the B2B buyer deciding whether to renew.
Compliance shows up most operationally right here. Every external system that touches PHI arrives with paperwork attached:
- a BAA
- a documented data flow
- a subprocessor list
- retention terms
Looking to design a stack like this without rebuilding from scratch? We help product teams ship mental health chatbots end to end.
Best tools and platforms for mental health chatbot development
Mental health chatbot development in 2026 turns on how much control you need. Six tool categories cover the mental health chatbot builds we see. Nothing on this list was made for therapy chatbot development specifically, so each hands you one piece of the stack and leaves you the rest.
Compare the main platform options: Dialogflow, Rasa, and LLM APIs
| Platform | Pick it when | Hosting and customization | Watch-outs |
|---|---|---|---|
| Dialogflow ES (Essentials) | Simple goal-oriented flows: intake forms, scheduling, FAQ flows, mood check-ins.
Mostly linear logic; fast prototyping on a clean intent/entity model. |
Hosted on Google Cloud.
Low to moderate customization. |
Assumes your product never needs complex state management, multi-step reasoning, or sophisticated memory. Check before committing. |
| Dialogflow CX | Complex branching conversations, where the state machine beats ES.
Multi-step flows with shared sub-flows that must remember what happened last Tuesday. |
Hosted on Google Cloud, with the security and compliance tooling enterprise buyers expect.
Moderate to high customization, heavier than ES. |
Steeper learning curve than ES.
A dialog backbone only: you still bring the LLM layer, RAG, guardrails, and crisis flows. |
| Rasa | High-control, self-hosted chatbots.
Often the only realistic dialog platform when a security review rules out third-party hosting or a data residency rule applies. |
Self-hosted by default, on-prem or private cloud; the audit trail is yours to produce.
Very high customization: open-source Rasa NLU + Core. |
Highest engineering investment.
For generative responses, add a hosted or self-hosted LLM layer on top of the structured dialog. |
| Hosted LLM APIs: OpenAI (GPT-4, GPT-4o), Anthropic (Claude), Google (Gemini) | The default start for most teams shipping a mental health chatbot in 2026.
Flexible, AI-powered support for open-ended conversations. |
Provider-hosted; no infrastructure burden.
High customization: iterate on prompts, retrieval, and guardrails without a retraining cycle. |
BAA coverage varies by tier and endpoint; verify yours.
You build the safety stack around the model. |
| Self-hosted open-weight LLMs: Llama 3, Mistral, and similar | One of the four constraints below forces it, such as strict data residency or fine-tuned weights you own. | Inference inside your own VPC or on-prem.
Very high customization. |
Significant infrastructure and ML engineering commitment. |
| Guardrails frameworks: NeMo Guardrails (NVIDIA), Guardrails AI | Always, around any model.
NeMo for conversational rails, fact-checking, and topic restriction. Guardrails AI for validating outputs against schemas and policies. |
Libraries that deploy with your stack.
High customization: NeMo is programmable through a DSL; Guardrails AI is Python-first. |
A runtime safety layer only, so pair one with a platform above. |
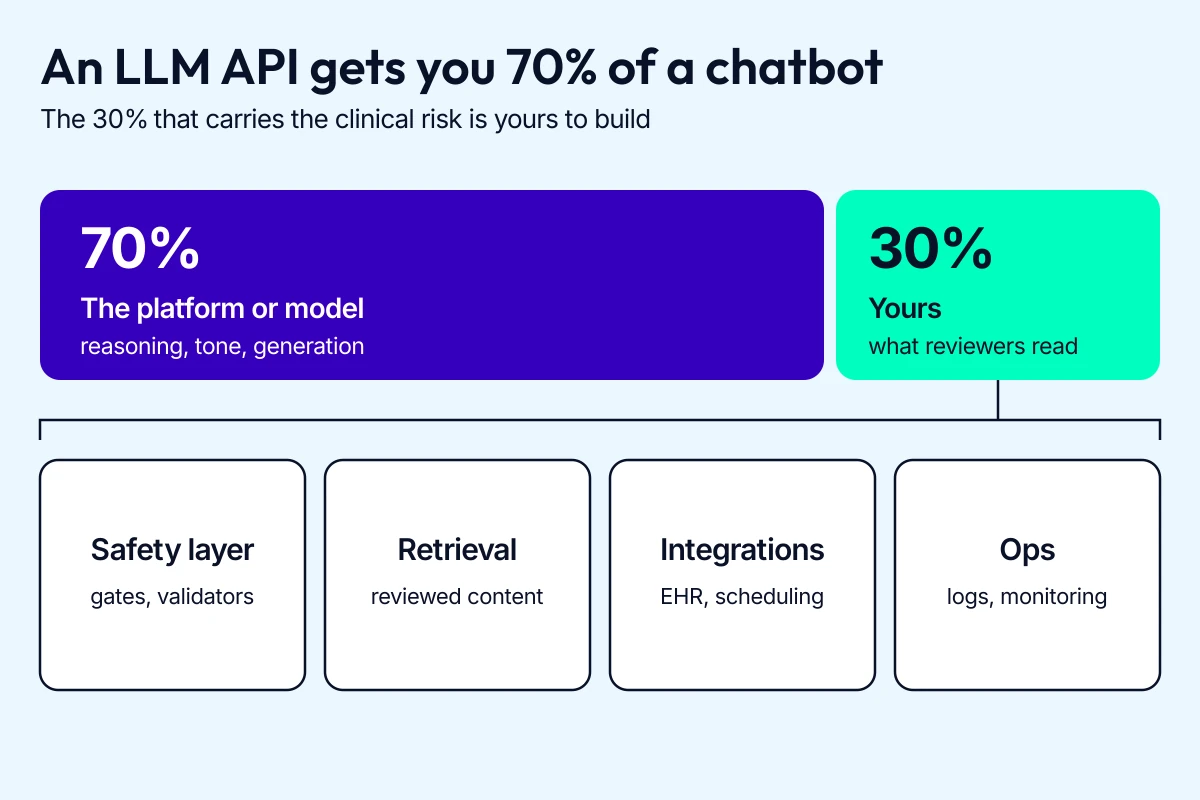
Dialogflow ES lacks every safety layer a serious mental health chatbot needs, so the platform handles the easy half of the conversation while you hand-roll every piece that carries clinical risk. On CX, the visual flow builder keeps your part reviewable: a clinician can look at the actual conversation graph and tell you where stage 3 loses people. An LLM API brings the strongest reasoning and tone available and gets you 70% of a chatbot; safety, retrieval, integrations, and ops are the other 30%.
Related: Medical Chatbots: Use Cases in the Healthcare Industry / How To Build Your Own ChatGPT Chatbot / How is ChatGPT Used in Healthcare
Private or self-hosted LLMs for enterprise control
Stay hosted unless one of four constraints rules that out. Most teams that self-host were forced there by one of these:
- A health system or payer security review won’t approve any third-party LLM provider, BAA included.
- Hard data residency rules no vendor endpoint satisfies: the EU, parts of APAC, regulated government contexts.
- Volume high enough that hosted economics stop penciling out.
- Deep fine-tuning on a tailored dataset, with full ownership of the weights. You can’t rent that from anyone.
Self-hosting costs GPU infrastructure, latency tuning, model evaluation pipelines, ongoing safety tuning, and enough ML engineering capacity to keep all of it honest.
Guardrails frameworks and runtime validators
Whatever model you use, you don’t ship a mental health chatbot without a runtime guardrails layer. Most teams add in-house validators, a thin custom layer on top of a framework or in place of one, and that custom layer is the one you usually end up owning.
NeMo and Guardrails AI handle the generic work well: schema validation, topic restriction. Your clinical policy is a different animal, written by a clinical lead, reviewed by compliance, tuned to the population you serve. It lands as a document somebody has to translate into code, and owning that thin validator keeps the audit trail in your hands, in a format your reviewers already read. Whatever the mix, the layer has to give you:
- Pre-call topic and risk classification.
- Post-call output validation (no diagnosis language, no medication recommendations, no unsafe content).
- Deterministic escalation routing when crisis triggers fire.
Which mental health chatbot platform should you choose?
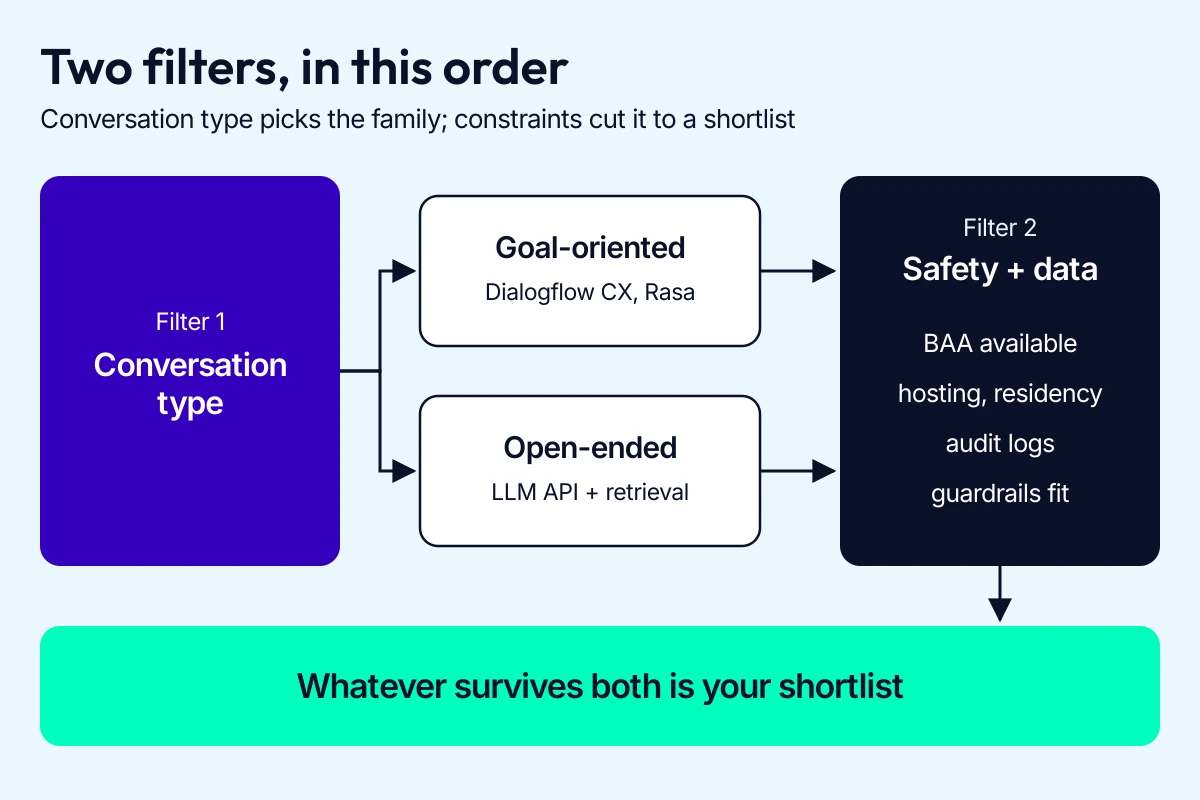
Platform selection for mental health chatbot development runs on two filters, and order matters: conversation type first, then what your safety and data constraints will let anywhere near ePHI.
Start with the conversation type
The conversation type decides which family of platforms you’re choosing from. The teams that get stuck here are almost always pushing two different conversation types through one platform, then wondering why the structured flow keeps drifting. Three questions pin the conversation down before you compare platforms:
- Goal-oriented or open-ended. A structured intake-and-triage flow, where users arrive with a task (book an appointment, finish a check-in, run a CBT module, send a PHQ-9 score to their clinician), wants deterministic branching and a state machine a clinician can read back. Dialogflow CX and Rasa handle that shape well. An open-ended journaling companion wants an LLM API with retrieval behind it and a guardrails layer you assemble yourself.
- How much state the conversation carries. A one-off mood check-in needs almost none. A 21-day program with branching content needs serious state management, and that requirement alone crosses names off your list.
- How much response variation you can live with. Crisis flows, disclaimers, and routing stay deterministic and templated. General psychoeducation can tolerate (and often benefits from) LLM-generated variation, as long as it’s grounded in approved content.
Check safety, data, and hosting requirements
This filter has no give in it. Before you fall for a demo, answer four questions: where your data physically sits, who can read it, what your BAA chain looks like, and what an auditor can pull back out on demand. Four checks settle them:
- HIPAA and BAA availability. If you’re handling ePHI, the platform (and any LLM provider behind it) must offer a BAA on a tier you can actually afford.
- Hosting and data residency. Self-hosted only, VPC deployment, an EU or in-country boundary, an enterprise contract that names the region: any one of those knocks out most hosted-only platforms on the first call.
- Audit and logging support. A year from now, can you reproduce a full conversation, its escalations, the model output behind each turn, and the prompt and model version in force at the time, for a clinical or regulatory reviewer?
- Guardrails compatibility. Does the platform work with the runtime guardrails layer you plan to use, or lock you into its own opinionated stack?
Run whatever survives against the watch-outs in the §10 Tools table.
Between two platforms that both clear the filters, pick the one your team can actually operate week to week.
Mental health chatbot examples: what product teams can learn from them
Of the four best-known names below, Woebot has retired the app that made it famous, and Tess now runs as Cass.
| Product | What it is | Evidence and regulatory signal | Business model and status |
|---|---|---|---|
| Woebot | Tightly scripted CBT mobile app with no open-ended LLM chat: daily check-ins, mood tracking, thought reframing, behavioral activation, psychoeducation | JMIR Mental Health RCT: college students’ depression symptoms fell significantly in 2 weeks (PHQ-9, d=0.44) vs. information-only control
FDA Breakthrough designation, May 2021. Never cleared |
Free consumer app, revenue from B2B partnerships with health systems, payers, and employers; a cleared digital therapeutic was the planned anchor
Consumer app retired 30 June 2025 |
| Wysa | CBT-based AI chatbot: daily check-ins, mood tracking, journaling prompts, guided exercises for anxiety, sleep, and stress
Optional human coaches for users who need more |
Retrospective JMIR study (n=2,061): meaningful improvement in depression and anxiety among engaged users
Claims 6M+ people helped (Sep 2026); its figures vary FDA Breakthrough designation, May 2022. Never cleared |
B2B to employers and health plans, white-labeled or co-branded, plus a consumer subscription
Enterprise is the priority now |
| Cass (formerly Tess) | Enterprise-focused mental health support over SMS and messaging platforms, built into existing healthcare and education workflows
Psychoeducation and emotional support, plus structured check-ins |
Several peer-reviewed studies of university and clinical deployments report improved engagement and self-reported wellbeing
No FDA clearance on record |
B2B contracts with universities, health systems, humanitarian NGOs, and enterprise wellness programs |
| Replika | AI companion app: open-ended chat with a customizable persona, persistent memory, romantic or “deeper” tiers, voice, and AR features | 10M+ downloads, company-reported; regulatory record in the timeline below | Freemium subscription
€5M Italian fine, under appeal |
Woebot: what a rigorous digital therapeutic path looks like, and where it stopped
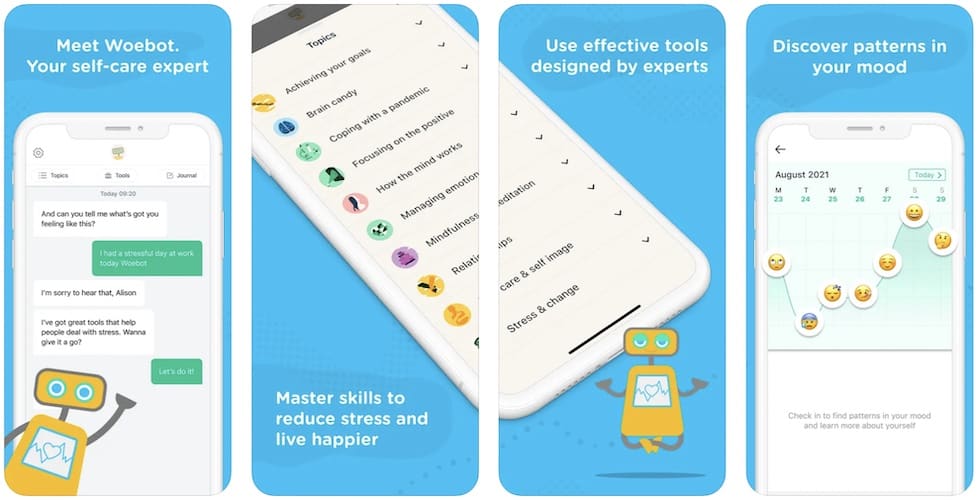
Woebot took the rigorous clinical path and never reached clearance. The FDA designation covered Woebot Health’s WB001 for postpartum depression, and the pivotal trial was terminated in May 2023. Clinical rigor buys evidence, and evidence alone has never made payroll.
Wysa: AI-led support for the “missing middle”
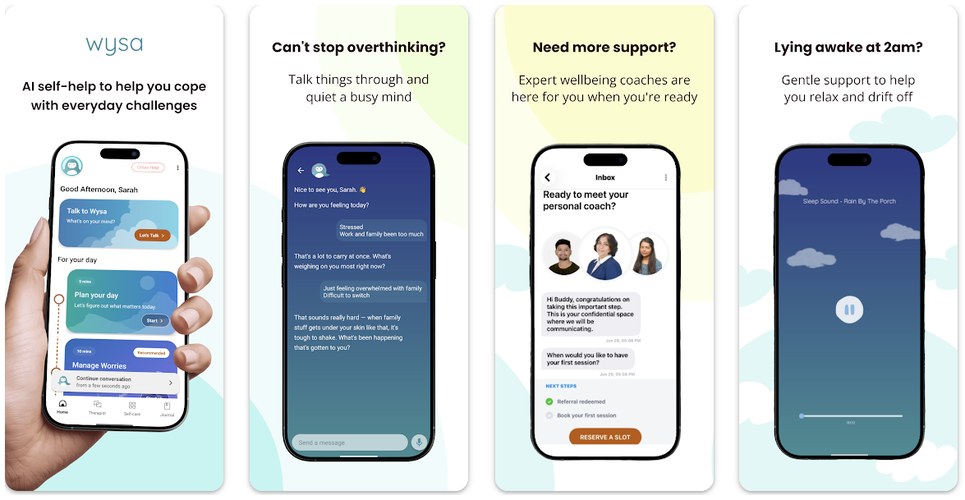
Wysa’s “missing middle” is the people who don’t need a clinic and aren’t fine alone. The piece worth copying is the upgrade path from AI to human coach, wired into the app where the user already is.
The May 2022 designation covers chronic musculoskeletal pain with associated depression and anxiety. Designation means closer FDA engagement during review.
Cass, formerly Tess (X2AI): psychological support over plain text
The channel is the lesson: SMS meets users in the tools they already have, which beats a more polished app they have to install first. Roughly a million people have actually held a conversation with Cass, which is worth separating from the much larger reach figure sometimes quoted.
The failure worth studying came in 2023. The National Eating Disorders Association had deployed Tessa, a support chatbot built on Cass’s technology, and pulled it on 30 May 2023 after it gave weight-loss and calorie-restriction advice to people seeking eating-disorder support. No policy layer stopped it.
Replika: companion AI and the risk of emotional dependency
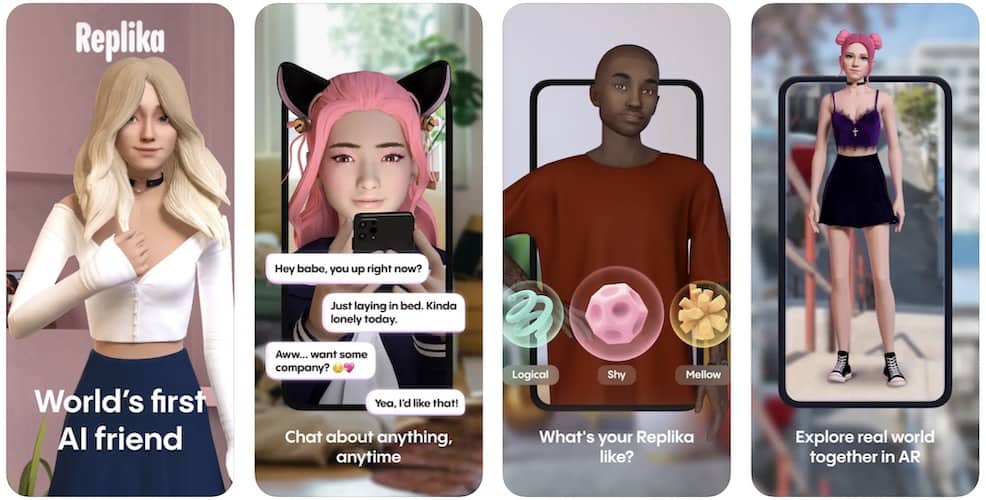
Open-ended chat that remembers you and performs intimacy is where mental health failures, data protection fines, FTC petitions, and litigation land first. Replika is positioned for companionship rather than clinical support, and many of its users treat it as de facto mental health support anyway. The regulatory record is the part to read closely:
- February 2023: Italy’s data protection authority imposes a provisional limit on processing, over child safety and data protection
- June 2023: that limit is suspended once Luka commits to compliance measures
- January 2025: advocacy groups petition the FTC to investigate, and no FTC action has followed
- April 2025: the authority adopts a €5 million fine, announced that May. Luka is appealing, so treat the penalty as contested rather than settled
If you’re building anything like Replika, draw the line inside the product: mental health support that can’t curdle into dependency, and no roleplay as a clinician or as a human.
Also Read: How to build a chatbot
What does a mental health chatbot cost to build?
The bot is the front door. Treat it as the whole build and the real cost hides in data handling, escalation paths, auditability, and after-hours coverage.
Cost follows what you decide “done” means for your first release. Scripted flows with minimal retention are the cheap end. An AI-led experience needs guardrails, monitoring, and a human-in-the-loop fallback somebody is actually on call for.
The ranges below come from our own delivery work on healthcare and behavioral health products, not published survey data, so read them as a scope-to-effort map for sanity-checking vendor proposals.
| Feature Level | Technology Stack | Development Time | Cost Range | Maintenance/Month |
|---|---|---|---|---|
| Basic Scripted Bot | Dialogflow ES | 2-3 months | $15,000-$30,000 | $500-$1,000 |
| Advanced Rule-Based | Dialogflow CX / Rasa | 4-6 months | $40,000-$80,000 | $1,500-$3,000 |
| AI-Powered (LLM + RAG) | LLM API + Custom guardrails | 6-9 months | $80,000-$150,000 | $3,000-$5,000 |
| Enterprise Clinical | Custom NLP + FDA pathway | 12-18 months | $200,000-$500,000 | $5,000-$15,000 |
The focused 12-week MVP at $30,000 to $80,000 has no line of its own: its price straddles the basic and advanced rows, and it holds to the basic row’s timeline by keeping scope to one workflow with basic escalation. Before any of these ranges reach a board meeting:
- The AI-powered tier is where most teams land for a real mental health chatbot today. The safety stack drives the cost: policy gates, runtime guardrails, output validators, audit logging. Model API spend is the small number on that invoice.
- Compliance multiplies whatever the build already costs. HIPAA-ready infrastructure, BAAs with vendors, and SOC 2 readiness add a fifth to two-fifths on top of the base build in our experience, depending on what you already have in place.
- Maintenance recurs for as long as the product is live. Clinical content review, model evaluation, safety incident handling, and compliance refreshes keep running.
Mental health chatbot monetization models in 2026
The monetization model you pick sets your safety requirements, how much of every conversation a licensed human sees, and your sales motion. Building a mental health chatbot is one problem, and getting paid for it is a separate one. Four paths still work in 2026.
How to choose the right monetization model
Four questions decide it, and the first is new. In 2026 it disqualifies more plans than the other three combined:
- Where do your users live? Consumer-facing AI therapy is off the table in Illinois and Nevada, and Utah lets you ship without ad targeting or data resale.
- Who’s the buyer? A consumer at $15/month, an employer paying PMPM for 10,000 employees, a clinic paying per-seat, and a payer want different products.
- How clinical is the product? The closer to the FDA-cleared end, the longer the path to revenue.
- What’s the procurement reality? Each path has its own sales cycle, evidence bar, and security review.

B2B employee wellness: selling licenses to corporations
Employer-sponsored distribution is the most reliable go-to-market path in 2026. Business Group on Health’s 2024 large-employer survey found 77% of large employers reporting increased mental health concerns, and KFF’s 2024 Employer Health Benefits Survey shows 48% increasing mental health counseling resources through an employee assistance program (EAP) or third-party vendors, the procurement channel most B2B products plug into.
The packaging is standard enough to copy:
- per-member-per-month (PMPM) licensing or annual seat-based contracts
- an “AI support + resources” tier for the broad population, higher tiers for therapy access or care navigation
- the enterprise ask: a SOC 2 Type II report, utilization reporting for finance, named data subprocessors, and outcomes language that survives legal review
The employer signs the contract, but the employee has to open the app.
Freemium plus human support: free AI chat, paid care access
This one fits therapist-led offerings: the free AI layer removes what stops people at step one, stigma and scheduling friction, while the paid tier anchors value in a licensed clinician.
- Free: AI chat for intake, psychoeducation, check-ins, lightweight skill practice, and routing.
- Paid subscription: human therapist video sessions (or messaging) bundled with AI support between sessions.
Users who got real benefit free convert far better than cold traffic.
Plan on subscription and referral revenue, and put conversation data on the cost side, because two recent legal constraints shape this model harder than any pricing decision:
- Illinois and Nevada. A free tier that behaves like therapy cannot be offered to consumers there, and no disclosure or consent step fixes it.
- Referral is what survives. Both statutes left open routing the user to a licensed human, and Utah lets the chatbot recommend a licensed professional by name. A shared-revenue arrangement with a practice still stands up.
- Ads and data resale are out. Utah allows only untargeted, labeled ads, and read literally, its bar on sharing conversation input reaches a transcript pipeline to an outside model provider, a reading no court has tested.
A free tier generous enough that upgrading never occurs to anyone kills this model.
Provider or practice SaaS: selling workflow tools to clinics
Selling per seat to licensed practices is the one revenue model open in all three restrictive states. This growing 2026 model sells the chatbot and its admin layer to clinical practices, group therapy clinics, and behavioral health platforms as a workflow tool. The practice owner buys and the clinicians use, so the product needs:
- Intake and triage flows the practice configures itself.
- Between-session support for clinicians’ existing clients.
- Integrations with the EHR, scheduling, and billing already in place.
Pricing is per-clinician seat licensing, predictable and simple to expand, or per-active-client, which tracks usage for swinging caseloads.
Nevada permits AI for a provider’s administrative support and Illinois permits administrative work plus supplementary support under licensed review.
Three product requirements follow:
- A blocking review-and-attest step, because Nevada makes the clinician check AI-generated billing and session notes.
- A per-patient consent artifact before AI touches a recorded session in Illinois.
- A per-state feature flag that ships sentiment scoring off for Illinois customers, since the emotion-detection ban there has no review exception.
Neither carve-out lets the software talk to the client therapeutically, so keep the clinician between the model and the patient.
Per-deal revenue is lower than enterprise B2B, but the cycle is shorter: practices tell you within a week whether the workflow saves clinician time.
Reimbursement for digital therapeutics: the hardest path
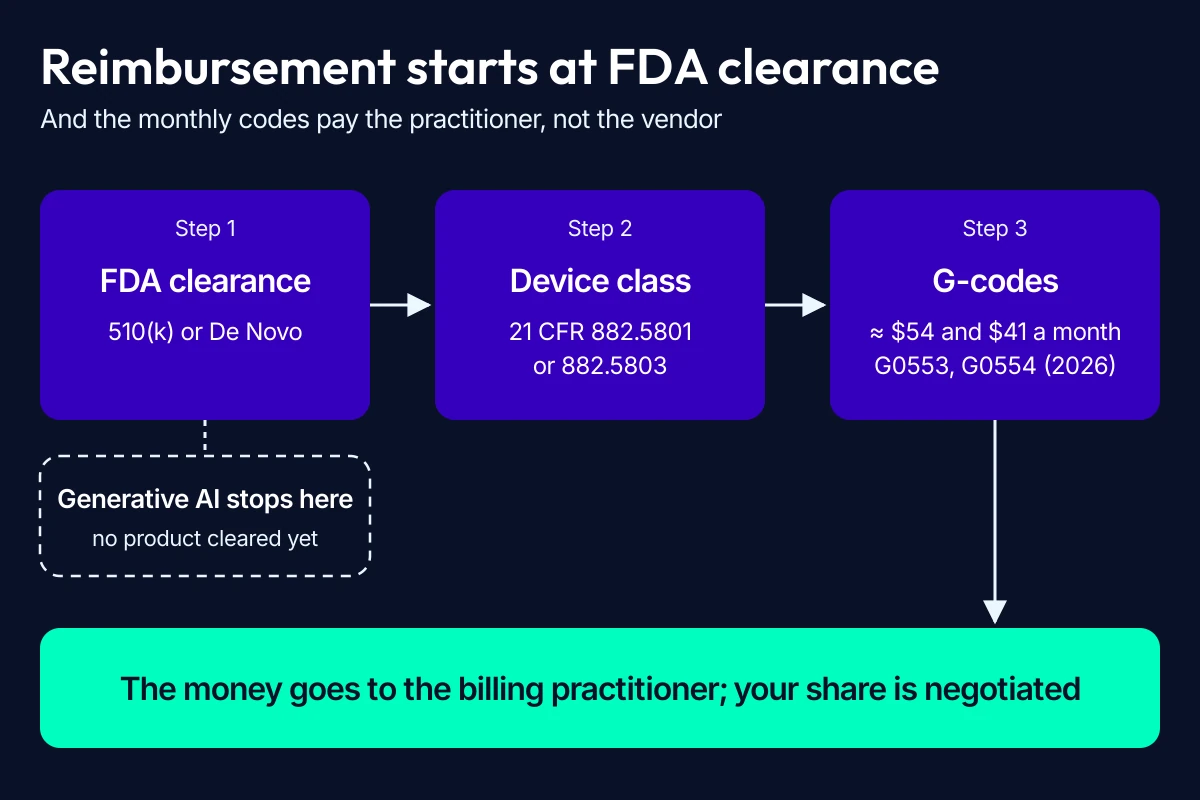
Reimbursement is the highest-moat model once you have it, and without a cleared device on the roadmap it sits below third among levers worth pulling, so fund the next 12 months elsewhere. U.S. reimbursement needs a regulated clinical intervention, usually FDA-cleared, plus a workflow that fits an existing billing pathway. The codes are few and easy to misread:
- Since January 2025, three HCPCS codes cover digital mental health treatment devices: G0552 for the device supply, G0553 and G0554 for monthly treatment management. CMS gated all three on 510(k) clearance or De Novo authorization and classification under 21 CFR 882.5801 or, since January 2026, 882.5803. In the CY2026 physician fee schedule CMS refused to pay for digital tools without that clearance, and refused to extend the policy to four other device classifications.
- A9291 (since 2022) and A9294 (since April 2026) are claim-submission identifiers for non-Medicare payers with no Medicare DMEPOS benefit category, so neither pays under any Medicare fee schedule. A HCPCS code lets a vendor submit a claim, not collect on it.
Six things make this a bad bet for most teams right now:
- For LLM-based products it is closed: no generative-AI mental health product is FDA-cleared, so there is nothing to attach a code to.
- Even with clearance the money lands elsewhere. G0552 is contractor-priced with no published national amount, and the monthly management codes run roughly $54 and $41 in 2026, accruing to the billing practitioner. Your share is whatever you negotiate.
- Commercial coverage is a plan-by-plan fight. A9291 is payable under Highmark’s commercial policy for eight named cleared products and investigational to Premera and LifeWise.
- Remote therapeutic monitoring is no way around it. CPT 98975 to 98978 need a device meeting the FDA definition, and the one CBT code is contractor-priced with no published values.
- Pending legislation is not a plan. The Access to Prescription Digital Therapeutics Act of 2025 would create a Medicare benefit category and has had no action since its May 2025 introduction.
- Time to revenue runs in years.
Which monetization model fits your product?
| Your Situation | Most Likely Model | Why |
|---|---|---|
| Therapist practice or group practice | Provider/practice SaaS or freemium plus human | Buyer and user incentives align; fast feedback loop |
| Consumer-facing wellness app | Freemium plus paid (human or premium AI) | Low friction first step, paid tier monetizes engaged users |
| Employer wellness or EAP-adjacent | B2B PMPM licensing | Clear procurement channel, mature buying behavior |
| Clinical product with FDA clearance on the roadmap | Reimbursement (long-term) plus B2B (near-term) | Reimbursement is the moat; B2B funds the journey |
| Multi-stakeholder clinical platform | Combination of provider SaaS + B2B | Practices buy workflow value, employers/payers buy outcomes |
The strongest mental health chatbot products run two of these in parallel: a B2B employer contract with a freemium funnel, or provider SaaS with a long-term reimbursement play.
How to measure mental health chatbot ROI
If you can’t measure the ROI of your mental health chatbot, you can’t defend it to a B2B buyer or to the clinical leadership who has to vouch for it. Measurement breaks down when you try to improve everything at once, so pick the two or three outcomes that matter most for your product.
The core metrics categories
Most mental health chatbot ROI analyses pull from four metric categories, and a defensible plan touches all four.
- Engagement and adoption. Activation rate, weekly active users, average session length, conversation completion rate, retention at 4 and 12 weeks. Cheapest to collect and easiest to oversell.
- Clinical and wellbeing outcomes. Validated symptom scales (PHQ-9, GAD-7, WHO-5), self-reported wellbeing, sleep quality, completion of evidence-based modules like CBT and mindfulness.
- Operational outcomes. Clinician time saved per client, intake-to-first-session time, no-show and late-cancellation rates, support ticket deflection, escalation accuracy (true positives against false positives in your safety routing). This is where the dollar translation happens for B2B buyers.
- Financial outcomes. Cost per active user, free-to-paid and AI-to-human conversion, customer acquisition cost, lifetime value, downstream healthcare cost trend.
For products in regulated workflows or with clinical claims, the clinical category is non-negotiable. Time horizons lengthen down that list, so agree on what you’re accountable for before anyone builds the dashboard.
A simple ROI framework you can actually use
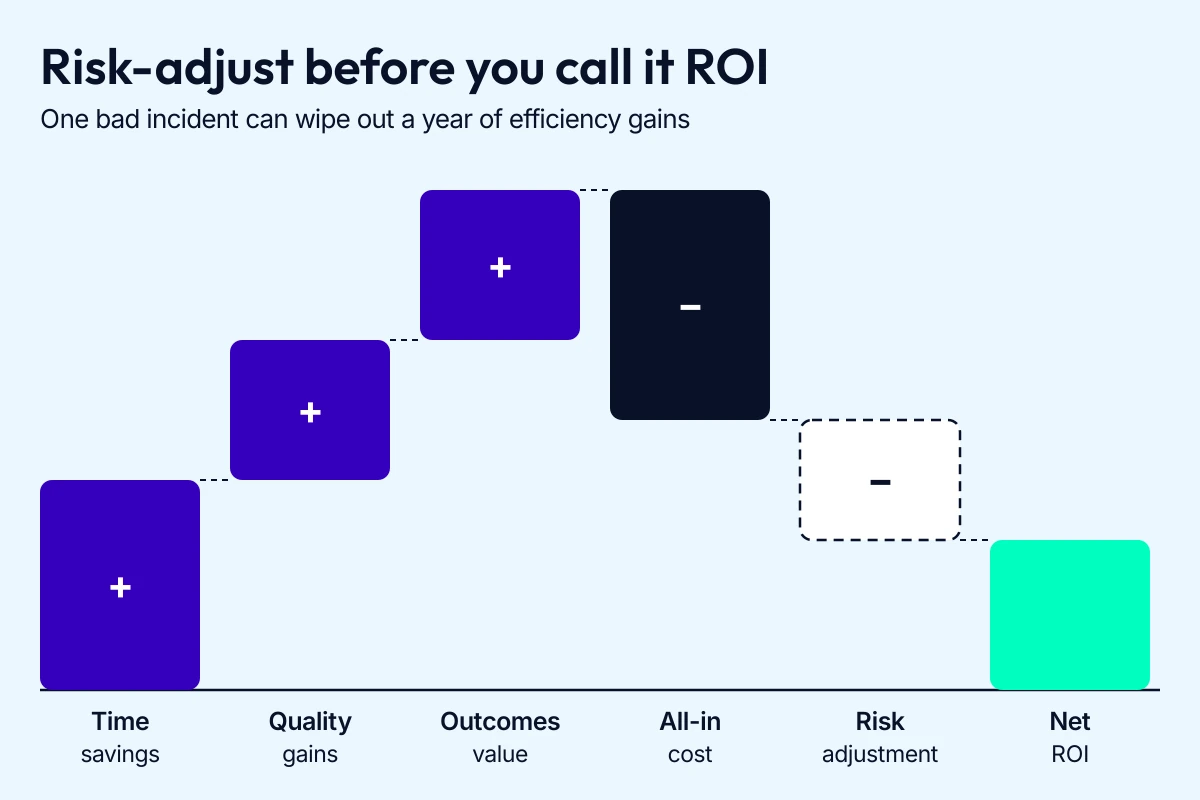
One bad incident can wipe out a year of efficiency gains, so the framework ends with a risk adjustment.
- Inputs. All-in cost of running the chatbot: build amortization, infrastructure, LLM costs, clinical content review, safety operations, customer success, compliance overhead.
- Time savings. Clinician minutes saved per client per week, times hourly cost and client count.
- Quality improvements. The operational metrics above, converted into revenue (more clients served) or cost avoidance (fewer wasted slots).
- Outcomes value. Improved symptoms and fewer escalations to higher-cost care for B2B and payer buyers; retention and conversion for consumer.
Then risk-adjust. Subtract:
- safety incidents
- compliance findings
- brand damage
- the engineering weeks each one eats
What buyers actually want to see
Every buyer reads the same dashboard for a different reason, so lead with the part that pays their bills.
- Therapist practice owner: clinician time saved per week, then no-show rate and client retention, to see whether that time turned into billable capacity. Keep the clinical review path one click from those numbers.
- Employer: utilization, cost per session, employee satisfaction, EAP referral patterns, and any credible signal of downstream healthcare cost impact.
- Payer: clinical outcomes, member engagement, cost-of-care trend, and the quality of the evidence under all of it. Bring a thin evidence section to a payer meeting and the rest of the dashboard stops mattering.
- Consumer investor: activation, retention curves, conversion, ARPU, and CAC payback.
- Clinical leadership: safety incident rates, escalation accuracy, and audit-readiness, read as a risk register.
Those last two sit in the same room, so the safety numbers belong on the growth dashboard rather than a separate deck.
Common ROI measurement mistakes to avoid
- Cherry-picking timeframes. A 2-week clinical outcomes win is interesting; a 6-month one is meaningful.
- Counting non-incremental engagement. If the people using the bot would have engaged with care anyway, you haven’t moved the access needle. Compare against a control or a pre-launch baseline.
- Never reconciling against operating cost. Teams instrument usage and outcomes carefully, then never check either against what the product costs to run. A board member asks the cost per active user, gets a shrug, and the whole dashboard is suspect after that. Reconcile from month one, while the number is still ugly.
- Confusing activity with outcomes. “Users sent 1.4M messages this quarter” is activity. “Users who completed 4+ CBT sessions saw a 4-point PHQ-9 improvement” is ROI.
If you want to discuss your therapeutic chatbot idea with a company that prioritizes your business’s growth besides product development, contact us here.
[This blog was originally published on 8/31/2022 and has been updated for more recent content]
Frequently Asked Questions
What is a mental health chatbot?
A mental health chatbot is an AI program delivering mental health support through text or voice: psychoeducation, mood tracking, self-assessment, coping exercises. It is not a clinician, and good products route users to one whenever clinical judgment is needed.
What tools do you recommend for creating a chatbot?
It depends on conversation type and hosting constraints. Dialogflow CX or Rasa suit structured clinical flows; hosted LLM APIs suit open-ended conversation. On either, layer a runtime guardrails framework and a vector database for retrieval over approved clinical content.
How long does it take to develop a mental health chatbot?
A focused MVP ships in roughly 12 weeks with tight scope: one workflow, basic escalation, minimal integrations. AI-led builds take 6 to 9 months. Enterprise clinical builds on an FDA pathway run 12 to 18 months or longer.
What platforms work best for mental health chatbots?
Mobile-first is usually the right start. Web portals suit employer and clinic rollouts plus admin workflows. Messaging channels work where users already live in chat, but treat them as add-ons riding on a core you own.
How much does it cost to build a mental health chatbot MVP?
Plan on $30,000 to $80,000 for a tightly scoped MVP: one user group, one workflow, basic escalation, minimal retention. Costs climb with EHR work, scheduling, billing, or multi-state rollout. AI-led builds run $80,000 to $150,000; enterprise clinical starts at $200,000.
Is ChatGPT HIPAA compliant for therapy apps?
By itself, no. HIPAA compliance is a property of the whole system rather than one vendor: access control, logging, encryption, retention, contracts. Send the minimum necessary data, and confirm your vendor signs a BAA before any PHI moves.
How do I get FDA clearance for a mental health app?
Start with intended use and claims, since oversight follows what you say the software does. In SaMD territory expect a quality management system, verification and validation, and evidence proportional to risk. Most teams write a pre-submission strategy first.
What is the best AI model for a mental health chatbot?
There is no universal best. Choose on safety controls, consistency, latency, cost, and how the model behaves inside your guardrails. Most teams prototype on two or three frontier models and pick on measured performance in their own risk scenarios.