

Updated November 2026
Healthcare app development cost ranges from $45,000 to $450,000+ across the scoped planning examples below; Topflight’s separate 7-project AI-assisted cohort ran $25,000 to $97,000. Budget the cost to develop a healthcare app against its delivery scope: the tier benchmarks cover 8 to 40 weeks, and broader EHR-connected programmes can take 6 to 12 months.
How much does it cost to develop a healthcare app?
The cost to build a healthcare app follows the scope you’re buying. Use these conventional planning tiers as a first comparison, then check the app-specific examples and the separate AI-assisted project data.
- Simple MVP: $60K to $120K for a focused release with limited dependencies.
- Moderate: $120K to $220K for patient/provider workflows and a small integration set.
- Advanced: $220K to $450K+ for multi-role operations and deeper clinical-system work.
For a focused scope, plan on 8 to 40 weeks; the phase table separates prototype work from a longer full-product programme. The biggest cost drivers are workflow complexity, clinical-system access and the assurance work your customers require.
Key takeaways:
- The AI-assisted cohort is actual Topflight project data. The broader tables are planning estimates for named scopes, so compare inclusions before comparing their prices.
- Keep implementation and ongoing operations in separate budget lines. Vendor access, permissions and review queues can change the calendar even when the feature list stays fixed.
The basic estimate is hours of work × the agreed rate, with separately priced dependencies stated in the quote.
Table of Contents:
- 1. Healthcare app development cost at a glance
- 2. What drives healthcare app development cost
- 3. Healthcare app development cost breakdown
- 4. Healthcare app development cost by app type
- 5. Why medical apps cost more than consumer apps
- 6. How much does AI add to healthcare app development cost?
- 7. Fixed price vs. time and materials: pricing models for healthcare apps
- 8. How long does it take to build a healthcare app?
- 9. How to reduce healthcare app development cost
- 10. Investment vs. returns in healthcare app development
- 11. How Topflight keeps healthcare app budgets in check
- 12. How we built these cost ranges
- 13. Frequently asked questions
Healthcare app development cost at a glance
The planning estimates below span $45K to $450K+. Compare the complexity benchmarks with the app-specific examples; the AI-assisted project data follows the tables.
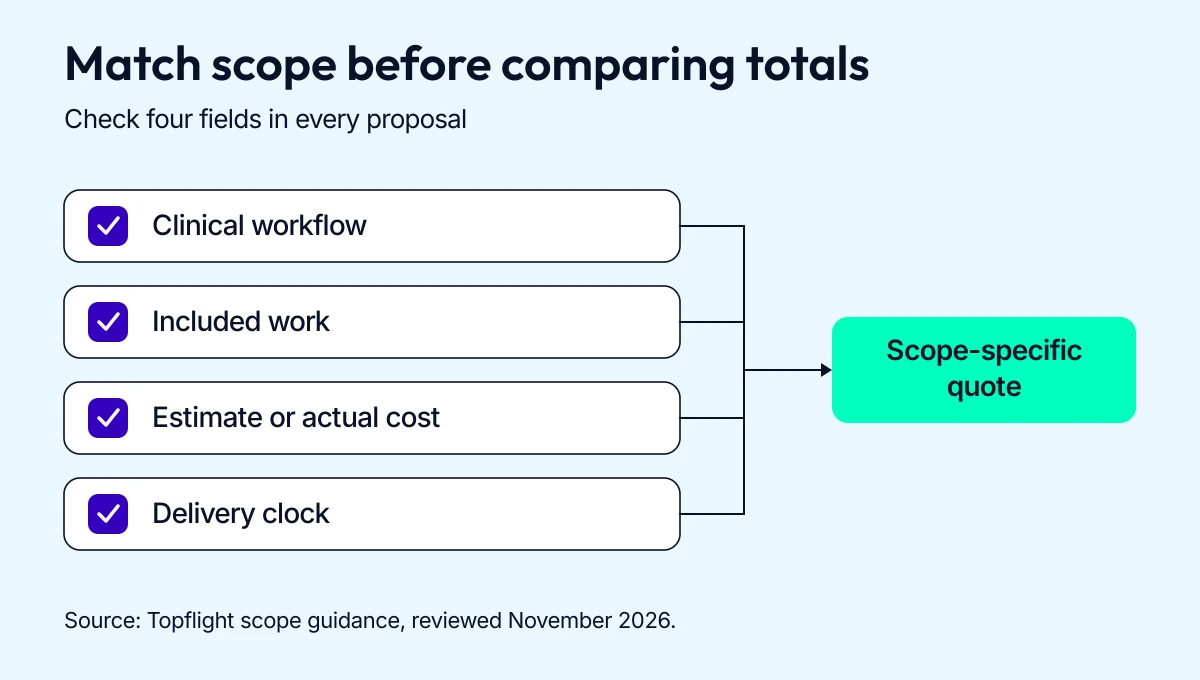
Ask each bidder to state its inclusions and timing assumptions before comparing the totals.
| Complexity benchmark | Scope used for this benchmark | Build estimate | Indicative delivery |
|---|---|---|---|
| Simple MVP | 1 user-facing surface and role; focused tracking or booking; no EHR write-back | $60K to $120K | 8 to 16 weeks |
| Moderate | Patient and provider/admin surfaces; 1 to 2 scoped connections; PHI access controls | $120K to $220K | 12 to 24 weeks |
| Advanced / enterprise | Multiple roles; EHR and revenue-cycle workflows; operational controls and release evidence | $220K to $450K+ | 20 to 40 weeks |
A surface is a distinct user-facing application or portal. A patient app and a provider portal are separate surfaces; iOS and Android delivery also adds platform work, even when they share code.
The app-specific estimates use each source’s own delivery window. A focused consumer MVP can cost less than the simple benchmark, and a clinical workflow can cross price bands or take longer. Where the source gives no matching timeline, the table identifies what needs estimating.
| App type | Typical scope and benchmark relationship | Cost range | Timeline | Source |
|---|---|---|---|---|
| Telemedicine: basic patient/provider product | Video, chat and scheduling; confirm the reusable-platform and vendor scope. Moderate benchmark. | $150K to $200K | Vendor and integration scope dependent | Topflight telemedicine estimate, 2026 |
| Patient portal and engagement | Read-only FHIR, results and reminders. Simple to moderate span; write-back needs a separate scope. | $100K to $150K | Vendor access and scope dependent | Topflight planning estimate, 2026 |
| RPM and chronic care | Device-cloud data, alerts, a care-team console and EHR write-back. Moderate to advanced span. | $180K to $300K+ | 16 to 32 weeks | Topflight planning estimate, 2026 |
| Mental health: HIPAA-grade MVP | A bounded care workflow; distinguish it from a no-PHI wellness tool. Simple to moderate span. | $70K to $140K | 4 to 6 months | Topflight mental-health estimate, 2026 |
| Fitness and wellness: health tracking app development cost | Focused fitness MVP with logging, health-platform sync and reminders. Below/within the simple benchmark. | $45K to $75K | 12 to 16 weeks | Topflight fitness estimate, 2026 |
| Wellness: wearable sync and basic AI | Wearable data and a defined AI feature. Simple price band; a longer source-specific clock. | $80K to $120K | 4 to 6 months | Topflight wellness estimate, 2026 |
| Provider/practice management | Scheduling and scoped eligibility/claims workflows. Moderate starting scope; deeper integrations raise it. | $150K to $200K+ | Clearinghouse and workflow scope dependent | Topflight planning estimate, 2026 |
| Hospital/provider enterprise product | Multiple roles with EHR + RCM and production operations. Advanced benchmark. | $220K to $450K+ | 20 to 40 weeks | Topflight complexity estimate, 2026 |
| Clinical decision support: rules-based | Guideline/rule workflows using discrete EHR data. Moderate benchmark; AI-assistant and medical-device work require their own scope. | $150K to $200K | Scope and validation dependent | Topflight planning estimate, 2026 |
What AI-assisted development costs
Our 7-project AI-assisted healthcare cohort for July 2025 to January 2026 had actual costs of $25,000 to $97,000, with a $49,000 median. These projects involved medium to high complexity and included discovery, design, engineering, QA and project management.
These costs reflect the workflows and delivery methods in that cohort. Reused modules can reduce implementation work.
For EHR write-back, estimate permissions, reconciliation and vendor-review work. FDA Software as a Medical Device (SaMD) work also needs its evidence and lifecycle tasks priced; our medical-device cost guide covers that wider development scope.
Quick cost calculator for healthcare apps
An agreed $170K base plus an additional, explicitly excluded $12K EHR connection gives an illustrative $182K build estimate. The worksheet works when the quote identifies which controls and connections the base already includes.
- Choose the benchmark closest to your user roles and release scope, then replace it with an agreed base quote.
- Mark the compliance controls and vendor connections already included in that base.
- Add separately scoped work once, using the integration and compliance sections below to identify the work.
- Keep the operating and maintenance budget separate from the one-time build total.
If a connection or security task is already funded in the base, it stays there when the worksheet is totaled.
What drives healthcare app development cost
Workflow complexity and the systems your app connects to determine how much engineering it needs. These medical app development cost factors explain the differences between the planning ranges above. Price each piece of work once: a quote that already includes security controls or an EHR connection should identify that scope before you apply any allowance below.
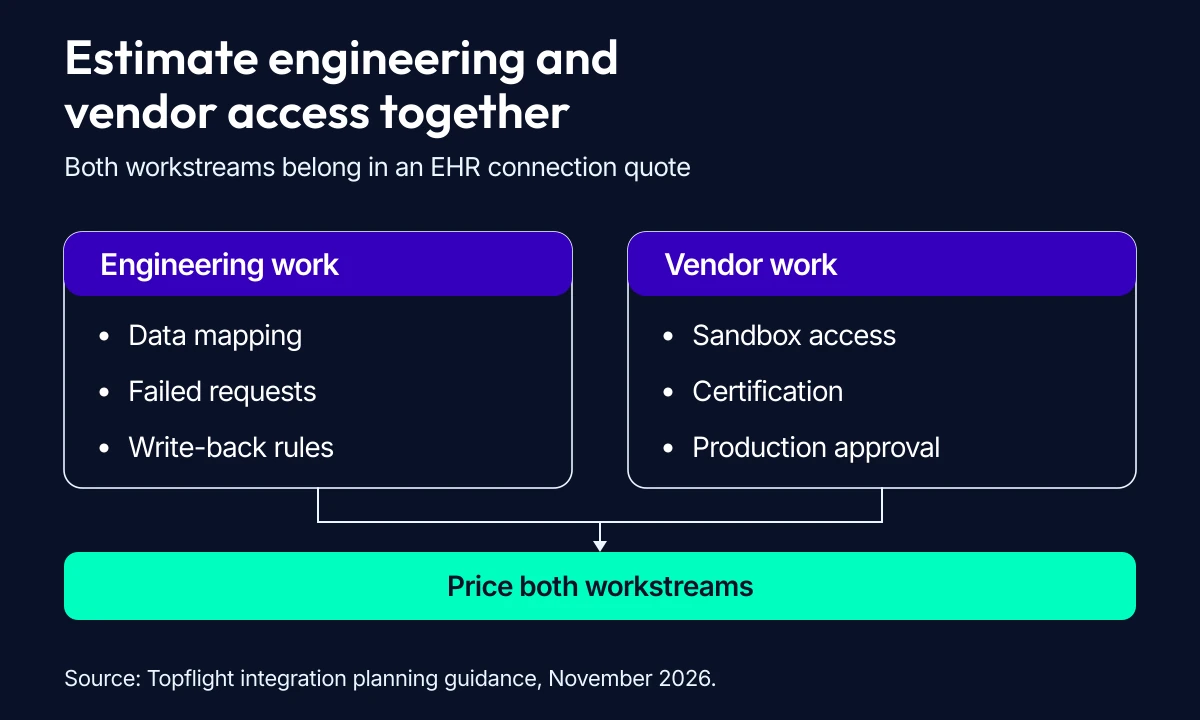
Ask who pays for the vendor work and connection code, and who signs off on each.
App complexity and number of platforms
Each user-facing app adds implementation and testing work, even when the products share a backend. A patient mobile app and a provider web portal have different permissions and workflows; count both when comparing proposals.
Estimate healthcare website app development cost against the workflow delivered in a browser, including its backend and admin screens. The cost to develop a healthcare mobile app also covers device permissions and the work needed to test and submit each store version. Offline records, background monitoring and Bluetooth connections need their own acceptance criteria.
Cross-platform development with React Native or Flutter can share application code across iOS and Android. The saving depends on the device features you need and the amount of platform-specific testing; a shared codebase still needs testing on both operating systems. Choose native development when the required device SDK or background behavior makes that the better fit.
Ask for the design scope separately, with the flows that get prototyped and the accessibility checks each needs. Set aside time for feedback from patients or clinicians.
Our app design cost guide explains that part of the estimate.
HIPAA, FDA and SOC 2 compliance costs
Compliance costs come from the controls and evidence required by your intended use and customer contracts. The following are Topflight planning estimates for scoped delivery work. Ask the estimator to identify the relevant tasks and mark those already included in the base quote.
| Scope | Work covered by the allowance | Planning cost and time |
|---|---|---|
| HIPAA baseline | Business associate agreement (BAA) work, ePHI handling, audit logs, backups and recovery | $10K-$25K; 1-2 weeks |
| FDA SaMD, applicable Class I-II scope | Quality-system planning, risk controls and validation documentation | $25K-$80K; 3-8 weeks |
| SOC 2 Type I/II support | Control mapping, evidence collection and penetration-test fixes | $15K-$60K; 2-6 weeks |
These allowances describe project work. Regulator fees and outside advisers need an explicit inclusion or exclusion in your quote. Ask separately whether an independent examination is included.
Use our HIPAA compliant app development guide to check the implementation scope with your team; buying a HIPAA-eligible cloud service still leaves application controls to build and operate.
As of November 2026, the 2025 HIPAA Security Rule proposal remains pending and the existing rule applies; HHS’s 2026 regulatory agenda targets July 2027 for final action, with no legal deadline.
CMS’s 2024 rule generally starts API obligations in January 2027 for affected payers, with payer-specific dates and exceptions.
FDA’s August 18, 2025 PCCP guidance addresses planned changes to AI-enabled device software; estimate the applicable validation and change-control work with your regulatory team.
EHR and third-party integration costs
EHR integration costs depend on the access you need and the systems involved. Reading records, writing clinical data and coordinating several vendors require different mapping and validation work. These Topflight planning estimates describe integration delivery scope:
- Read-only FHIR access: $8K-$20K per EHR vendor, with 1-3 weeks of implementation work.
- Limited write-back, such as orders or notes: $25K-$60K per EHR vendor, with 3-6 weeks of implementation work.
- A multi-vendor stack, such as Epic plus Oracle Health and a clearinghouse: allow 30-50% integration overhead, with the calculation base stated in the estimate.
Vendor access and certification queues affect the calendar separately from engineering effort. Before accepting a delivery date, confirm sandbox access, permitted data fields, production approval and who owns re-testing after a vendor update.
Our Epic EMR integration guide covers that delivery work. Epic licensing and access charges are separate from the engineering needed to connect your app; use the Epic EHR cost guide to scope those charges independently.
If you’re building the clinical record system itself, budget its modules and data model as product development. Our EHR software development guide covers that larger scope. Keep recurring SDK subscriptions and vendor fees visible alongside implementation work.
Security and privacy costs
Security costs follow who can access each record and what happens when access fails. Topflight’s planning estimates below cover implementation work; assign overlapping compliance tasks to one budget line before totaling the quote.
| Control | Typical work | Planning cost and time |
|---|---|---|
| Fine-grained RBAC and PHI scoping | Role matrices, least-privilege access and data tagging | $8K-$25K; 1-2 weeks |
| Encryption and key management | KMS/HSM setup, key rotation and envelope encryption | $10K-$30K; 1-2 weeks |
| Secure UI patterns | Masking, consent flows and session handling | $5K-$15K; 1 week |
Permissions need to work across the API and the interface. A hidden button doesn’t prevent an unauthorized API request.
Test each role’s access and session expiry. Verify the resulting audit events and recovery from failed requests.
Privacy decisions also change how details appear in notifications and on shared devices. Patients need a way to change their sharing permissions.
Our healthcare mobile app design guide explains those workflow decisions. Budget the testing of these controls with the feature that uses them.
Team location and type: US, nearshore, offshore
Team location changes hourly rates and the time spent getting decisions made. When comparing healthcare app development cost in USA projects with nearshore or offshore delivery, hold the workflow and acceptance criteria constant.
US-based product and clinical-workflow leads can work directly with your buyer’s stakeholders. Nearshore teams provide working-day overlap for implementation and review. Offshore delivery can suit well-specified work, provided somebody owns decisions across time zones and the estimate includes that coordination.
Compare who performs security review and who handles the first EHR connection. Check how much senior engineering time is included. An estimate that leaves those roles open will need another estimate when the work reaches them.
- With an agency, identify the named product and technical leads and their responsibility for production support. Check any subcontractor arrangements.
- With an in-house team or freelancers, include recruitment and management costs. Price any specialist work you need to buy separately.
We’d keep discovery and the first clinical integration close to the people who can resolve workflow questions. Hand off repeatable work after the acceptance criteria are settled. Compare proposals by the cost of delivering accepted scope, including review and rework.
User base size and scalability
More users raise costs when they increase concurrent requests, data volume or support obligations. Monthly active users are a planning proxy; estimate the actual device feeds and query load before choosing infrastructure. These are Topflight planning estimates for additional capacity work where the base design needs it.
| Monthly active users | Architecture work | Planning cost and time |
|---|---|---|
| ≤10K | Single region and basic autoscaling | $0-$10K; 0-1 week |
| 10K-100K | Caching, queues, CDN, asynchronous jobs and push notifications at volume | $10K-$40K; 1-3 weeks |
| 100K+ | Multiple regions, read replicas, sharding and service observability | $40K-$120K; 3-6 weeks |
The bands are approximate. Load testing should settle the capacity you need, while the customer’s recovery and availability requirements determine the redundancy. Keep cloud consumption separate from the engineering allowance, and record whether the initial quote already covers the planned user tier.
Healthcare app development cost breakdown
A healthcare app budget pays for the client applications and the services behind them. The allocation below is a Topflight planning estimate by delivery stage. Its MVP example has 1 EHR connection plus payments, which puts it in the moderate tier in the at-a-glance table.
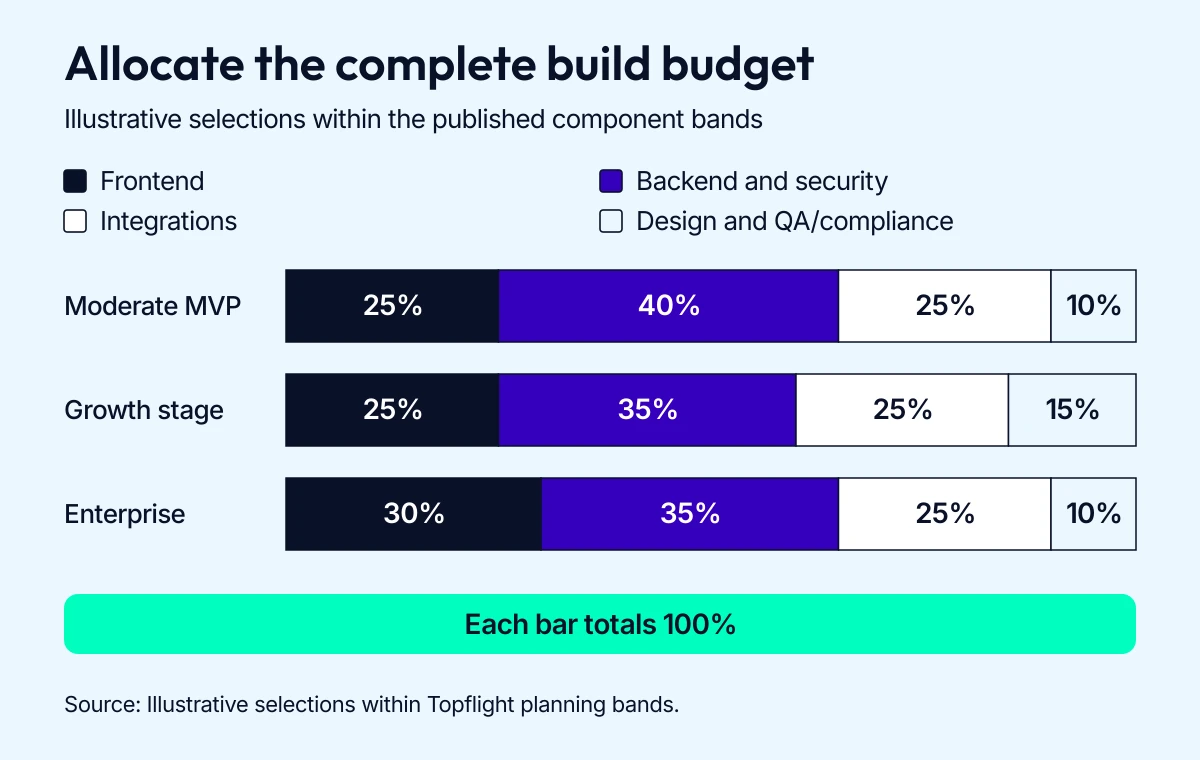
Ask where project management and release work are charged within these quoted component packages.
| Build component | Moderate MVP ($160K-$200K) | Growth stage ($250K-$350K) | Enterprise ($400K+) |
|---|---|---|---|
| Frontend: iOS, Android and web | 25% | 25% | 30% |
| Backend and security | 40% | 35% | 35% |
| Integrations | 25% | 25% | 25% |
| Design and QA/compliance | 10% | 15% | 10% |
These illustrative columns select values within the published component bands and each total 100%. Identify where project management and release work are charged within the quoted packages before using a split for your budget.
For an MVP, keep the allocation tied to a small set of delivery decisions:
- Finish one primary workflow and test its failure states before adding more platforms.
- Give backend access controls and audit events a named owner and an acceptance check.
- Estimate each external connection with its vendor approval and production-testing work.
- Include release preparation, accessibility and support handover in the launch scope.
Hidden costs teams miss
Hidden costs usually come from work left outside the feature estimate: vendor onboarding, production preparation or a recurring service contract. Ask for these items alongside the build quote:
- Sandbox-to-production differences, vendor certification and re-testing after an EHR or payment-provider update.
- BAA and vendor-contract review, access reviews, backup restoration tests, and fixes from penetration testing.
- Recurring SDK subscriptions and video or messaging usage charges. Check cloud logging and other consumption charges separately.
- Store disclosures, accessibility fixes, staff training and the support team’s release documentation.
Record the payer for each external fee and the point when billing starts. A service used during development can become a production subscription before the app has users, so the first-year cash plan needs its start date as well as its monthly price.
If the project replaces an EHR, migration and staff rollout need their own budget. Our EHR implementation cost guide covers that work. Keep it separate from the cost of connecting an app to a system that’s already running.
Maintenance cost after launch
Annual maintenance needs a budget tied to the operating scope and support commitments. The following Topflight planning estimates express recurring work as a share of the initial build; they sit outside the build-allocation table.
| Operating scope | Annual planning allowance | Work behind the estimate |
|---|---|---|
| Consumer-app comparison | 10-15% of the initial build | OS and SDK changes, bug fixes and routine upkeep |
| Healthcare MVP | 15-25% of the initial build | Security patches, vendor re-tests, access evidence and production support |
| Healthcare growth stage | 20-30% of the initial build | Infrastructure work and SDK updates as usage grows |
| Healthcare enterprise | 25-35% of the initial build | Multiple regions, capacity work and contracted service levels |
Ask what the allowance buys. A support agreement should define response times and on-call coverage. State how vulnerability fixes and scheduled compatibility checks are handled.
Cloud consumption and vendor subscriptions also need explicit treatment; check whether they’re included in the agreement or billed separately.
Healthcare support includes access history and release-change evidence that survives a later review. Keep backup-restoration test results alongside it. EHR upgrades and changing vendor permissions can trigger re-testing even when your own feature list stays the same.
Product expansion is a separate decision. Budget a new clinical workflow or another EHR vendor as new scope, then revise the support agreement to cover what you’ve added.
Healthcare app development cost by app type
The master table assigns one published estimate to each stated scope. Use the short descriptions here to decide which example resembles your product, then ask for a quote that names its differences.
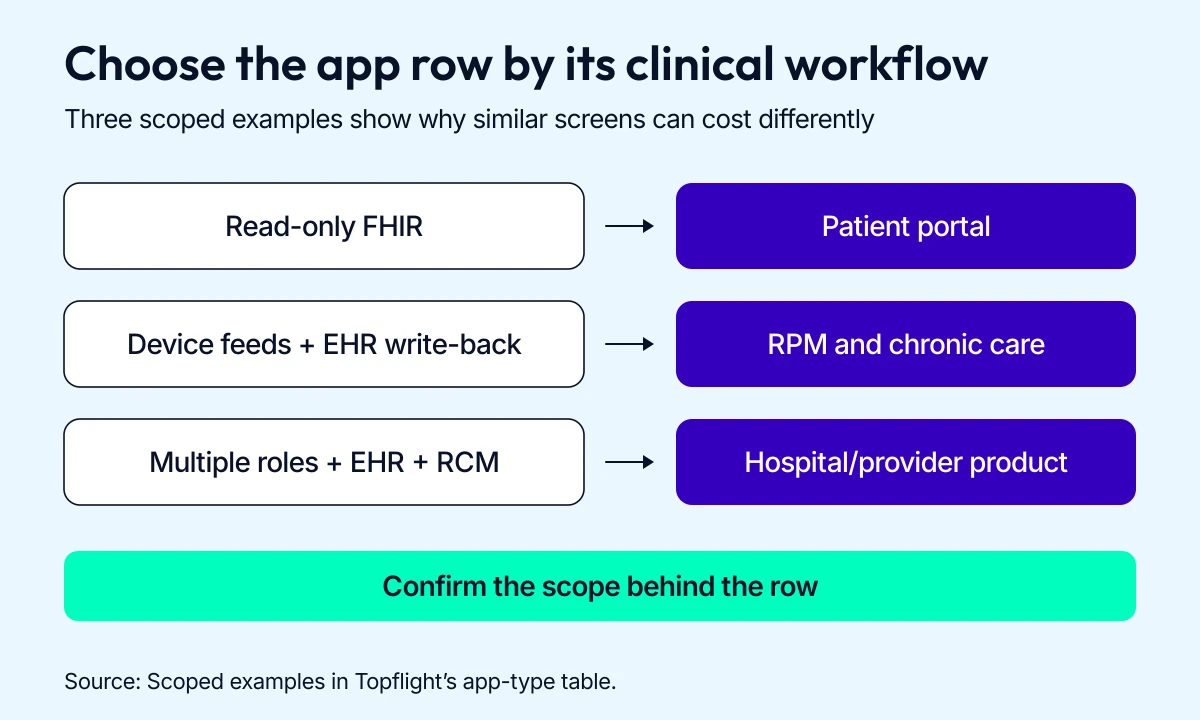
A portal estimate and a hospital operations estimate cover different work even when their screen lists overlap.
Telemedicine app
A basic patient/provider telemedicine product is estimated at $150K to $200K in our telemedicine cost guide (2026). That source ties its opening bands to white-label-platform experience, so confirm reusable components before treating the price as a custom quote.
Video concurrency, patient identity and documentation workflows change the engineering effort. EHR write-back and prescribing add their own vendor dependencies. Compare those inclusions with our telehealth development services before choosing the delivery approach; calendar timing needs the actual vendor and integration plan.
Patient portal and engagement app
A read-only patient portal starts around the $100K to $150K planning band in this guide. Results, appointments and care-plan reminders share one assumption: your team can obtain the required EHR access.
Refill requests or other write-back workflows add reconciliation and approval work. Define which record is authoritative, how a failed request reaches staff, and what a patient can see while a result is pending. Confirm sandbox access and customer review windows before committing to a launch date.
Remote patient monitoring and chronic care app
An RPM/chronic-care build is estimated at $180K to $300K+ and 16 to 32 weeks for the device-data and care-team scope in the master table. Device-cloud access, measurement normalization and alert handling determine much of the work.
Your estimate should identify who reviews an alert and what happens when data stops arriving. That estimate includes EHR write-back. If you support more than one device vendor, include separate failure cases and verification work for each connection before applying a shared budget assumption.
Mental health app
A HIPAA-grade mental-health MVP is estimated at $70K to $140K over 4 to 6 months in our mental-health app guide (2026). Confirm whether your first release supports self-management, therapist-led care or a safety-sensitive workflow.
Each choice changes the roles your app needs, including their permissions and escalation responsibilities. Crisis routing needs a defined operating process, and provider documentation adds a different workload from a private mood log.
Fitness and wellness app
A focused fitness MVP is estimated at $45K to $75K over 12 to 16 weeks in our fitness cost guide (2026); wearable sync with basic AI is $80K to $120K over 4 to 6 months in the wellness guide (2026). Apple HealthKit and Health Connect access, subscription flows and data permissions need explicit scope.
A coaching product with human services also needs the service workflow priced.
Provider, hospital and practice management app
Practice management starts around $150K to $200K+ in this guide, while the separate multi-role EHR + RCM benchmark is $220K to $450K+. Keep those scopes distinct when comparing a quote. Eligibility checks, claims and remittances require different interfaces from scheduling.
Hospital work also needs customer security review and an operational owner for failed transactions. The advanced benchmark covers 20 to 40 weeks; the practice estimate needs a calendar based on clearinghouse access and the customer’s review process.
Clinical decision support and AI assistant app
Rules-based clinical decision support is estimated at $150K to $200K for a workflow using discrete EHR data. An AI assistant needs its model, data and review process priced separately; our AI medical-assistant guide explains the product choices (2026).
Specify the clinician’s review step and how an unsafe output is handled. Agree the validation and EHR-access plan before setting a delivery date, and name who approves the release.
Specialty apps with extra consent rules
Consent-sensitive specialties need an estimate for the roles and disclosures your product actually supports. The table identifies work to scope for each case; a specialty label alone can’t determine its implementation cost.
| Specialty or record context | Scope to establish | Budget implication |
|---|---|---|
| Pediatrics | Age and guardian flows; applicable child-data collection; private minor records | Check COPPA’s under-13 applicability and the child’s actual HIPAA/proxy circumstances. Budget consent, access boundaries and testing for the roles you support. |
| Women’s health | Consumer wellness versus regulated care; sensitive collection and disclosure | Map the entity and data flows before choosing a privacy rule set. Price deletion, disclosure controls and vendor review against the applicable obligations. |
| Senior care | Patient, caregiver and legally authorized representative roles | Scope the caregiver’s permitted access and how authority is verified or revoked. Limited care-related sharing and personal-representative authority have different requirements. |
| 42 CFR Part 2 records | Records from covered substance-use-disorder programmes | Implement the applicable consent and disclosure rules. HHS’s rule permits the required controls without imposing universal record segmentation. |
Federal source checks: FTC COPPA guidance and HHS personal-representative guidance for pediatric and proxy scope; HHS’s reproductive-health rule status for the current effect of the 2025 court decision; and HHS’s Part 2 final-rule fact sheet for the rules whose compliance date was February 16, 2026. These checks were made in November 2026.
Why medical apps cost more than consumer apps
Topflight’s 2026 app development cost guide gives a $50K-$350K planning range for custom apps; a useful average requires a defined scope. Healthcare adds work around clinical data, customer security requirements and system access. Compare quotes for the same workflow and platforms before comparing their totals.

Use the detailed driver sections to price applicable work and avoid adding overlapping allowances.
The budget effects below are Topflight planning estimates for a comparable consumer build. They describe overlapping areas of effort, so adding the percentages together would double-count work. Use the detailed driver sections to scope each allowance.
| Cost driver | Consumer-app scope | Healthcare scope where applicable | Estimated budget effect |
|---|---|---|---|
| Compliance and governance | Store policies and consumer privacy obligations | HIPAA/BAAs, consent and disclosure controls, Part 2 requirements for covered records | 10-20% additional scope for policies, documentation and review |
| Security baseline | Authentication, TLS and application security | Record-level access, key management, incident procedures and control evidence | 5-10% additional build effort, plus operating work |
| Integrations | Social login and standard payments | EHRs, e-prescribing, payer EDI, RPM feeds and vendor certification | 10-20% additional engineering effort, with vendor-dependent timing |
| Data model and auditability | Application records and analytics | Access history, provenance, repeat-safe writes and retention controls | More backend engineering and verification |
| QA and validation | Device, operating-system and browser testing | Clinical failure states, permission boundaries and regulated workflows | 5-10% additional QA/compliance effort |
| Frontend emphasis | A larger share can go to visual polish | A greater share goes to backend controls and integration work | A different allocation of the build budget |
| Release and operations | Routine deployment and support | Customer change windows, approval evidence and on-call procedures | More product-management and DevOps time |
| Ongoing maintenance | OS/SDK changes and routine upkeep | Vendor re-tests, security evidence and contracted availability | Separate recurring allowances in the maintenance section |
For a consumer MVP, Topflight’s published component bands are 35-45% for frontend, 20-30% for backend, 5-10% for integrations and 5-8% for QA/compliance. These selected components leave other work to allocate; ask the estimator to account for the complete budget.
A health insurance app can involve member access, eligibility and claims connections. Price those workflows against the specific payer systems involved. A similarly sized screen list can conceal much more backend work once the app needs to exchange clinical or payment records.
How much does AI add to healthcare app development cost?
Budget an AI feature as implementation and validation work plus ongoing model usage and oversight. Its cost follows the model, the data it touches and the clinical consequence of an error.
A hosted text feature and a custom clinical model have different work lists. Specify the output you need to test, who can act on it, and the point at which a person must review it. Those decisions give the estimator a defined deliverable.

Keep model usage and human review attached to the product’s operating assumptions.
AI features: price validation and running costs
Estimate monthly model usage from the expected request volume and the vendor’s billing units. Add retrieval/storage and the people needed to review consequential outputs to the operating budget.
- Inference: requests × input/output units × the chosen model’s unit price.
- Data preparation and evaluation: representative cases tested against known failure modes, with criteria for clinical review.
- Hosting and access: the exact service and its permitted data flow, with retention configured for that use.
- Monitoring: output quality checks, incident handling and a process for approving changes.
For PHI, include the selected model service’s applicable BAA, contractual review and chosen configuration in the proposal. Request the current eligibility list for the specific AWS, Azure or Google Cloud services you intend to use; document which HIPAA-eligible cloud services handle model inputs, logs and stored outputs. HHS’s business-associate guidance explains the relationship to check (reviewed November 2026).
For a conversational product, our chatbot cost guide covers the scope decisions. A clinical team also needs time to approve the test cases and review failures.
AI-assisted development: price the agreed delivery scope
AI-assisted development can reduce routine implementation work while your team still owns the result. Our actual cohort in the at-a-glance section gives a scoped first-party example of that delivery approach.
Reused authentication or messaging code can shorten implementation. A new clinical workflow still needs design and verification, so have the team identify what it can reuse and what it must build.
For a broader breakdown of product AI spending, our AI-in-healthcare cost guide separates implementation choices from the operating budget.
Fixed price vs. time and materials: pricing models for healthcare apps
Use fixed price when the deliverable and acceptance criteria are settled; use time and materials when the build needs room for clinical or integration discoveries. A hybrid contract lets you fix the price of a defined phase and estimate later work from what that phase proves.
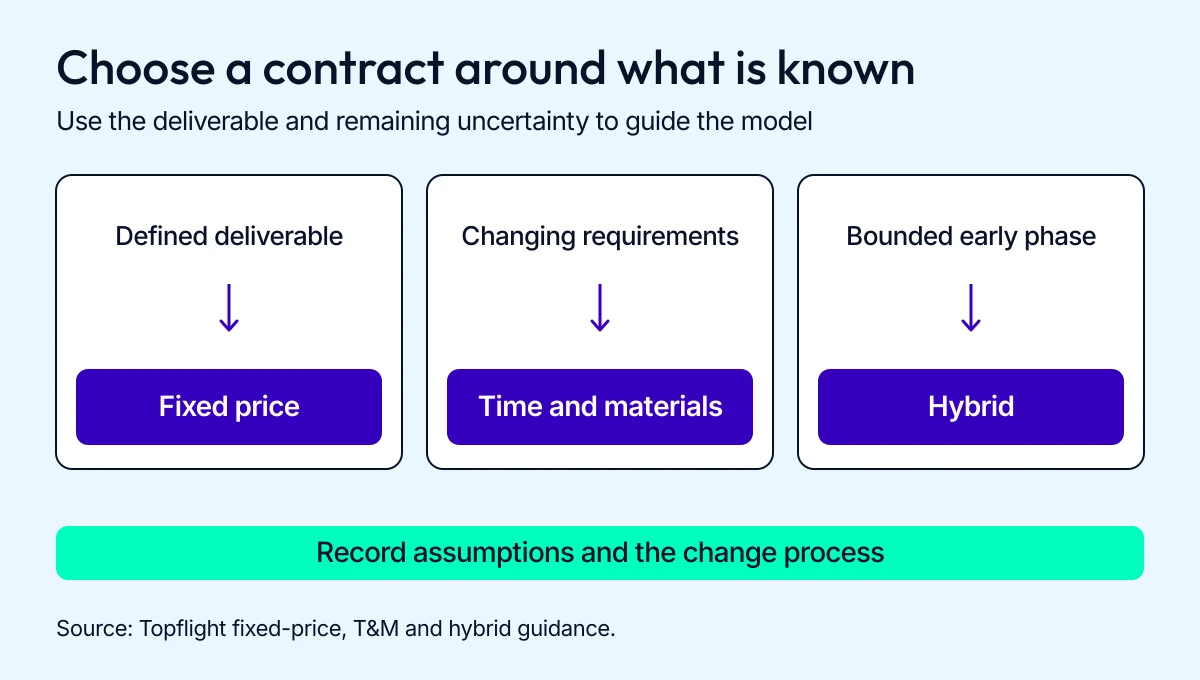
Agree how changed scope is approved and how the remaining estimate is reviewed.
When fixed price works best for healthcare apps
Fixed price fits a bounded release with agreed designs, known dependencies and a written definition of completion. A scheduling utility with an approved workflow is easier to price this way than a product waiting for its first EHR sandbox access.
Read the scope and change process together. The contract should say which screens and integrations the fee covers, who supplies vendor access, and how you approve added work.
If the estimate depends on an existing API supporting a particular field, confirm that field before the build starts.
Time and materials for complex medical solutions
T&M fits work whose requirements will change as you test it with users or connect to clinical systems. You pay for the team’s time and can change priorities between delivery cycles.
Keep that flexibility tied to a spending review:
- Review actual spend against completed work.
- Update the remaining estimate when an assumption changes.
- Approve new scope before it enters the active build.
- Keep a release cut line for the features you can defer.
Ask what you can test at the next review. A working referral flow gives you a firmer basis for the next budget decision than a percentage-complete report.
Hybrid approaches in healthcare app development
A practical hybrid starts with a fixed discovery or prototype engagement, then moves into T&M once the team has tested the main assumptions. You can also fix the price of a well-understood module within a larger evolving product.
For capped T&M, agree in advance which work takes priority as you approach the cap. Vendor dependencies and the approved release scope belong in that conversation. Record the next estimate at the end of each phase so you can decide how much to commit.
How long does it take to build a healthcare app?
A rapid prototype takes about 4 weeks; a full build with EHR integration can take 6 to 12 months.
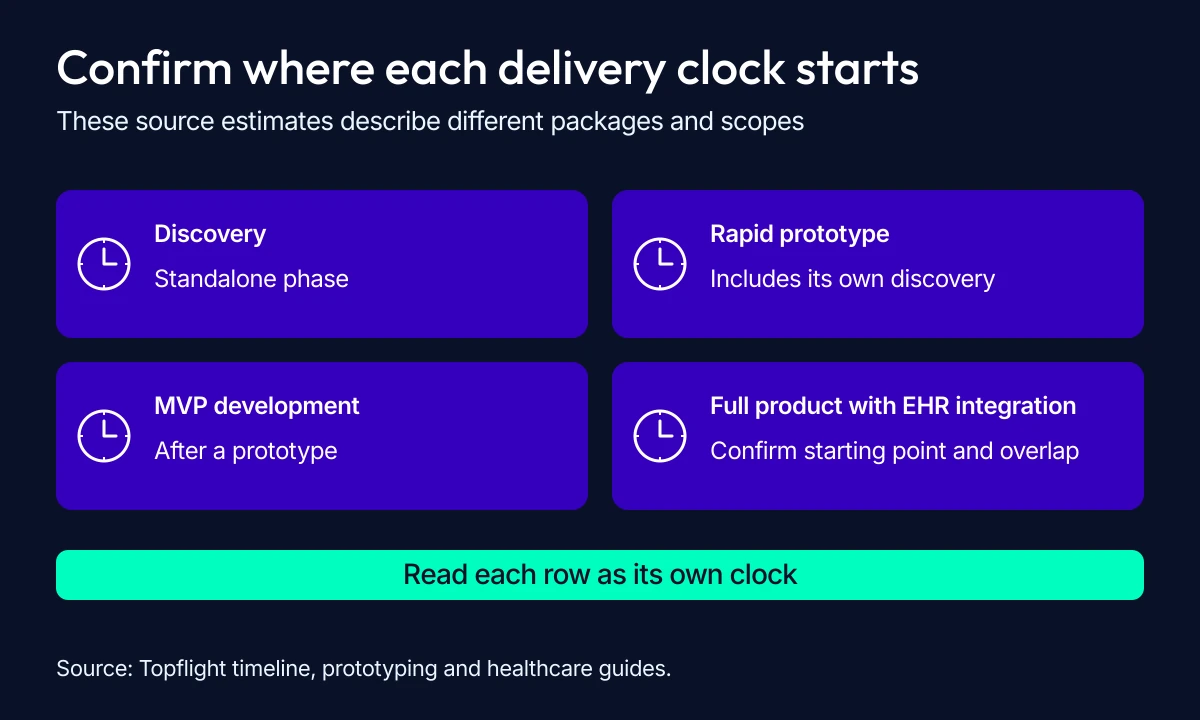
Prototype, MVP and full-product estimates start at different points in the delivery process.
| Stage or delivery milestone | Planning duration | What the clock covers |
|---|---|---|
| Discovery | 2 to 4 weeks | A standalone phase to define users, workflows, scope and risks. The rapid-prototype package can bundle its own discovery. |
| Rapid prototype | About 4 weeks | Topflight’s package includes discovery, design, implementation and testing for a testable prototype. Production release work is scoped in the next phase. |
| MVP development after a prototype | About 13 to 26 weeks (3 to 6 months) | The subsequent development phase in the prototyping service path: production features, infrastructure, security and operational tooling. |
| Full product with EHR integration | About 26 to 52 weeks (6 to 12 months) | The source estimate for this broader EHR scope; confirm preliminary work, integration access and customer review windows in the project schedule. |
These delivery windows have different starting points and can overlap; adding the rows would overstate the schedule. Month-based ranges use approximately 4.35 weeks per calendar month. Allow for external access and approvals when planning the launch.
Sources checked in November 2026: Topflight’s app-development timeline guide for discovery; rapid-prototyping service for its package and subsequent MVP phase; healthcare development guide for the full EHR-connected build.
How to reduce healthcare app development cost
Reduce the first release to a useful care workflow, then reuse components and test the dependencies that could force a rebuild. The best cut is a feature you can postpone while the product still does the job you need to validate.
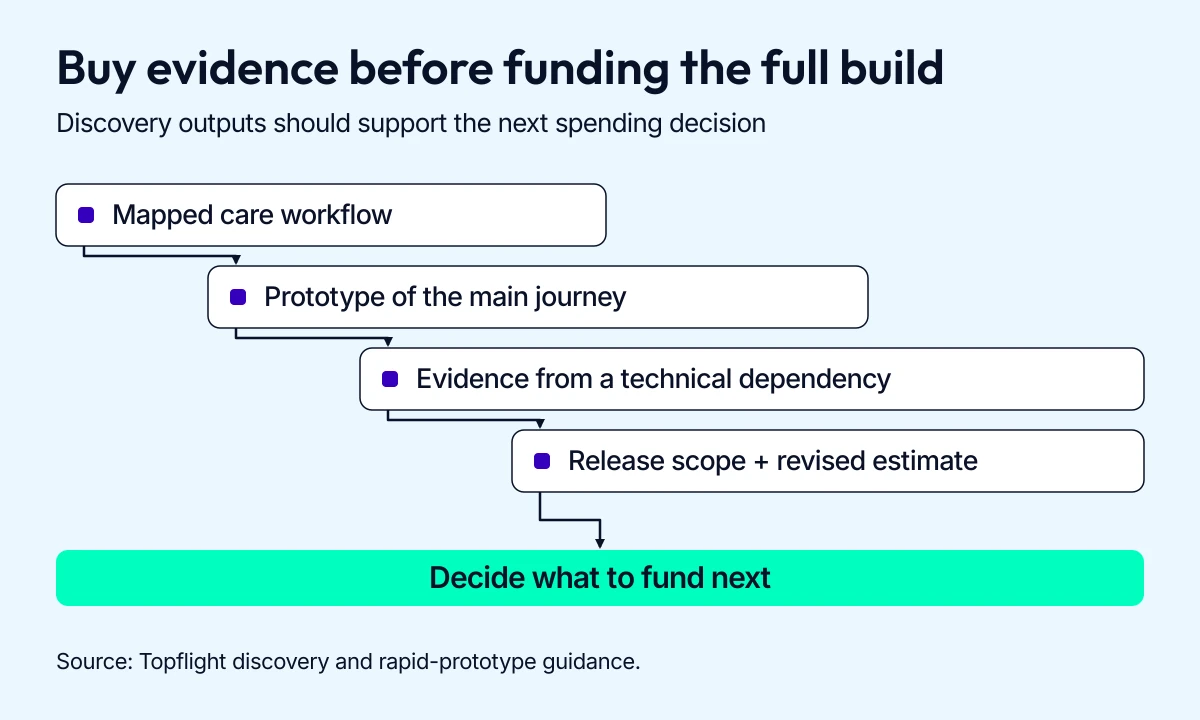
Test the workflow and the difficult dependency while the release is still small enough to change.
Start with discovery and a rapid prototype
Discovery reduces uncertainty in the estimate by checking how the product will work with its users and outside systems. A rapid prototype lets you test the difficult part before you commit to the full build.
Use discovery to check whether a care coordinator can finish the core task and whether the intended EHR connection returns the required information. Confirm which user can see a sensitive record.
Keep the paid outputs specific:
- A mapped care workflow with the important exceptions.
- A prototype of the main user journey.
- Evidence from the highest-risk technical dependency.
- A release scope and revised estimate.
Our healthcare MVP development guide explains how to turn that work into a first release. A prototype can use synthetic data while you test the workflow; production data and access requirements need their own implementation plan.
Use pre-built HIPAA-ready modules, SDKs and white-label components
Reusable account management and messaging components can remove implementation work when they fit your workflow. Check the component against your requirements before putting its saving into the estimate.
Start with its data handling and commercial terms. Check where information goes and which permissions you can control. Price the recurring service at the usage level you expect.
- Test whether the component supports the workflow you actually need, including error handling.
- Confirm which customization and maintenance work your team will own.
Evaluate open-source and commercial options against the same requirements. A white-label starting point can reduce the initial build, while substantial changes to its underlying workflow can absorb that saving. Have the team price the changes before choosing it.
Start with read-only integrations
A read-only connection can keep the first release focused when your users mainly need to review information from another system. Writing orders or notes back into an EHR adds decisions about permissions and how to handle failed or conflicting changes.
For example, a dashboard can first display the records needed for a care-team review. If the next release will update those records, define that future action during discovery so the initial data model supports it.
Check the read-only option with the people doing the work. A release that still forces them to re-enter every result elsewhere may leave too much manual work to justify adoption. Use their response to choose which write actions belong in the first estimate.
Test where failures are expensive
Put testing effort into failures that could expose patient information, interrupt care or require a major release correction. Use the risk review to decide which paths need repeated automated checks and which need a clinician or user to inspect them.
- Check that each role sees only the records and actions it should.
- Test patient matching before information crosses a system boundary.
- Retry interrupted requests and check for duplicate actions.
- Verify what happens when a vendor is unavailable or access expires.
Run those checks as soon as the relevant connection works. Early results give you time to change the implementation while the release is still small. Keep the final test plan tied to the agreed scope so you can explain what was checked before launch.
Investment vs. returns in healthcare app development
Estimate payback by comparing the build and launch investment with the monthly contribution the product can produce. Use collected revenue and verified savings, and account for the recurring costs needed to keep the service running.
Payback months = (Initial build + launch costs) ÷ (Monthly net revenue + verified monthly cost savings).
Subtract ongoing support and vendor charges when calculating net revenue, and count each saving once. During a pilot, measure whether the workflow removes manual steps or releases time for another task. Track billable services delivered as well.
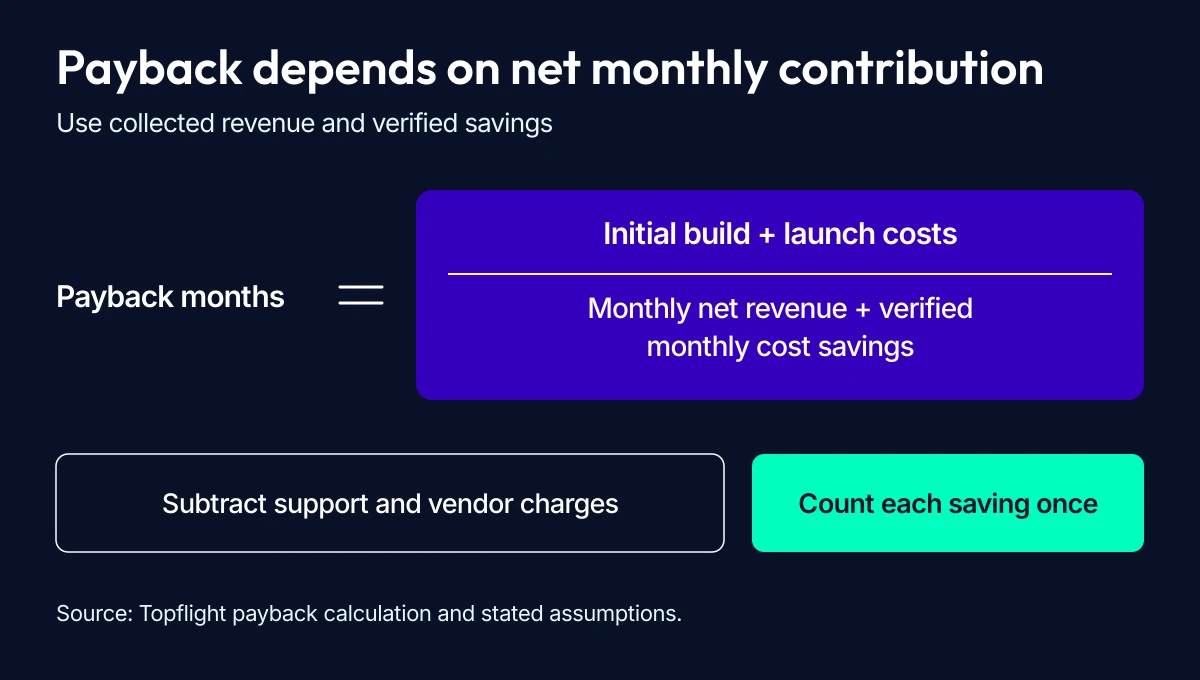
Revise the inputs from pilot results and the timing of actual customer collections.
Topflight’s Dedica Health case study reports a $300,000 annual recurring revenue deal through an RPM SaaS subscription. The product connected home-monitoring devices to a provider dashboard and used text messages for patients, keeping the initial patient experience simple.
For the AlgoRX prescription platform, Specode’s case study reports 7-figure ARR within 6 months of launch. The medication storefront combined eligibility screening with provider workflows and pharmacy routing, work covered by our pharmacy app development services.
These are company-reported revenue outcomes. To estimate your own payback, apply your expected margin and collection timing to the formula, then include the launch ramp. An annual contract signed after a pilot can produce cash on a different schedule from monthly subscriptions.
How the product charges for its work shapes that schedule as much as the build cost does: employer contracts, payer reimbursement and consumer subscriptions each collect on a different clock, so the mobile app monetization route belongs in the same forecast.
Set the baseline before the pilot. For manual follow-up, measure staff time before and after rollout, and check whether any saving releases paid capacity or shifts the same work to another person.
Build the cash forecast around when customers pay and what each service costs to support. Include the first paid clinic sites or, for reimbursed services, collection timing and claims work.
Forecast the first paid month from expected customer start dates and vendor-connection dates, then revise it from actual collections and pilot results. Use those results to decide which next-release features justify their development cost.
How Topflight keeps healthcare app budgets in check
We break a healthcare build into stages with results you can review before funding the next stage. Our Vision-to-Traction System carries that approach through 5 steps, from confirming the product vision to supporting the launched product.
- Confirm the product vision with a visual prototype.
- Demonstrate the value proposition with users.
- Build and refine the MVP.
- Develop and launch the product.
- Deliver traction through continued product work.
The team can revise the scope after testing a prototype or working release with users.
The VTS includes a money-back guarantee. Its published terms set out refund coverage and review points for each plan and stage. Review those terms with the proposed engagement so the commercial commitment is clear alongside the work you expect.
AI-assisted development and reusable healthcare components are part of our delivery approach. The cohort of 7 projects described near the top of this guide had a $49,000 median actual project cost, including discovery and design, engineering, QA and project management.
Ask us to show which components we can reuse and which workflows or connections need new work.
Talk to Topflight about your healthcare app with the workflow and integrations you have in mind. We can work through the assumptions and identify what needs checking before you commit to a build budget.
How we built these cost ranges
We checked the planning estimates in our published healthcare guides in November 2026; the component allocations are illustrative selections within their published bands. The separate AI-assisted range and median come from actual costs for 7 healthcare projects in the July 2025 to January 2026 cohort.
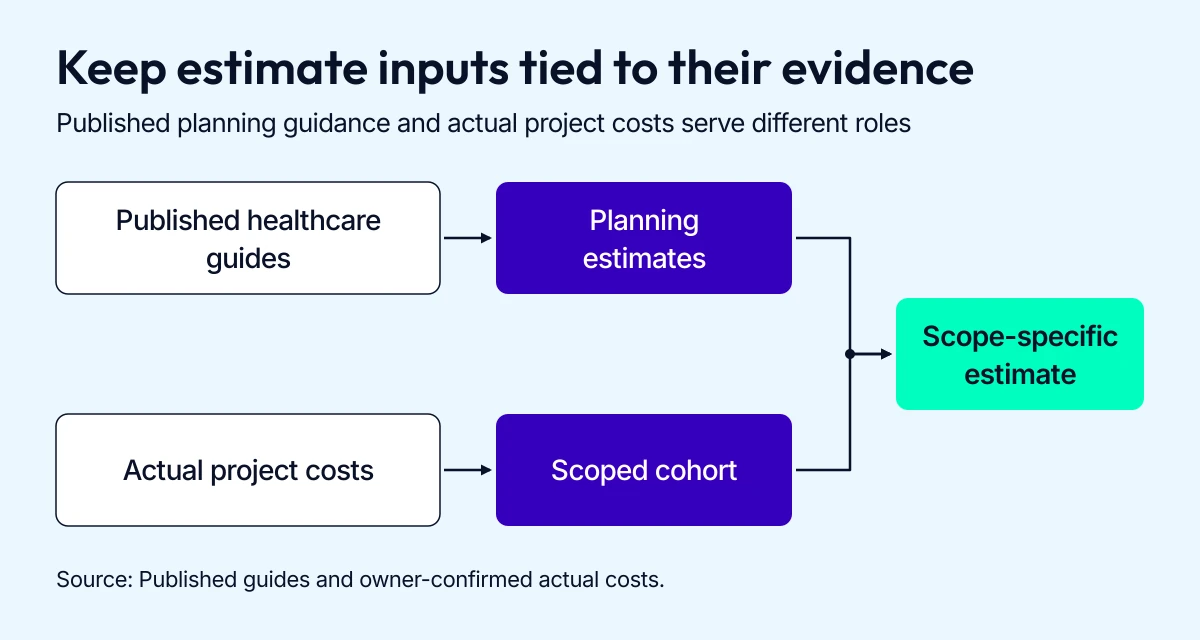
Use the cohort as context and price the new project against its own workflow and inclusions.
Those projects involved medium to high complexity and included discovery, design, engineering, QA and project management.
Frequently asked questions
How much does it cost to develop a healthcare app?
Use $45,000 to $450,000+ as this guide’s planning estimate for conventional healthcare builds, with the scope and exclusions in the at-a-glance tables. Topflight’s separate cohort of 7 AI-assisted projects had actual costs of $25,000 to $97,000; its scope is described in the project-data section.
How much does it cost to build a medical app?
Medical app development cost varies by scope: read-only patient portals are estimated at $100K-$150K here, while the RPM/chronic-care example is $180K-$300K+. Confirm the quoted EHR and validation inclusions against your workflow.
How much does healthcare software cost?
For a multi-role product with EHR and RCM workflows, our planning benchmark is $220K-$450K+. Healthcare software development cost changes with the chosen roles, connections and release requirements; ongoing hosting and support need separate allowances.
How long does it take to build a healthcare app?
A rapid prototype takes about 4 weeks; a full EHR-connected product can take 6-12 months in the cited planning example. Use the phase table’s separate clocks and confirm scope, overlap and vendor access before committing to a schedule.
How much does HIPAA compliance add to app development cost?
Our HIPAA-baseline planning allowance is $10K-$25K for the control work listed in the compliance section. Confirm which of those controls your base quote already includes before adding a separate allowance.
How expensive is AI in healthcare apps?
Price model usage from request volume, billable units per request and the vendor’s unit price, then budget implementation and validation separately. Hosting, monitoring and clinical review also need an operating allowance.
Is it cheaper to build a healthcare app offshore?
An offshore team can quote a lower hourly rate, while the total project cost also depends on coordination and rework. Compare matched scopes and the team’s healthcare integration experience using the team-location section.
How much does it cost to maintain a healthcare app?
For a healthcare MVP, this guide uses an annual planning allowance of 15-25% of the initial build; growth and enterprise scopes have separate allowances in the maintenance section. Agree support responsibilities and vendor-change work before setting the annual budget.