

PointClickCare integration starts with the access route. For a PointClickCare EHR integration, you may use the USCDI Connector, an approved Marketplace connection, or a managed data feed. Each route comes with its own data scope, review, activation, and pricing model.
An EHR PointClickCare integration plan needs vendor approval and facility-level authorization in scope from day 1. Those gates decide which records the app can reach and when production traffic can start.
How does PointClickCare integration work?
Apply through PointClickCare’s Partnerships path and choose the matching program. Build and test in the authorized developer environment. PointClickCare then reviews production access; the customer authorizes the app and facilities.
Key takeaways:
- Route selection comes first because each route changes the data, permissions, review, and activation plan.
- PointClickCare governs FHIR access by resource and operation. Customer authorization and facility activation set the production boundary.
- Public guidance on PointClickCare integration cost and timing covers specific products or stages. Custom partner work still needs a scoped quote.
- Topflight’s adjacent EHR case work spans Epic, athenahealth, FHIR, HL7 v2, and Mirth.
Table of Contents:
- 1. PointClickCare’s reach across long-term and post-acute care changes integration scope
- 2. The access route determines how PointClickCare integration works
- 3. PointClickCare integration risks start before coding
- 4. PointClickCare integration value starts with a bounded workflow
- 5. One workflow should carry through the PointClickCare integration process
- 6. PointClickCare integration cost and timing need product labels
- 7. What PointClickCare customer results show
- 8. Adjacent EHR work defines Topflight’s PointClickCare starting point
PointClickCare’s reach across long-term and post-acute care changes integration scope
PointClickCare describes its current platform as serving senior care providers, hospitals, risk-bearing providers, health plans, and government. For long-term and post-acute care teams, that reach means a workflow may cross an SNF, an acute-care hospital, a payer, and a third-party application.
A long-term care EHR integration sits inside those relationships. For an EHR PointClickCare integration, contracts and enabled facilities matter as much as the interface choice.
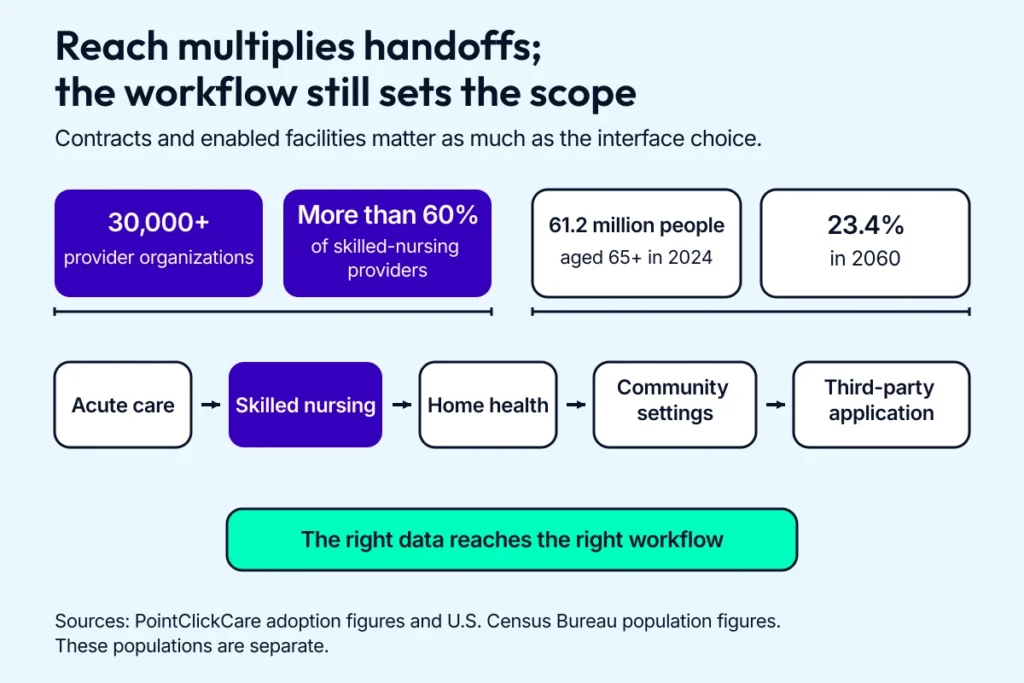
Contracts and enabled facilities turn a large care network into a specific integration scope.
The network is large, and the numbers need labels
PointClickCare’s February 2026 release reports 30,000+ provider organizations, every major U.S. health plan, and 70+ state and government agencies. The company also says more than 60% of skilled-nursing providers use its software.
Those are PointClickCare’s adoption figures. PointClickCare integration quality needs its own measures, such as facility activation time and interface reliability.
KLAS Research’s vendor history records PointClickCare wins from 2020 through 2026. Its current category is Skilled Nursing Facilities / Long-Term Care. That’s product-market context; API fit still comes from the use case and access route.
Demographics increase the handoff load
The U.S. Census Bureau counted 61.2 million people aged 65+ in 2024. Its 2026 aging report puts this group at 18.9% of the population in 2025 and 23.4% in 2060.
As care volume grows, more handoffs will pass among acute care, skilled nursing, home health, and community settings. A PointClickCare EHR integration earns its keep when the right data reaches the right workflow and someone owns exceptions.
Related: How to choose an EHR system
The access route determines how PointClickCare integration works
A PointClickCare API integration runs through an approved partner program. In an EHR PointClickCare integration, the use case decides whether you need the USCDI Connector, an approved Marketplace endpoint set, or a managed feed. Each route has its own test access, operations, production review, and activation rules.
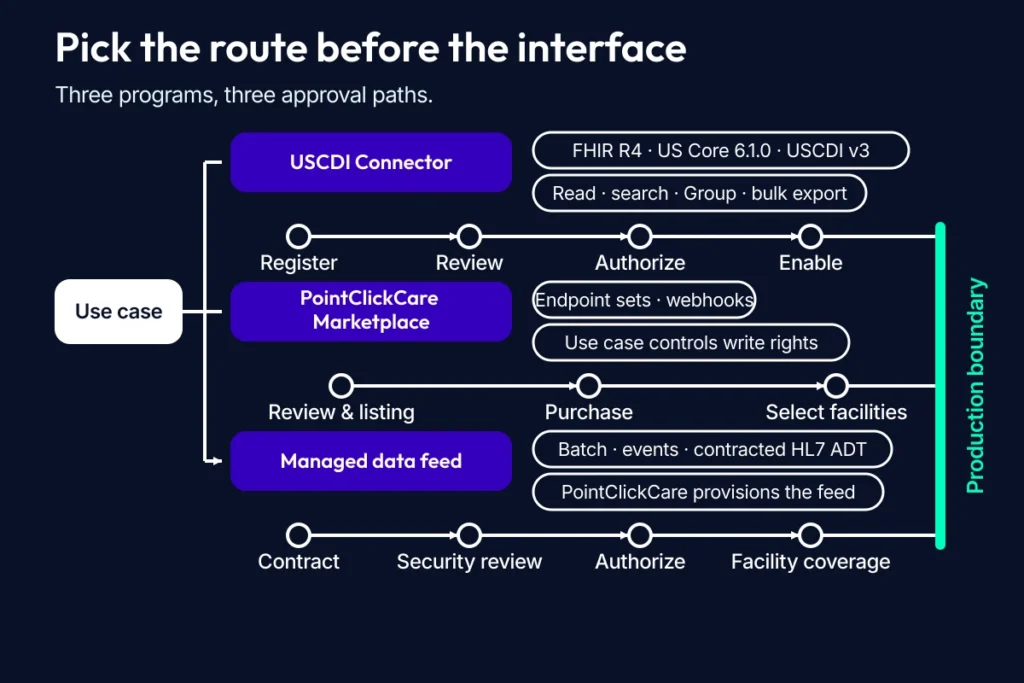
Program choice fixes the approved services, operations, customer authorization, and facility steps in the delivery plan.
Production access starts with the partner program
Budget the approvals as delivery work. PointClickCare’s public developer path runs like this:
- Apply through PointClickCare Partnerships and choose the program tied to the use case.
- Complete the account-approval process and enable 2FA for the developer team.
- Register the app. FHIR development apps can use the shared deidentified sandbox; other routes receive the test access defined by their program.
- Submit the connection for PointClickCare’s production review and complete the route-specific technical or commercial requirements.
- Have an authorized customer purchaser approve the app and select the facilities that will activate it.
A PointClickCare EHR integration schedule should name the owner and due date for every approval in that sequence.
For a PointClickCare Marketplace integration that has already passed review, the activation guide says activation takes 1-2 business days after the partner approves the customer’s activation request. That clock covers activation only. The USCDI route lists a minimum 2-week enablement window once its prerequisites are complete.
The route controls what the app can see and do
|
Route |
When it fits |
Interface and data pattern |
Approval and activation boundary |
|---|---|---|---|
|
Apps that need standardized, scoped USCDI clinical data |
FHIR R4 against US Core 6.1.0 and USCDI v3. SMART on FHIR uses OAuth 2.0. Available operations include reading, searching, Group creation, and bulk export |
App registration and production review precede customer authorization. Facility enablement has a stated 2-week minimum once prerequisites are complete |
|
|
Approved partner products built around a defined workflow or product use case |
Endpoint sets and webhooks vary by product. The approved use case controls operations and write rights |
Partner review and listing precede purchase. An authorized purchaser selects facilities and submits the request; activation follows 1-2 business days after the partner approves it |
|
|
Contracted recurring delivery across a network or care-transition program |
Managed batch or event feeds. PointClickCare’s portfolio includes HL7 ADT delivery where the contracted product supports it |
PointClickCare provisions the purchased feed. Its public sheet doesn’t describe approval or activation, so confirm contract terms, security review, authorization, and facility coverage with PointClickCare |
FHIR access stays operation-specific
Design to the operations PointClickCare approves. As of September 2026, the public specification identifies FHIR R4 with US Core 6.1.0, and PointClickCare’s access policy identifies USCDI v3.
The specification documents resource-specific operations. Reading and searching dominate the catalog. Group creation and bulk export have their own flows, and CCD XML comes through DocumentReference.
SMART on FHIR uses OAuth 2.0. The app approval sets requested scopes plus authentication and certificate details. The approved application record governs the grant flow.
The USCDI terms cover near-real-time queries alongside asynchronous jobs. Paging applies to certain queries, and PointClickCare can throttle an app that threatens platform stability or security, so build monitoring around the endpoints you call. Customer authorization stays facility-specific. PointClickCare’s terms also set U.S./Canada location rules for production PHI and address customer BAAs where applicable.
Approved interfaces set the boundary
Build only against services PointClickCare has approved for the app. Its developer terms bar direct database or HL7 access outside exposed services. The third-party access policy bars unsanctioned scraping, bots, browser extensions, and credential sharing.
PointClickCare excludes Custom Extracts and Data Relay from vendor access paths. It stopped accepting new Data Relay letters of authorization on March 20, 2026. Existing arrangements stay supported until further notice, so the cutoff applies to any new PointClickCare integration architecture.
PointClickCare integration risks start before coding
The decisions that create rework in an EHR PointClickCare integration sit upstream of the code. Your team needs a named source of truth, a resident-matching rule, an access model, and an owner for every production exception.

Put data provenance and facility status beside a named owner so support can trace each exception.
The source of truth decides every write
PointClickCare’s public FHIR specification chiefly exposes retrieval operations alongside documented Group creation and bulk export. Marketplace endpoint sets vary by approved use case.
Record field ownership, direction, approved operation, and conflict behavior before you estimate the build. Do the same for the system on the other end, whether it’s a hospital management system or a medical practice management system.
This matters for medication lists, census status, billing fields, and clinical notes. A PointClickCare EHR integration that reads a resource is a different risk class from one that changes a chart or triggers a downstream event.
Resident matching deserves production-grade tests
A clean API response can still carry the wrong resident or facility context. Test the cases that shared sandboxes rarely contain:
- duplicate and merged resident records across source systems
- facility transfers that change local identifiers or access rights
- code-system, unit, and time-zone differences that alter meaning
- retries and late events that can create duplicate downstream work
Keep provenance with every mapped field. Support teams need to trace a value back to its endpoint, facility, timestamp, and source record when a clinician disputes it.
Every facility adds another go-live
Production approval from PointClickCare is one gate. The customer then authorizes the connection and activates the facilities in scope.
Roles and local configuration can change at each site. So can record volume and rollout order.
Put the facility list beside the technical scope in your EHR implementation plan. A 10-facility pilot and a 200-facility rollout need different support coverage even when they use the same endpoints.
A PointClickCare EHR integration rollout needs one facility-status record that your team and the customer lead both keep current.
PHI location and access belong in the architecture
PointClickCare’s terms limit production PHI acquisition, access, use, and disclosure to Canada or the United States. A developer may also need a BAA with each customer that activates the app. Those constraints belong in cloud hosting, logging, support-access, and vendor reviews from day 1.
Use the smallest practical scopes and keep human authorization visible in the workflow. Our HIPAA app development guide covers the wider vendor-chain and audit questions that sit around the PointClickCare contract.
PointClickCare integration value starts with a bounded workflow
A useful EHR PointClickCare integration starts with one measurable workflow, such as reading an active medication list during reconciliation. A facility-wide “better care” target is too broad to measure.
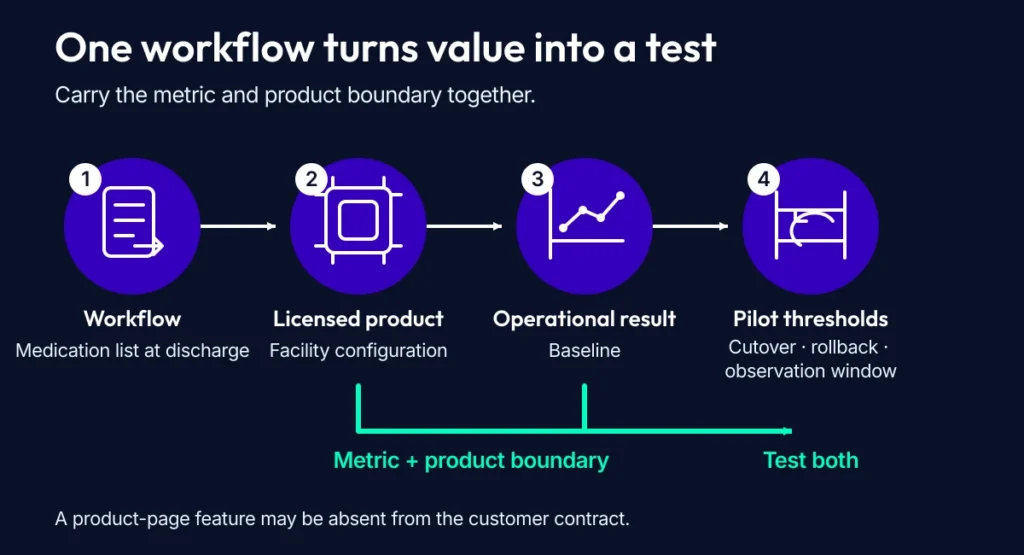
A measurable release carries the workflow, product boundary, baseline, and go-live limits together.
|
Workflow |
PointClickCare surface |
Product boundary |
A metric worth baselining |
|---|---|---|---|
|
Bedside documentation |
Point of Care records ADLs, attendance, vitals, and tasks near the resident |
Mobile Point of Care is scoped to bedside documentation |
Time from care event to signed documentation |
|
MDS and medication work |
The SNF EHR includes MDS and iQIES submission support; eMAR sits in the core SNF package |
PointClickCare’s medication management package adds a pharmacy connection and has its own scope |
Assessment completion and medication-reconciliation exceptions |
|
Wound and after-hours care |
Skin and Wound handles imaging and measurements; Virtual Health connects after-hours telemedicine through Sound Physicians |
Both are named products with their own operating workflows |
Documentation lag, unresolved wound alerts, after-hours response time, and avoidable transfers |
|
Staffing and billing |
Apploi Schedule uses census data for coverage; billing scope changes between SNF and senior-living packages |
These functions can sit outside the base EHR package |
Open shifts, agency hours, clean-claim rate, and days in A/R |
|
Clinical and operating reports |
Advanced Insights has embedded reports that PointClickCare says update daily |
Daily reporting and event-level interface data have different latency |
Report lag and time to close an exception |
The product boundary changes the interface
“PointClickCare” can mean the core SNF EHR, a separate PointClickCare product, or a partner product that reads PointClickCare data. Confirm the licensed product and the exact facility configuration before you write a data map. A feature on a product page can still be absent from the customer’s contract.
A PointClickCare EHR integration can touch more than one of those product boundaries, and each one needs a named contract and data owner.
Take fall management: PointClickCare documents fall incidents, and Chart Advisor can flag possible undocumented risk events for follow-up. Claims about physical fall detection or prevention need separate evidence.
Write the metric before the interface ticket
Pick the operational result and capture its baseline before the PointClickCare integration goes live. Useful measures include:
- duplicate-entry minutes
- transfer-document completeness
- exception volume
- time spent closing one task
If the project adds a machine learning model on top of exported EHR data, keep model performance and clinical workflow performance separate. Our AI in EHR guide covers that split in more detail.
Attach the metric and product boundary to every PointClickCare integration requirement so the pilot can test both.
Related: Medication tracker and pill reminder app development guide
One workflow should carry through the PointClickCare integration process
A PointClickCare EHR integration plan should follow the approvals and data boundaries of the chosen route. Use one sequence in the project plan, architecture record, go-live checklist, and support runbook so the work can’t drift into competing definitions of “done.”
A use case that changes partway through the PointClickCare integration process can reopen the program choice and the approved operations.
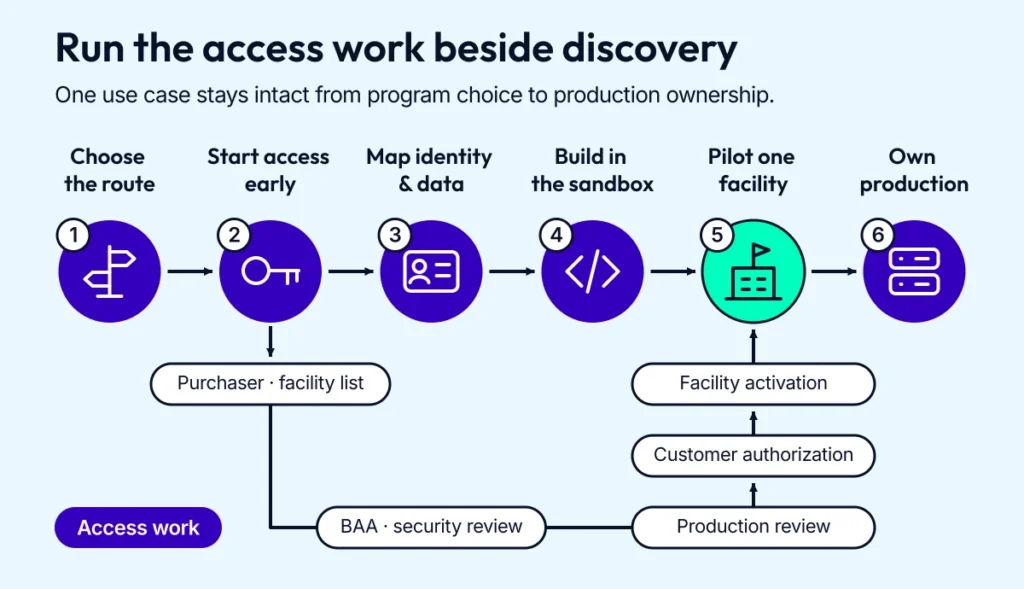
Assign owners and due dates to vendor dependencies early.
Step 1: choose the route around one workflow
Write a single-sentence job for the connection. “Show the current medication list during hospital discharge” names the record set and the care moment, and it doubles as the success test. Keep that sentence in front of everyone who helps you integrate with PointClickCare.
Use that job to choose USCDI Connector, a Marketplace partnership, or a managed feed. Record the choice and the rejected routes in the architecture decision log.
Step 2: start vendor and customer access early
Run the access work beside discovery:
- confirm the PointClickCare program and commercial path
- set up approved developer accounts with 2FA
- name the customer purchaser and list every facility in the first release
- start BAA, security-review, hosting-location, and support-access decisions
The schedule should show these as delivery tasks with owners and due dates. Give every vendor dependency an escalation date too.
Step 3: map identity and data ownership
Build the map before the client code. Start with field ownership and direction, then pin down these details:
- source identifier and target field
- code system and units
- allowed operation and source-of-truth rule
- failure behavior and retry policy
Add example payloads from the approved test environment and keep provenance through each conversion.
Bulk history or an EHR replacement may also need a separate EHR data migration workstream. An API connection and a migration have different rollback plans.
Step 4: build against the approved sandbox
Use the auth method, scopes, certificate details, endpoints, and operations attached to the approved app record. Then test 2 layers:
- contract tests for paging, throttling, token expiry, retries, and schema changes
- workflow tests for resident matching, facility access, source-of-truth rules, and user-visible failures
Treat sandbox success as entry to customer-specific validation. Local configuration and record quality still need production-like test cases.
Step 5: pilot one facility before the network
Complete PointClickCare’s production review, have the customer authorize the app, and activate a facility with representative volume. Reconcile record counts and sample clinical meaning with the people who own the workflow.
Set cutover and rollback thresholds before go-live.
Decision test: can the pilot hold error rates, data completeness, support load, and workflow timing inside those thresholds for the agreed observation window?
Step 6: put an owner on production
Train each role on the part it controls and give support a runbook with named contacts. Production ownership covers:
- authorization renewal and facility changes
- interface health, queue age, failed-record replay, and retry decisions
- clinical workflow questions and source-data correction
- PointClickCare escalation and release regression tests
Set a response target for every PointClickCare integration exception the runbook covers.
Related: How to build an EHR system
PointClickCare integration cost and timing need product labels
PointClickCare publishes several component prices and activation windows. A custom PointClickCare integration still needs a scoped quote because route, facility count, data work, security review, and support model change the job.
Keep the product and stage label beside every published number in the PointClickCare integration budget.
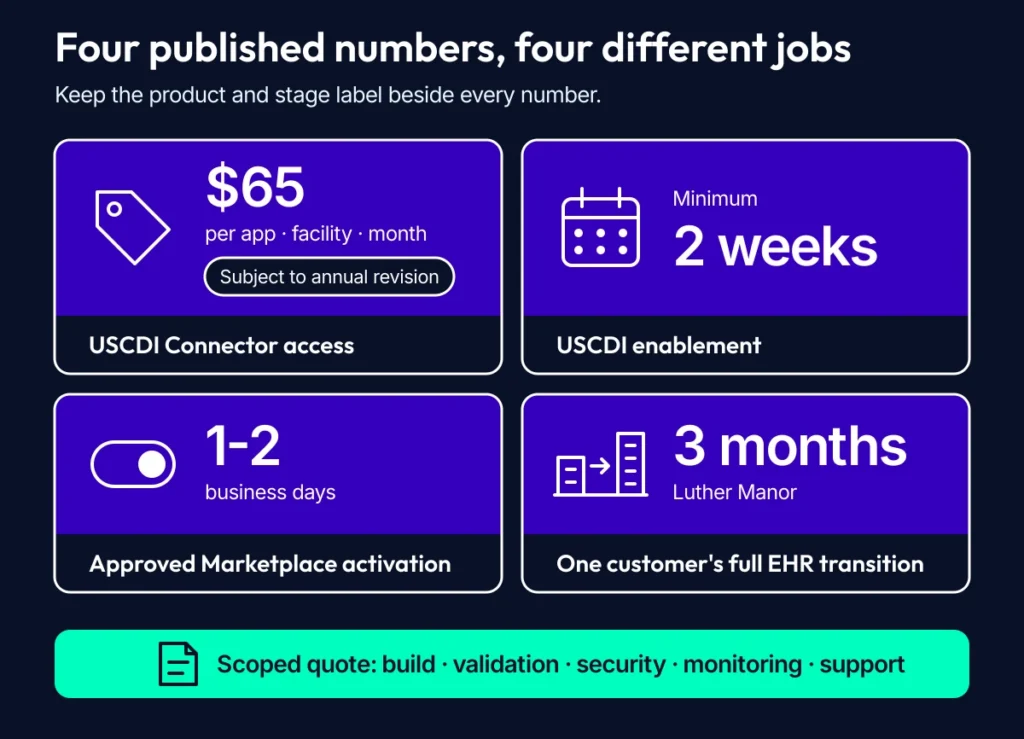
Multiply the USCDI fee by activated apps and facilities, and schedule enablement after app approval and customer authorization.
Published numbers cover different slices of the work
|
Published signal |
What it covers |
How to use it in a plan |
|---|---|---|
|
$65 per app, per facility, per month, subject to annual revision |
The customer pricing model PointClickCare publishes for USCDI Connector access |
Multiply by activated facilities and apps. Budget the app build, validation, security work, monitoring, and support separately |
|
One-time implementation plus ongoing organization- or bed-based charges |
PointClickCare’s Core EHR cost line for its medication management package and e-prescribing |
Use it as a module-level signal in EHR procurement planning. Ask PointClickCare which third-party route and contract apply to the proposed connection |
|
Migration and extract work priced by data volume and required changes |
Historical data movement and conversion |
Separate migration scope from recurring interface scope, with its own acceptance and rollback tests |
|
Minimum 2 weeks |
USCDI Connector enablement after prerequisites, with timing affected by facility count and record complexity |
Place it after app approval and customer authorization in the schedule |
|
1-2 business days |
Activation of an already-approved Marketplace partner connection, counted from the partner’s approval of the customer’s activation request |
Use it for the activation task only. Partner review by PointClickCare, contracting, development, and security work happen earlier |
|
One customer’s full EHR transition in a 2018 PointClickCare story (archived copy), described there as an aggressive schedule |
Treat it as a case example. Build your schedule from route, facilities, migration, testing, training, and local change work |
Build the quote from the actual surface area
A useful PointClickCare integration cost estimate names the assumptions behind it. Price these groups separately:
- partner program, facilities, environments, and vendor fees
- resources or feeds, transformations, write rights, and identity matching
- security review, BAAs, audit evidence, and production-access controls
- migration, cutover, training, monitoring, maintenance, and support
That breakdown lets a buyer remove scope and see exactly how the remaining connection changes.
A baseline makes the first release measurable
Give every KPI a baseline, a target, an owner, and a review cadence. Record those fields before the pilot starts.
|
Measure |
Baseline and target |
Owner |
Review cadence |
|---|---|---|---|
|
Facility activation time |
Request-to-enabled days per facility; set a target after the first approved site |
Rollout lead |
Weekly during rollout |
|
Interface reliability |
Successful calls or messages, failures, retries, and queue age |
Engineering owner |
Live alerting plus weekly review |
|
Data completeness |
Required fields present and valid for the named workflow |
Data steward |
Daily during pilot, then monthly |
|
Reconciliation exceptions |
Open mismatches and median time to resolution |
Clinical operations |
Daily during pilot, then weekly |
|
Workflow time |
Minutes per task before and after release, measured on the same job |
Product owner |
Before pilot and monthly after launch |
|
Support load |
Tickets per facility and median resolution time |
Support lead |
Weekly |
|
Program outcome |
A care or operating outcome with a defined denominator and comparison period |
Clinical sponsor |
At the cadence the measure can support |
Medication errors, staff satisfaction, readmissions, revenue, and ROI need their own measurement design. Report those results as associations unless the program can isolate what the EHR PointClickCare integration changed.
What PointClickCare customer results show
PointClickCare customer stories give you benchmark questions for a defined care program. The measure, population, period, and product need to match your own work before the number belongs in a business case.
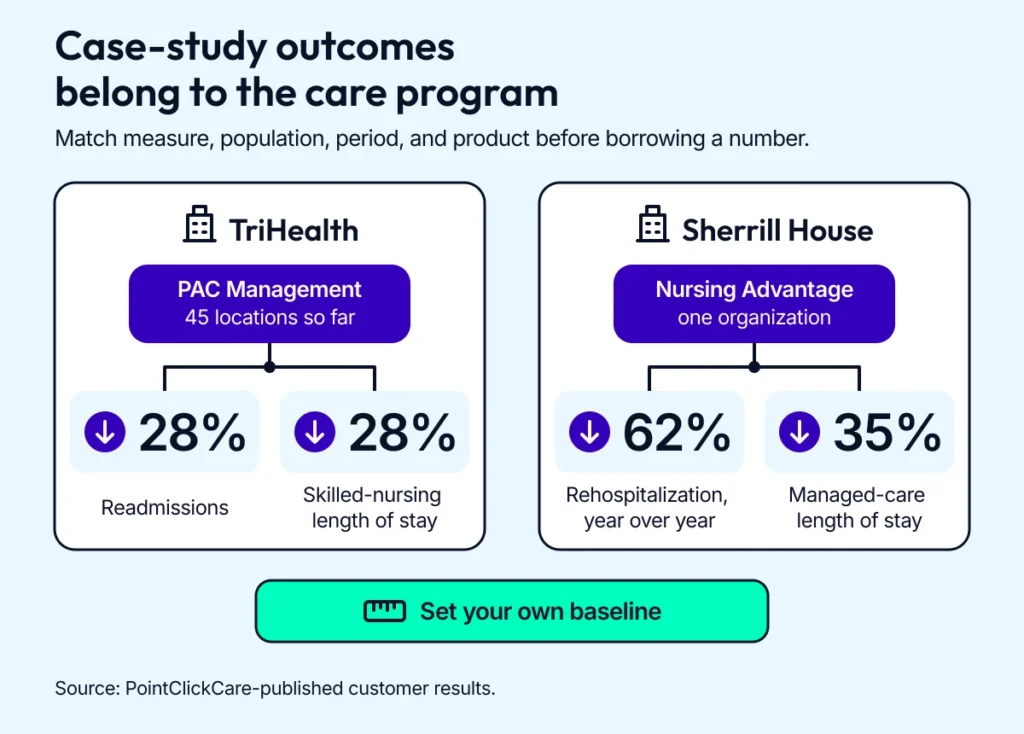
Treat the 4 percentages as prompts for your own measurement plan.
TriHealth measured readmissions and length of stay
PointClickCare’s TriHealth PAC Management case study reports a 28% reduction in readmissions and a 28% shorter skilled-nursing length of stay. TriHealth ran PAC Management IQ at 45 locations alongside dedicated nurse case managers, so both outcomes belong to the operating model described in the case.
Sherrill House tracked rehospitalization and length of stay at one facility
In its Sherrill House story, PointClickCare reports a 62% year-over-year fall in rehospitalization and a 35% shorter managed-care length of stay after Nursing Advantage. These are vendor- and customer-reported results from one organization.
Use both stories to choose measures and denominators for an EHR PointClickCare integration, then set your own baseline. Track PointClickCare integration performance separately from care-program outcomes.
Related: How connected healthcare systems benefit clinics and patients
Adjacent EHR work defines Topflight’s PointClickCare starting point
Topflight’s PointClickCare-specific portfolio currently contains 0 projects. That boundary puts the vendor-specific gaps at the front of the architecture and schedule. The transferable evidence comes from adjacent EHR connections involving vendor review, clinical data mapping, hospital IT, and marketplace packaging.
Reuse the interface-mapping and marketplace-packaging work in PointClickCare integration planning; treat PointClickCare’s program rules as new project inputs.
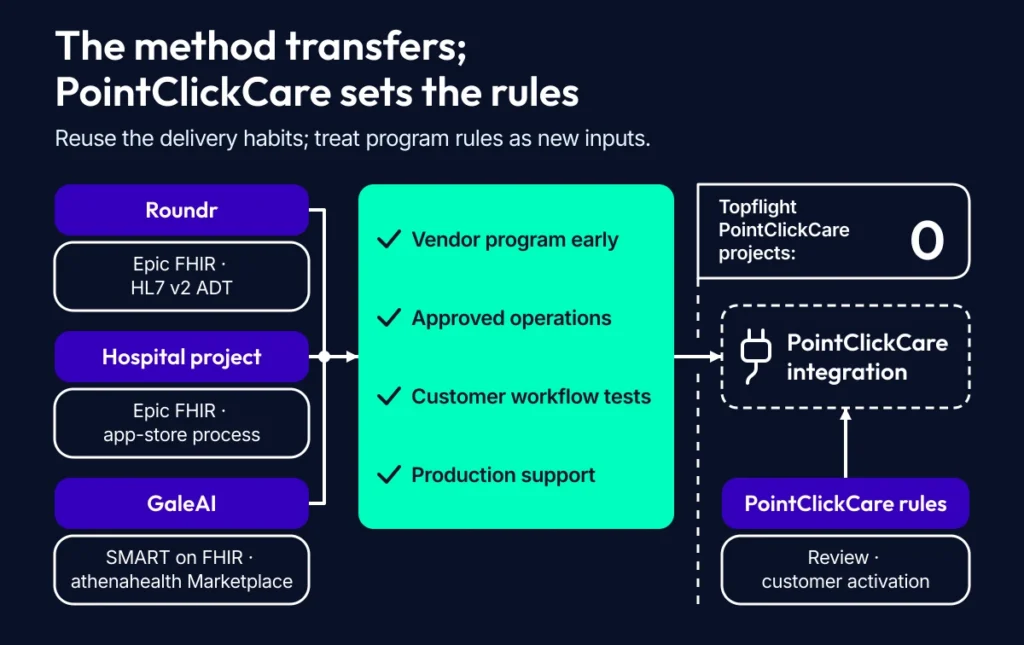
Bring the use case, facilities, source systems, and read or write behavior to scoping so new PointClickCare approvals can be separated from reusable delivery work.
Hospital integrations tie FHIR and HL7 v2 to clinical workflow
For Roundr, our team connected a rounding app to Epic through FHIR plus an HL7 v2 ADT interface built with Mirth. The app had to fit the clinician’s rounding job and the hospital’s interface controls at the same time.
Our EHR integration services page describes another hospital project that used Epic FHIR for patient lookup and went through Epic’s app-store process. Our Epic EHR integration guide covers the vendor-specific approval work behind that route.
GaleAI carried the marketplace packaging work
GaleAI connects with Epic and athenahealth through FHIR and SMART on FHIR. It also ships EHR mini-apps for coding workflows, and our EHR integration services page documents an athenahealth Marketplace module.
That work transfers these habits to a PointClickCare Marketplace integration:
- agree on the vendor program early
- build around approved operations
- test the customer workflow
- package support for production
PointClickCare still sets its own review and customer-activation rules.
Scope the route before the estimate
Bring the use case, candidate facilities, source systems, and required read or write behavior to the first scoping call. We can then separate PointClickCare fees from application work and flag the approvals that belong on the schedule.
Start with our EHR integration services overview when you’re ready to scope a PointClickCare EHR integration.
[Reviewed September 2026 by Scott Rossignol, EHR Integration Architect]
Frequently asked questions
How does PointClickCare integration work in healthcare?
A PointClickCare EHR integration starts with the vendor program that matches the use case: USCDI Connector, an approved Marketplace connection, or a managed feed. PointClickCare reviews production access. The customer then authorizes the app and selects facilities for activation.
How is USCDI Connector different from a PointClickCare Marketplace integration?
USCDI Connector exposes scoped clinical data through FHIR R4 and SMART on FHIR. A PointClickCare Marketplace integration uses the endpoint set or webhooks approved for a specific partner product and may support different operations.
What data can a third-party app access in PointClickCare?
A PointClickCare API integration can access only the resources, operations, residents, and facilities covered by its approved app record and customer authorization. Endpoint behavior may be near-real-time or asynchronous, with paging and throttling set by the service.
How much does PointClickCare integration cost, and how long does it take?
PointClickCare currently lists USCDI Connector customer pricing at $65 per app per facility per month and a minimum 2-week enablement window after prerequisites. An already-approved Marketplace connection activates 1-2 business days after the partner approves the customer’s activation request; development, review, migration, security, and support still need a scoped estimate.