Discovery and rapid prototyping
We define your first release and prototype the patient and clinician journeys before development. Our rapid prototyping service lets you test intake, booking and visits.

Custom telehealth app development services, from prototype to EHR-connected platform.
Topflight Apps, an Irvine, California telemedicine software development company, serves clinics and startups across 14 specialties. Our telehealth app development MVPs: $100K–$150K, 16–32 weeks depending on scope. AlgoRX generated $100K/month within a month of MVP launch; Allheartz’s case reports up to 50% fewer in-person visits and up to 80% less clerical time. Tech leads: Alin Hucea and Francesco Mantovani.
For the AlgoRX launch result and build details, see how to create a telehealth app.
| Question | Topflight Apps at a glance |
|---|---|
| Where is the company based? | Irvine, California. You can find our office address and contact details on the company page. |
| Which healthcare apps have you built? | Geneium’s DNA-based skincare app, AlgoRX’s prescription platform, and the iFaint research dashboard built with Medable for Stanford Medicine. |
| How do we get started? | In discovery, we work through your clinical workflows and estimate the build. A prototype lets you test the patient and provider experience before development. |
| How is the team selected? | During discovery, we’ll discuss who’ll handle development and security for your app, based on its features and integrations. |
Our telemedicine app development services cover discovery, custom builds, integrations and support after launch. We plan the work around your clinical workflows and the systems your team already uses.
We define your first release and prototype the patient and clinician journeys before development. Our rapid prototyping service lets you test intake, booking and visits.
Our custom telehealth software development covers native iOS and Android apps or React Native. We plan device access for video or audio-only visits where permitted, using the same process as our healthcare app development work.
Our telemedicine software development services include patient portals and clinician workstations. We plan synchronous and asynchronous telehealth around live visits, messages and store-and-forward photo reviews. We test browser camera and microphone access, EHR write-back and failed syncs.
EHR integration connects appointments, notes and supported readings to your clinical systems. We check API access, map the records and test the connection in the vendor sandbox.
We build remote patient monitoring (RPM) into telehealth apps for reviewing device readings between visits. Your clinicians set alert thresholds and response responsibilities; we build the queue and escalation route.
We plan moves from a white-label telehealth platform to a custom app when clinical routing or EHR access needs change. Your workflows and data access shape the build, record migration and service switch.
After launch, we can maintain your app and handle updates as patient and clinician needs change. Our delivery process includes staging and regression testing before production releases.
We build virtual care around when your clinicians are available and how your patients reach them. That includes consent for video visits and a clear way to get help between appointments.

A virtual visit can save a trip to the clinic. We build around the states you serve and include referrals for patients who need an in-person exam.

Patients can send messages and receive reminders between visits. If you provide after-hours care, we can route urgent requests to the on-call clinician.

Patients can save travel time when a visit can happen remotely, and clinics can use appointment capacity differently. Whether that lowers operating costs depends on your staffing and reimbursement.

Clinicians can review patient photos and follow-ups between scheduled visits. We plan response times and urgent requests around the staff you have available.

Check-ins let your care team follow symptoms between appointments. Your clinicians decide which changes need review and where the app sends those concerns.

When a video call drops, patients need a way to reconnect or continue the visit another permitted way. We test calls on weak connections and plan that fallback.
We start with the work that’s slowing your team down or holding up launch, then decide what the app needs to do.
Before writing custom code, we check whether existing video and scheduling tools will do the job. We also put vendor contracts and EHR access on the launch plan, since either can hold up release.
Copying notes between video, EHR and lab tools takes staff time. We decide where each record lives, then use FHIR or HL7 where supported to send updates to clinicians.
HIPAA and state practice rules shape different parts of the app. We trace PHI through your vendors and document access controls and audit requirements for your compliance team.
We test your expected peak visit volume before release, including what happens when services fail. That helps us plan video capacity and cloud costs, and choose what to monitor as use grows.
A patient should be able to complete intake and join the first visit without staff walking them through every screen. We test that path with users and use visit and reminder data to identify where they drop out.
We work with your billing team on claims and patient payments, including the visit documentation your payers need.
Request a proposal for an app
We build around the care your clinicians deliver. Your specialty’s assessment protocols and escalation rules guide the features we choose.
For teledermatology app development, we can build secure photo uploads and dermatologist review queues. Geneium gives users DNA-based skincare reports they can export to dermatologists.
Patients can send dental photos for triage or join a video consultation. We build the review queue and patient follow-up around your dentists’ care process, including when to book an in-person exam.
Telestroke teams need video exams and assessment results during the visit. We can add NIHSS capture and connected-device readings, with an escalation route for cases that can’t be assessed remotely.
Prenatal and postpartum care can combine video check-ins with home blood-pressure readings. Your clinical team decides which readings to collect and when a patient needs an in-person visit.
Pharmacists can review counseling requests alongside patients’ medication information. We plan prescription routing and refills with your pharmacy partners, including who reviews interaction alerts.
Surgeons can use secure video for consultations and post-operative wound reviews. For operating-room proctoring, we plan around acceptable latency and the participating clinicians’ protocols.
Give your cardiologists ECG and blood-pressure trends, with device details alongside each reading. We work with your clinical team to set alert thresholds and decide who responds.
Retinal screening starts with fundus-camera images that specialists can review. We build image-quality checks and referral tracking around your diabetic retinopathy protocol, so clinicians can identify patients who need an in-person exam.
Nurses can review triage and post-discharge requests in one queue. When a patient needs a prescribing clinician or an in-person visit, your nurses can pass the request to the right person.
Therapists can check exercises over video and follow progress logs between visits. If you want motion data, we’ll check what the device can capture and how your therapists will use it.
Remote specialists need to view whole-slide images and send their findings back to your lab. We plan for the large files and control access, while keeping a history of each review.
Bring lab results and supported device readings together for your CKD and home-dialysis patients. We plan video rounds and escalation around the clinicians who’ll monitor them.
Scheduling and intake should fit how your clinicians evaluate patients and manage medications. We can include PHQ-9 questionnaires in the intake. For XZEVN, a mental health app, we built emotion journaling and reading recommendations.
Patients request a visit, and the app finds a clinician who’s available and authorized to treat them in their location. We build matching around your payment rules.
Our healthcare app development cost guide gives 2 budget ranges for telemedicine builds. The right budget depends on the features and integrations you need.
| Build type | Planning budget | Planning timeline | What it covers | What to plan for |
|---|---|---|---|---|
| Production MVP | $100K–$150K | 16–32 weeks, depending on scope and integrations. | Video visits, scheduling, clinical notes and basic analytics. | Deep EHR write-back is left for later. We confirm vendors and first clinical workflows during discovery. |
| Expanded telemedicine build | $300K–$400K+ | EHR read/write and multi-clinic care, plus e-prescribing, eligibility or RPM as needed. | Vendor access can change the work. Budget separately for running costs and ongoing support. |
EHR access and provider routing can change both the budget and the schedule. We check those dependencies during discovery, then give you an estimate for each phase. The roughly $200K case studies below show what clients spent on their particular projects.
The states you serve and the clinicians on your team shape what the app needs to do. We work through practice rules and billing before choosing features.
| Topic | Product decision | Current policy |
|---|---|---|
| Licensing and interstate care | Record patient location at each visit, then route the request to a clinician who’s authorized to practice there. Keep the clinician’s location on record too. | IMLC expedites separate physician licenses.
NLC uses multistate licenses for qualifying RNs/LPNs, excluding APRNs. PSYPACT requires E.Passport and APIT for psychologists practicing from their declared home state. PT Compact privileges follow the patient’s state rules. Each compact applies within participating jurisdictions; state exceptions vary. |
| Controlled prescribing | Record the visit format and previous evaluations with each prescription. Update prescribing rules as requirements change. | DEA’s temporary Ryan Haight pathway lets qualifying DEA-registered practitioners prescribe Schedule II–V medications without a prior in-person evaluation through December 31, 2026. The default is an audio/video visit; audio-only prescribing is limited to certain opioid-use-disorder medications, and state requirements still apply. |
| Reimbursement and coding | Check which services each payer covers. Bill using the patient’s location and claim type. | Medicare permits covered telehealth from any US location, including home, through December 31, 2027. Home audio-only flexibility shares that deadline.
POS 02 means outside the patient’s home; POS 10 means at home. Modifier 95 requirements depend on payer and claim type, including hospital outpatient therapy. Coverage parity concerns covered benefits and terms; payment parity concerns provider rates. |
| Privacy and vendor agreements | Check vendor agreements and who can access PHI at each step. | OCR’s telehealth transition ended August 9, 2023. Covered providers and plans need HIPAA-compliant vendor services and applicable BAAs. |
Decide who’ll own the practice and make clinical decisions before launching a provider network. California’s corporate-practice-of-medicine restrictions, for example, reserve certain clinical decisions for licensed physicians.
Regulatory sources checked October 21, 2026.
The tools we choose depend on what your app needs to do and where it sends patient data. We check the BAA and eligible services for any vendor handling PHI.
Video and real-time communication
We can build calls and visit messaging with WebRTC or providers such as Agora, Twilio Video and Vonage. We check the applicable BAA and how PHI moves, then test call recovery on your supported devices.
Cloud and compliance infrastructure
We use HIPAA-eligible services on AWS, Google Cloud or Microsoft Azure, with the applicable BAA. We set up encryption and access logging for your app.
Mobile and web
We use Swift or Kotlin for native apps, or React Native when it makes sense to share mobile code. React supports browser apps; HealthKit and Health Connect connect to data on the device, while cloud data uses separate vendor APIs.
Interoperability and AI
FHIR and HL7 move clinical data between systems; SMART on FHIR handles authorization and app launch. For AI features like note drafting and chat assistance, we set limits on data access and decide with your clinicians what needs review.






Request a proposal for an app
We’ll choose native iOS and Android or React Native based on how your patients use the app. Device access and push notifications are part of that decision.
Patients can check into a virtual waiting room before joining a secure video visit with a caregiver or interpreter. We plan how they’ll rejoin if the connection drops.
Secure chat lets patients send follow-up photos and receive care instructions. We work with your care team on message access and retention, including which messages belong in the visit record.
Patients book against provider calendars and can reschedule within your clinic’s rules. Reminders use the channels and consent choices you approve.
We connect e-prescribing to your pharmacy workflow, including refill requests and medication lists. Permissions follow the clinician’s prescribing authority and the requirements for each medication.
Your remote patient monitoring app can bring supported device readings into the chart between visits. We work with your clinicians to set alert thresholds and decide who receives each alert.
We handle push notifications and app store submission, along with the payment and device connections your app needs. For Android readings, we use Health Connect or a supported cloud API, depending on where the data is stored and what access is available.

As a telehealth app development company, we connect your app to the clinical and payment systems you use. During discovery, we work out which data needs to move and how to recover from system outages.

For Epic EHR integration, Oracle Health or athenahealth, we start with the APIs your organization can access. Then we map how notes, vitals, appointments and prescriptions move between systems, using native APIs or middleware where needed.
FHIR resources and HL7 v2 interfaces handle different parts of EHR interoperability. SMART on FHIR handles authorization and app launch. We check which USCDI and US Core versions your EHR supports, along with its SMART requirements. A newer USCDI release doesn’t change the vendor’s API on its own.
Stripe or Braintree can handle patient payments and subscriptions. We work through refunds and PCI responsibilities with your processor, and plan a separate claims workflow for insurance billing.
Your clinicians can review Apple Watch and supported medical-device readings in the dashboard. We use HealthKit or Health Connect for device-held data and check Google Health API migration and access for Fitbit cloud connections. Each device’s measurements and vendor permissions determine which readings we can retrieve.
During discovery, we’ll explain who’ll lead your app’s architecture and development, and who’ll review security before release.
Our technical team includes Alin Hucea and Francesco Mantovani, both Tech Leads, and Khurram Islah, our Head of Security. Meet more of the people behind our healthcare apps in our company profiles.
Our healthcare apps development services include work on Medable‘s clinical-trial platform and its dashboard for Stanford Medicine‘s iFaint study. As a telemedicine software development company, we’ve also built products for Athcorp, ARA Genomics and Cleveland Clinic.
We build on HIPAA-eligible AWS, Google Cloud or Microsoft Azure services, with the BAAs your project requires. We configure access controls and audit logs for your patient data. For video tools such as the Agora SDK, we test weak connections and plan how patients rejoin interrupted visits.

FHIR and HL7 connections can send visit notes and other clinical data back to your EHR. We check what your EHR can read or write, then plan provider calendars and on-call routing with your team.
We choose AI and machine learning features around the clinical task and the data you can use. Our custom mobile app development process includes testing with real patients and clinicians, so their feedback shapes what we build.
Bring your idea or prototype. We’ll work out what goes into the first release, then adjust the roadmap as we learn from your users.
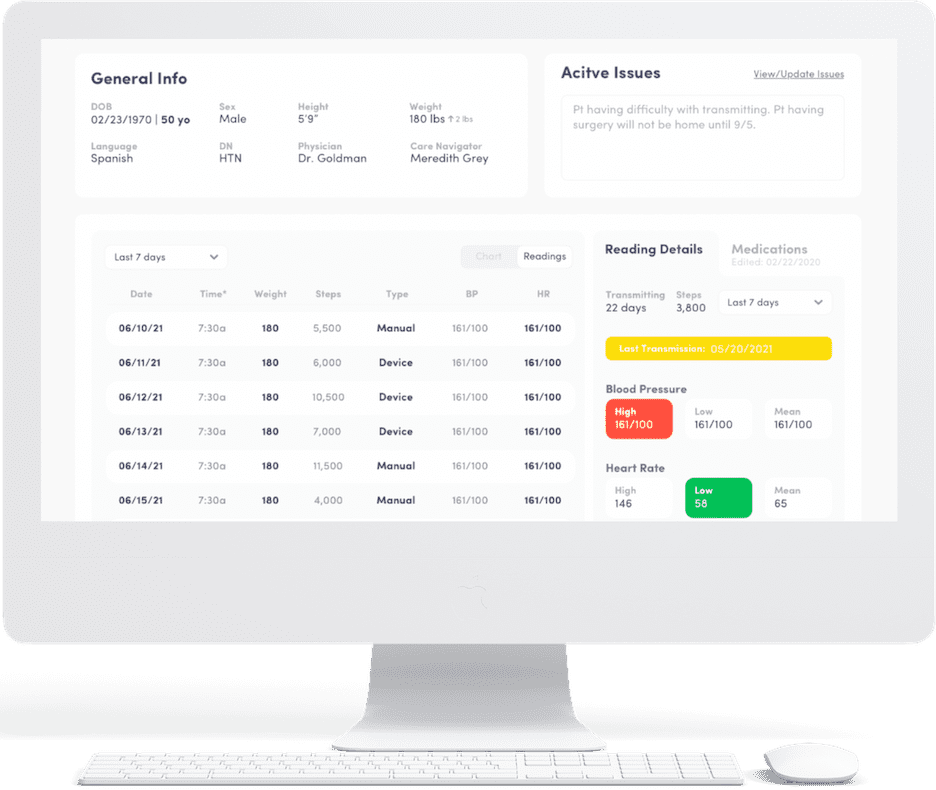
Patients should be able to book, complete intake and join the right clinician’s visit without losing track of what’s next. If a connection drops, they need a way back in.
On the provider side, scheduling needs to match clinician availability. Intake answers and visit history should arrive before the consultation starts.
Choose video conferencing that fits your consent and recording rules. Test the visit flow on weak networks, including what happens when patients reconnect.
Keep encounter notes and the follow-up plan in the visit record, and make sure they reach the systems your care team uses.

We start telemedicine app development by looking at who’ll use the app and what each visit needs to capture. We check EHR and vendor limits before choosing the stack and estimating your first release.
Deliverables: Requirements document (SRS), development estimate
A clickable prototype lets you test patient and clinician journeys before telemedicine software development starts. We use the feedback to fix the flow while changes are still cheap.
Deliverables: Clickable application prototypes


Then we turn the tested flows into screen designs and navigation. We include the states you’ll need for incomplete forms and dropped connections.
Deliverables: design assets, high-fidelity prototypes.
We build in 2-week sprints, with demos and a weekly progress check-in. Your product manager keeps you up to date on the roadmap and estimates as we build features and connect vendors.
Deliverables: application code, beta versions


QA runs through each sprint, including regression tests as features change. Your team can try the release on staging and give feedback on the patient and clinician flows.
Deliverables: source code, a ready-for-deployment application
We release your app to the app stores or your production web environment. You receive the source code, and you can keep working with us on updates and support as usage grows.

Request a proposal for an app
AlgoRX is a prescription storefront for non-controlled medications. Patients complete an eligibility questionnaire at checkout, and providers review pre-filled SOAP notes before approving orders. We built multi-pharmacy routing and a patient portal with HIPAA safeguards; the MVP shipped on time, and AlgoRX retained us for ongoing work.
E-commerce + e-prescribing · NextJS, Supabase, DoseSpot
We helped a San Francisco telehealth company take its product through discovery and UX/UI, then built a web app that works on mobile screens. Patients track symptoms, medications and diet, while clinicians review the trends in a React Native dashboard. The client rated us 5.0 overall in its Clutch review.
~$200K · 12-month engagement (April 2022–April 2023)
We built iOS and Android apps with AWS and RevenueCat for a telehealth founder in Burton, Michigan. In their Clutch review, the client rated us 4.5 overall and 5.0 for willingness to refer.
~$200K · November 2021–August 2023 engagement
“We hired them for an MVP, but they delivered what feels like an entire platform.”
Ray Arias, Owner, ARA Genomics. Read the Geneium case.
Choose a telehealth software development company that can show shipped products and explain its EHR work. Compare each telehealth development company with your first-release requirements:
| What to check | Evidence to request |
|---|---|
| Shipped telemedicine products | A working product or case study, with the team’s role in its patient and clinician workflows made clear. |
| Video vendors and BAAs | The proposed vendor, its BAA (business associate agreement) and a map of visit data, including recordings. |
| EHR integrations shipped | Connected EHRs, permitted read/write operations and failed-update handling. If billing needs it, request evidence of eligibility verification. |
| State licensing and prescribing workflows | Patient-location, interstate licensure and provider credentialing checks reviewed by your clinical and legal teams. If controlled prescribing is needed, request the vendor’s EPCS (electronic prescribing of controlled substances) plan. |
| Prototype before development | Patient and clinician journeys to test before estimating the build, including permissions for a multi-tenant platform if needed. |
| Support after launch | Incident ownership, release testing, support terms and access to your source code. |
Topflight Apps was a 2022 Inc. 5000 honoree. You can also read our client reviews on Clutch and view our GoodFirms profile.



Updated October 21, 2026.
Budget $100K–$150K for a telemedicine MVP with video visits, scheduling, notes and basic analytics, leaving deep EHR write-back for later. Our healthcare app development cost guide estimates $300K–$400K+ for expanded builds with EHR read/write and features such as e-prescribing and RPM. Your estimate will depend on the features and integrations you need at launch.
We estimate your first release during discovery, after checking the integrations it needs. Development runs in 2-week sprints; EHR access and vendor approvals can affect the schedule. Plan 16–32 weeks, depending on scope and integrations. The San Francisco project above was a 12-month engagement.
Yes, if your app handles PHI for a covered entity or business associate. We map how that data moves and choose vendors that can meet your HIPAA requirements, including applicable BAAs.
A ready-made product makes sense when its workflows and vendor agreements fit your practice. Choose custom development when you need different clinical routing or deeper EHR connections, and work through those requirements before picking a platform.
Choose the platform around how patients attend visits and the devices they use. A responsive web app works for booking and clinician dashboards; mobile apps suit recurring sensor readings and patient check-ins.
Our telemedicine app development services connect to the APIs your EHR supports and your organization can access. We map appointments and visit notes, then test the connection in the vendor sandbox. Where the EHR supports SMART on FHIR, we can use it for authorization.
Our telemedicine app development company reviews who can access PHI and builds in encryption, role-based permissions and audit logs. We configure cloud services under the applicable BAAs and document how your team should operate these safeguards.

