

Updated on October 20th, 2026
Reviewed by Francesco Mantovani, Head of Engineering
Telemedicine app development runs in five steps: choose the platform, design the patient and clinician flows, connect a HIPAA-eligible video API, test on real devices, and deploy. Budget 16 to 32 weeks and $100K–$150K for a production MVP; expanded builds with EHR write-back land at $300K–$400K+.
The United States is running out of clinical capacity in a measurable way. The Association of American Medical Colleges projects a shortage of 13,500 to 86,000 physicians by 2036, and HRSA’s shortage-area data counts roughly 137 million people in designated Mental Health HPSAs.
How to develop a telemedicine app end to end: the features that ship in v1, the video and messaging APIs that carry the visits, the compliance work behind them, and the cost and timeline that follow from all three. Telemedicine application development is mostly a sequence of scope decisions, and the order you make them in decides what the build costs.
Should I build a custom telemedicine app or buy a white label?
Buy white label if you need a pilot inside 60 days or expect under about 10,000 visits a year. Build custom once you need specialty workflows, EHR write-back, or a patient experience your competitors can’t copy. The white label fee is worth paying until the workflow you need doesn’t exist off the shelf.
Top Takeaways:
- The global telehealth market reached $186 billion in 2025 and Fortune Business Insights projects $219 billion in 2026, which keeps demand for a telemedicine app development company steady.
- A production MVP budgets $100K–$150K across 16 to 32 weeks. Expanded builds with EHR write-back run $300K–$400K+.
- Behavioral health accounted for 67% of telehealth encounters in 2024, so the workflow has to work for a therapist as well as a physician.
- Ready-made video APIs such as Twilio, Agora and VSee carry the visit, and the HIPAA-compliant video SDK you pick matters less than the BAA behind it.
Table of Contents:
- 1. What are the latest telemedicine trends in 2026?
- 2. Practical applications of telemedicine in healthcare
- 3. What challenges do telehealth apps face?
- 4. Telemedicine app security
- 5. Telemedicine app features: what ships in v1
- 6. How to build a telemedicine app step by step
- 7. White label telemedicine solutions
- 8. How much does it cost to build a telehealth app?
- 9. Monetization strategies of a telehealth app
- 10. How Topflight fast-tracks telehealth app success
- 11. Our experience developing telehealth apps
- 12. Time to make a telemedicine app
What are the latest telemedicine trends in 2026?
The COVID-19 pandemic transformed healthcare services faster than a decade of shiny consumer tech ever did. But the “everyone is doing video visits” phase is over. In 2026, the real story is that virtual patient care has normalized into a set of repeatable workflows, especially where access is tight and no one wants to burn clinician time on low-value logistics.
That shift matters if you’re planning telemedicine application development or deciding whether to create a telehealth app now: the winners are “workflow-first.” Think scheduling that actually reduces friction, async intake that removes back-and-forth, and routing that keeps the right patients out of the wrong queues. (Your clinicians need fewer meetings. Telehealth just happens to be the lever.)
Market overview
From a market lens, the telemedicine market is still expanding globally: Fortune Business Insights estimates $186B (2025) and projects $219B in 2026.
In the healthcare sector, utilization looks like a steady baseline. FAIR Health’s claims-based tracking shows that in early 2025, about 14.9% of patients had a telehealth claim in January, dipping slightly to 14.5% in February (commercially insured). And behavioral health remains the heavyweight: the American Hospital Association reported behavioral health represented 67% of telehealth encounters in 2024 (commercially insured).
Practically, that demand shows up in three dominant modalities you’ll need your telemedicine software to support: live phone consults, live video consults, and health app or website consults (asynchronous messaging/intake plus lightweight monitoring). Audio-only visits are not going away either: Medicare policy explicitly allows two-way audio-only in defined scenarios (and permanently for behavioral/mental telehealth).
Net: if you’re trying to build a telemedicine system in 2026, treat modality as a product decision with its own tradeoffs and plan telehealth platform development around workflows.
More on health and fitness app development in our dedicated blog.
Telehealth market statistics
US, 2024–2025 baseline → planning for 2026
| Metric | What the numbers say | Context (why it matters) | Source / As-of |
|---|---|---|---|
| Price reality (commercial claims) | $24 median allowed (telehealth) vs $24 (in-person office) | Telehealth wins on workflow and access. Visit price is a separate question. | FAIR Health (US), Dec 2024 |
| Baseline utilization | 5.04% of all medical claim lines were telehealth | An operating baseline you can design around. | FAIR Health (US), Dec 2024 |
| Behavioral health dominates | 66.9% of telehealth volume was behavioral health; 58.5% of telehealth patients had a mental health condition | If your product doesn’t support BH workflows well, you’re building “telehealth” with one hand tied behind your back. | Trilliant Health (2024); FAIR Health (Jan 2025) |
| No-show impact | Lower odds of non-attendance: OR 0.61 | Show-rates are operational ROI. Less wasted clinician time, fewer reschedules, tighter panels. | Systematic review/meta-analysis (45 cohort studies) |
| Satisfaction (virtual care) | J.D. Power score: 730 (direct-to-consumer) vs 708 (payer-provided), out of 1,000 | Consumers reward convenience + clarity. “Workflow-first” is also “experience-first.” | J.D. Power, 2024 |
| Modality mix (reality check) | Physician video use: 49.6% (2024) vs 59.1% (2020); 40.9% provide audio-only weekly | Build each modality as its own workflow. | AMA, 2024 |
| RPM economics (Medicare) | $100–$180+/month per patient reimbursement potential, depending on how far up the CPT stack the practice bills (large practices, 10+ physicians) | RPM ROI depends on ops + scale. The workflow is the business; the app is the easy part. | CMS 2026 fee schedule |
| Hospital-at-Home (when ops are tight) | Reported savings 19%–30% vs inpatient (Johns Hopkins); ROI mixed across operators | Shows where telehealth is heading: protocolized, hybrid care models. | Johns Hopkins (reported); broader evidence mixed |
Telemedicine is Inclusive
Underserved communities, seniors with chronic diseases, and other vulnerable groups of population along with tech-savvy younger people looking for a healthy lifestyle, a vast population is going to adopt and rely on telemedicine. But here’s something to ponder: what about the ‘pain points’ these diverse groups might encounter while using a telemedicine platform? Those pain points belong in the first release scope.
Done well, that translates directly into higher patient satisfaction, because the delivery of care adapts to real-life constraints (work schedules, mobility limits, distance from a specialist). Done poorly, the same app becomes a barrier precisely when patients need it most, during a late-night flare-up, a post-op check-in, or a near-emergency that should have triggered an escalation 48 hours earlier.
That means the companies working on telemedicine solutions would need to sort out another layer of complexity with telemedicine software development. How do you create a telemedicine app that is equally well understood and navigated by different target audiences?
Check out our on demand webinar on: Buy or Build Telehealth?
Vertical growth
Telehealth is rapidly expanding beyond e-consulting with a physician. As patients are getting accustomed to the new technology, there appears the need to cover the whole spectrum of healthcare services. That brings to life new, niche telemedicine products, such as teledermatology apps, telenursing apps, telepsychiatry, teledentistry, and other types of health related virtual care apps.

The modality you lead with decides which video stack, compliance work and price range you inherit.
Better insurance coverage
Insurance companies and federal health care programs are stepping up to cover care you deliver through telehealth apps. For instance, Medicare already covers some types of telemedicine services and remote patient monitoring. You can build a telemedicine platform that connects to insurance services. That is how mobile health changes access to care and the way insurance gets managed at the same time.
Read Also: Insurance App Development Guide
Remote patient monitoring
Remote patient monitoring (RPM), as a distinct subset of telehealth, is winning wider adoption as providers seek to push back patient readmission rates. RPM apps, paired with wearable devices like smartwatches, blood-pressure cuffs, and continuous glucose monitors, have proven their effectiveness in helping doctors watch patients’ recovery or illness progression while they stay at home, feeding continuous medical data straight into the patient record without forcing a clinic visit. For healthcare organizations running chronic-care programs, remote monitoring has moved from “pilot program” to billable backbone of a sustainable virtual-care practice.
Related: How to build a remote patient monitoring app
AI
Artificial intelligence is a change agent. Applied to patient healthcare data, the technology can assist medical personnel by making predictions about patients’ well-being. That results in timely and accurate treatment plans.
Related: Deep Learning in Healthcare: Use Cases and Case Studies, AI App Development Guide
Benefits of telemedicine apps
Why would you build a telemedicine app for Android and iOS? Training a new doctor can take up to 18 years. And one of the benefits of telemedicine is that it eliminates this waiting period for patients in communities with limited access to healthcare professionals by linking them to other physicians from all over the country, on-demand.
Other benefits matter more for patients and care providers, and they matter most on mobile.
Patient benefits
-
-
- On-demand access to healthcare specialists
- Authorized permission to message the doctor
- No need to travel to a clinic
- Lower cost of service
- Ease of use (accessible on any device)
-
Provider benefits
-
-
- Freedom to collaborate with remote colleagues on patient cases
- Access to home-care and discharged patients
- Ability to treat more patients simultaneously
- Integration with EHR and other clinical systems
- Fewer cancellations and missed appointments
-
Investor benefits
Telehealth has become investable for reasons that don’t show up in a feature list:
- Recurring revenue by default, subscriptions, per-visit billing, and RPM reimbursement codes ($100–$180+ per patient per month on Medicare) produce predictable MRR/ARR once a clinic is onboarded.
- Capital-light scaling: adding patients doesn’t require new exam rooms, so gross margin typically expands as volume grows.
- Regulatory tailwinds that stuck: permanent Medicare coverage for audio-only behavioral health, state parity laws, and a growing RPM code set mean the reimbursement floor keeps rising.
- A $219B (2026) market that’s already segmented: behavioral health, RPM, chronic care, and specialty verticals each support focused plays, so you don’t have to “beat Teladoc” to build a defensible business.
- Unit economics you can actually measure: lower no-show odds (OR 0.61), shorter lead times than in-person visits, and better clinician utilization feed straight into LTV and payback math.
Telehealth solutions need to be built by a specialized custom mobile apps development firm that understands healthcare regulations.
Top 3 successful telehealth apps
Before you build a telehealth application, three incumbents are worth studying.
Teladoc
Market Cap: ~$1B (as of April 2026, down from a peak of roughly $45B in early 2021 during the pandemic-era telehealth surge)
Founded in 2002 and publicly traded since 2015, Teladoc is one of the most established publicly traded telemedicine companies in the US. The company provides patients and doctors with easy-to-use mobile apps for iOS and Android and offers its telehealth platform as a white-label solution.
The Teladoc notable app features include:
-
-
- Scheduling a meeting
- Mobile payments
- Video and audio calls
- Integration with Healthkit and Google Fit
- Medical history
-
Doctor On Demand
Funds raised: $160m, now part of Included Health following a 2021 merger with Grand Rounds Health.
Doctor on Demand is a telemedicine app that connects patients with a variety of healthcare professionals. Similar to Teladoc, the company offers its customers apps on both mobile platforms. Patients can schedule a video appointment from their phones and tablets.
Notable features:
-
-
- Upfront pricing
- Medication management
- Push notifications
- Video calls
- Healthkit and Google Fit
-
Related: How to Develop a Doctor’s Appointment App, On-Demand Doctor App Development
MDLIVE
Funds raised: ~$174m as an independent company, before being acquired by Cigna’s Evernorth for an estimated $1B in April 2021. MDLIVE is a telehealth service company that was founded in 2009 in Sunrise, Florida, and now operates as part of Cigna’s Evernorth health services portfolio. MDLIVE partnered with Walgreens to add pharmacy access to its platform.
Important features:
- ePrescribe integration
- Video calls
- Health records
- Instant messaging
- Mobile payments
Related Article: The Best Telemedicine Apps
There are many other types of healthcare apps with telemedicine features that focus on different care aspects, from therapy to psychology, but they each deserve their own guide.
Practical applications of telemedicine in healthcare
Most of what telemedicine changes happens off the video call. Telehealth now handles scheduling and follow-up, so a clinic’s day runs on software instead of phone tag.
These applications ensure that a therapist or a GP can deliver care that fits the patient in front of them.
How telemedicine is transforming clinics and hospitals
Telemedicine is changing how clinics and hospitals run by improving workflows and patient outcomes:
- Virtual Consultations – Enables remote diagnosis and follow-ups, reducing congestion in hospitals and clinics.
- Partner pharmacies – Patients can receive digital prescriptions and have medications delivered without visiting pharmacies in person.
- Remote Therapy Sessions – Therapists can conduct video consultations for mental health support and rehabilitation.
- Chronic Disease Management – Continuous monitoring and digital check-ins improve treatment adherence for long-term conditions.
Doctor-patient relationships
The adoption of telemedicine strengthens communication between doctors and patients, making healthcare more responsive and engaging.
Through doctor profiles, your patients can check a provider’s experience and specialties before they book. Reminders for upcoming sessions, medication adherence, and follow-ups improve patient compliance. Telemedicine platforms also track consultation duration, so a clinic can see when visits start running long.
Treatment workflows that telemedicine simplifies
Hospitals and private practices benefit from automated processes that sharpen personalized care and treatment efficiency:
- Diagnostics Integration – Remote patient monitoring tools collect vital signs and share real-time data with healthcare providers.
- AI-Powered Symptom Analysis – AI chatbots handle preliminary assessments before connecting patients with specialists.
- Centralized Health Records – Ensures direct access to patient history, improving decision-making in hospitals and outpatient facilities.
Used well, telemedicine gives a patient the consultation without the commute.
What challenges do telehealth apps face?
Telehealth is operational now. But the moment you try to move from a pilot to a real telehealth app (or a full telemedicine platform), the hard parts show up fast: compliance, call quality, patient UX, and integrations that don’t politely stay inside your sprint plan.
The good news: most of these problems are predictable. We build telemedicine apps against this list, and the order matters: compliance and call quality first, because retrofitting either one costs more than designing for it.
| Challenge | What it looks like in real life | Solution (what you build) | Build notes (so it doesn’t blow up later) |
|---|---|---|---|
| HIPAA compliance complexity | “We’re using cloud… are we compliant yet?” | Encrypt PHI in transit + at rest, role-based access, audit logs, retention controls, BAAs with vendors | Decide where PHI lives early; audit logging is hard to bolt on later |
| Video quality complaints | Frozen video, choppy audio, “I can’t hear you” | Adaptive bitrate + auto quality fallback; pre-call network test; audio-only fallback | Instrument call quality metrics; add TURN relay fallback for restrictive networks |
| High no-show rates | Clinicians waiting; patient forgets / can’t join | Reminders (SMS/email/push), calendar invites, one-click join, easy reschedule | Add “join from reminder” deep link + quick device permissions check |
| EHR integration difficulties | “We need Epic/Cerner/Athena integration” (but requirements are fuzzy) | Start with FHIR where possible; isolate integration layer; queue + retries; mapping/normalization | Scope the first integration to 1–2 workflows (e.g., demographics + encounters) |
| Patient identity matching | Duplicate records, wrong charts, safety risk | Strong identity model + verification steps; matching rules; manual review workflow | Patient matching is a product problem with its own workflow |
| Security & account takeover | Weak passwords, reused links, session hijacks | MFA options, short-lived tokens, session timeouts, device trust, rate limiting | Don’t rely on “magic links” alone for sensitive actions |
| Consent & privacy expectations | Patients ask “Who can see this? Can I revoke access?” | Consent capture + revocation flow; granular sharing; clear privacy UI | Make consent auditable (who consented, when, to what) |
| Clinical documentation burden | Clinicians hate “double charting” | Smart templates, structured notes, auto-attach visit metadata, exportable summaries | Design for “finish the note fast” over “more fields” |
| Accessibility & UX friction | Older patients can’t navigate; low vision/hearing | Large-tap UI, captions support, keyboard navigation, screen-reader friendly flows | Test with real devices and real patients in the room |
| Language barriers | Miscommunication, safety risks | Multilingual UI; interpreter workflow; real-time captions where feasible | Don’t use generic translation for medical instructions without review |
| Scheduling & time zones | Wrong appointment times; missed visits | Time zone–safe scheduling, buffer rules, clinic hours logic, cancellation policy | Prevent double-booking with server-side rules (not only front-end checks) |
| Scalability & reliability | Peak-hour slowdowns, dropped calls | Observability (logs/metrics/traces), autoscaling strategy, graceful degradation | Build SLOs early and define what “video works” means as a number. |
HIPAA compliance is the floor. If your telehealth app touches PHI, imaging like MRIs and CT scans, doctor’s notes, lab results, compliance runs end-to-end, vendors included. In practice, teams often start with HIPAA-ready hosting on AWS or GAE, then add audit logging and access controls early (because retrofitting “who accessed what, when” later is a special kind of pain).
A consumer video tool can’t stand in for a telehealth build. If the vendor won’t sign a BAA, the tool can’t carry PHI, whatever its feature list promises.
Related: Building a HIPAA-Compliant App Made Easy
Telemedicine app security
Security in a telemedicine app is mostly plumbing: where the data sits and who can reach it. Healthcare applications handle vast amounts of protected health information, which means regulatory compliance, starting with HIPAA and extending to state-level privacy rules, is non-negotiable. One misconfigured storage bucket exposes PHI, and the breach-notification clock starts the day you find out. Those requirements only count once they show up in permissions and logs.
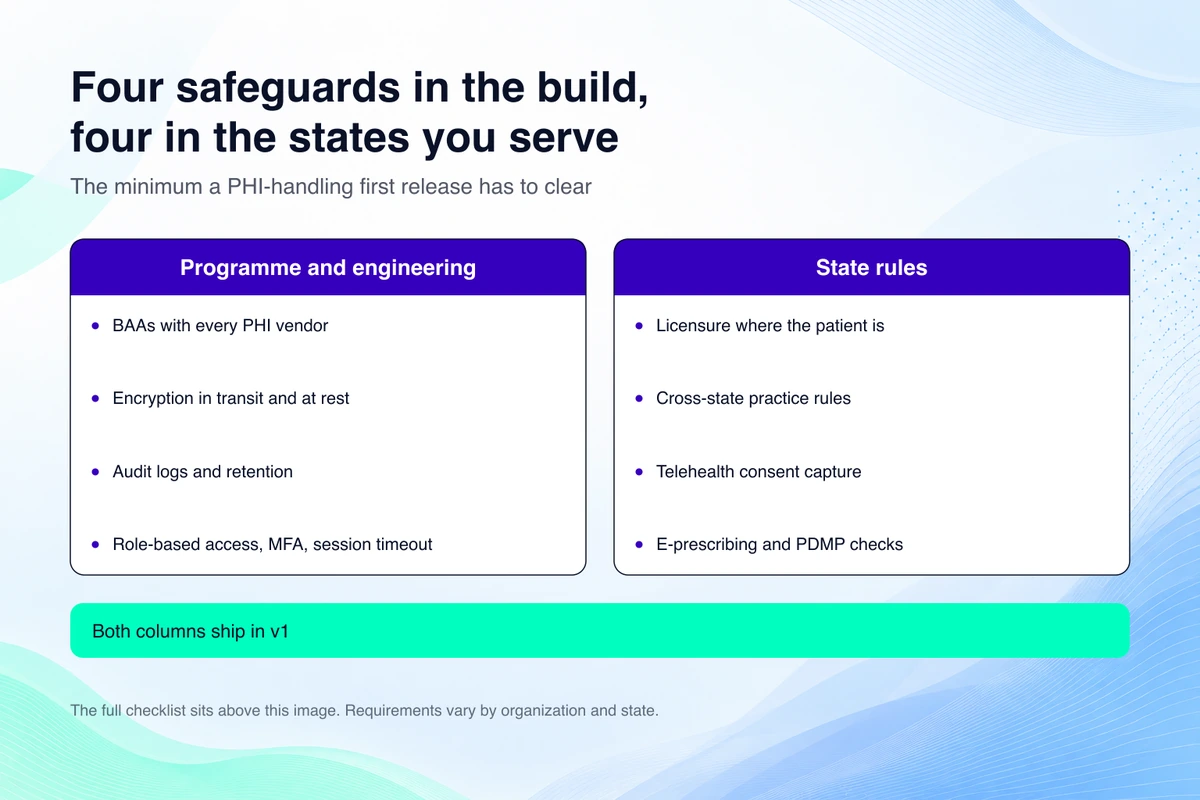
Half of compliance is engineering and half is paperwork across the states you treat, which is why both land in the first release.
Ensuring security in telemedicine apps
To safeguard telemedicine applications, you want these controls in place before launch:
- Data Encryption: End-to-end data encryption ensures that sensitive medical information remains protected, both at rest and in transit.
- HIPAA Compliance: The app must adhere to HIPAA regulations, securing protected health information (PHI) and limiting unauthorized access.
- Secure Authentication: Multi-factor authentication (MFA) and biometric verification tighten access control.
- Regular Security Audits: Routine assessments help identify vulnerabilities and prevent potential data breaches.
- Role-Based Access Control: Restricting access ensures that only authorized personnel can view or modify patient data.
Best practices for telemedicine app security
A secure telemedicine build follows a short set of practices we won’t ship without:
- Security Testing: Perform penetration testing and vulnerability scans to detect weaknesses before deployment.
- Data Storage Protections: Store PHI in secure, encrypted databases with access logging and monitoring.
- Risk Mitigation Strategies: Implement real-time threat detection that pages someone when access patterns turn strange.
- Compliance with Future Regulations: Stay updated on evolving data protection laws to ensure long-term security.
Telehealth compliance checklist
(practical implementation checklist; requirements vary by org + state)
HIPAA Requirements (program + technical controls):
☐ BAAs in place with all vendors that may touch PHI (cloud, video, messaging, analytics, support tools)
☐ Encryption in transit (TLS) and at rest for PHI
☐ Audit logs for PHI access (who/what/when/where) + log retention defined
☐ Role-based access control (RBAC) + least privilege (minimum necessary access)
☐ Strong authentication (MFA for clinicians/admins; secure session management)
☐ Automatic session timeout / re-auth for inactive sessions (set a policy; 15 minutes is a common starting point)
☐ Data retention + deletion policy (define by legal/clinical needs; don’t hardcode one number unless you’ve standardized it)
☐ Backups + disaster recovery plan (RPO/RTO targets documented)
☐ Incident response plan + breach notification workflow tested
☐ Regular risk assessment + vulnerability management (pen tests/scans, remediation SLAs)
State-Specific Requirements (operational + clinical rules):
☐ Interstate licensure: confirm the provider is licensed where the patient is at the time of the visit
☐ Cross-state practice rules (telehealth modality allowed, supervision rules if applicable)
☐ Consent requirements (telehealth consent language, when/how it must be captured)
☐ Prescribing rules (controlled substances, tele-prescribing constraints, PDMP checks where applicable)
☐ Minor consent / guardian rules (varies heavily by state and service type)
☐ If recording is used: recording consent + storage/retention policy + access controls
Treat telemedicine app security as a launch gate. Get the controls in before release and the audit turns into a checklist review.
Telemedicine app features: what ships in v1
Your telemedicine app needs a specific feature set to deliver complete telehealth services, and it’s shorter than most teams expect. Depending on whether you start with a minimum viable product (MVP) or continue building a full-fledged telemedicine app, there will be different features in your app.
Once you decide to develop a telehealth application, the feature question is really two questions: what belongs to whom, and what ships in v1 vs. later. Role decides who owns a feature. Priority decides when it ships, and every item carries a rough cost so you can build a telemedicine application on a realistic budget.

The admin console is the panel teams forget, and the first one your ops team opens.
Also, you may be interested in how to build a video chat app.
Telehealth app MVP feature set
Thinking about a telehealth MVP by role helps avoid two common mistakes: over-building a patient app with clinician features that go unused, and under-building the admin console until your ops team is in revolt. Every feature below is MVP-eligible, but you won’t need all of them in v1. We’ll prioritize in the next section.
Patient features
- Onboarding, consent, and ID verification: new-user registration should capture telehealth-specific consent. That is a compliance requirement, and a generic ToS does not satisfy it.
- Secure video + audio visits: HIPAA-eligible SDK (Twilio, Agora, VSee) with audio-only fallback for low-bandwidth situations and a virtual waiting room, so the clinician decides when the visit opens. (HIPAA compliant video conferencing and messaging.)
- Secure 1:1 chat with the provider: pre-, during-, and post-visit messaging. (More on messaging app architecture.)
- Appointment booking + reminders: self-serve slot selection, time-zone safe, with SMS/email/push reminders. A proper patient scheduling tool also lets admin staff cancel, reschedule, and sync with calendar apps.
- Patient profile & medical history: lets the patient see their own chart, upload documents, and review visit notes.
- Mobile payments / cash-pay checkout: for non-insurance flows; subscription or per-visit.
- Apple Health / Google Fit connectors: optional but low-lift; useful longitudinal signal.
Related: Build a Video Calling Application
Provider features
- Provider dashboard: today’s queue, wait times, upcoming appointments at a glance.
- Video, audio, group calls, and secure chat: same rails as the patient side, different UI (more controls, lower friction to switch modalities).
- Clinical documentation: structured notes with templates; auto-attach visit metadata (duration, modality, participants) so the note practically writes its own header.
- Provider profile: specialties, credentials, availability, photo. The patient-facing trust layer.
- Electronic prescriptions: if in scope for MVP; otherwise explicitly deferred. (More on e-prescription integration.)
- Chart + history view: patient context surfaced at the point of care, within one tap. If you are building an app for neurology, this view also needs to handle labs and imaging alongside notes.
Also Read: Guide to building a messaging application
Admin and staff features
- User and role management: add/remove clinicians, assign roles (provider, nurse/medical assistant, admin, billing), rotate access. (Nurse-side workflows deserve their own UI if you run a large care team, see our virtual nurse app guide.)
- Scheduling administration: cancel/reschedule on behalf of patients, clinic-hour rules, calendar sync.
- Audit log review: who accessed what PHI, when, and from where. Required for HIPAA; quietly essential for incident response.
- Billing administration: refunds, adjustments, reporting by provider or service line.
- Content and settings management: forms, consent language, reminder templates, basic branding.
- Integration config: where EHR, e-prescribing, and RPM connections get wired once you’re ready for them.
Read more our telehealth EHR integration guide
MVP planning: must-have vs. nice-to-have features
Not every feature above ships in v1. The split below maps to the cost tiers you’ll see later in this post: must-haves typically land inside a basic MVP (~$80k–$120k), nice-to-haves push you into Standard (~$120k–$180k) or Advanced (~$180k–$300k). Ranges are directional; they shift with integration depth and compliance scope.
Must-have features
- Secure video calling: +$15k–$25k. SDK integration (Twilio/Agora/VSee), BAA, variable bitrate, audio-only fallback, pre-call network check.
- Secure 1:1 chat / messaging: +$8k–$15k. Encrypted, HIPAA-eligible (CometChat, Stream, or SDK-level via Twilio/Agora).
- Appointment scheduling: +$10k–$20k. Slot booking, reminders, calendar sync, time-zone safety. (Skip self-serve if a front desk handles it, see the Scoping Guide below.)
- Patient + provider onboarding and profiles: +$10k–$18k. Consent capture, ID verification, baseline profile fields.
- HIPAA-ready foundations: +$15k–$25k. Encryption in transit and at rest, RBAC, MFA, audit logging, session timeout. It’s mandatory for any PHI-handling telemedicine application. Retrofitting is painful and audit-visible.
- Admin console (baseline): +$10k–$15k. User management, basic reporting, settings. You’ll use this on day one.
- Clinical notes (structured, basic): +$5k–$10k. Templates for common visit types; exportable summaries.
Directional must-have total: ~$100k–$128k, the lower half of the MVP budget.
Related: How to Create a Mental Health App
Nice-to-have features
These turn “a working telehealth app” into a platform, but they often defer cleanly to v1.5 or v2, once real clinical workflows have surfaced.
- EHR / FHIR integration (first 1–2 workflows): +$25k–$60k. Start with demographics + encounters, and use SMART on FHIR for authorization where the EHR exposes it. Interoperability scope grows fast once clinicians get comfortable, and HL7 v2 still appears for legacy systems.
- E-prescribing (Surescripts via Dosespot/NewCrop): +$20k–$40k. Needed the moment you treat acute conditions; can be deferred for pure behavioral health.
- Payment gateway beyond basic checkout: +$8k–$25k. Stripe/Square for cash-pay is cheap; insurance billing is its own project.
- Group video / multi-party consults: +$8k–$15k. Worth it if care teams actually collaborate in-visit; otherwise theoretical.
- Remote patient monitoring device ingestion: +$25k–$50k+. The code payoff is real ($100–$180+ per patient per month on Medicare), but so is the complexity (device SDKs, HL7 and FHIR mapping, alerting thresholds).
Related: Pharmacy App Development Guide
- Apple Health / Google Fit integration: +$6k–$12k. Low-lift longitudinal signal; most useful for chronic care and fitness-adjacent verticals.
- AI-powered symptom checker / triage chatbot: +$20k–$60k. Saves clinician minutes on intake; scrutinize clinical-safety scope before claiming “diagnoses.” To learn more, we recommend reading our articles about chatbots in medicine and how to build your own chatbot.
- Multi-language support: +$10k–$25k. Real requirement if your population demands it; don’t use generic machine translation for medical instructions without clinician review.
- Advanced analytics dashboards: +$15k–$30k. Provider productivity, utilization, outcome signals, often investor-facing more than clinician-facing.
- VR for telepsychiatry / specialty modalities: +$40k–$80k+. Treat it as a differentiator. (See our mental health app guide.)
- IoT peripheral integration (intraoral cameras, dermatoscopes, sensors), +$20k–$50k+ per device class. Specialty-driven; budget per device family, because one integration rarely covers the next device. (IoT app development guide.)
Sequencing rule of thumb: ship the must-haves, then add one nice-to-have per quarter based on clinician feedback.
Related: IoT App Development: The Ultimate Guide
MVP scoping guide: integrate EHR, scheduling and payments now, or later?
(Rule of thumb: sequencing that keeps scope from blowing up.)
1) Are you launching into an existing clinic workflow where the EHR is the system of record from day one?
→ Yes: Plan EHR integration early (otherwise you risk “double charting” backlash)
→ No / greenfield or DTC: Defer EHR; go to #2
2) Will clinicians and staff need self-serve scheduling inside the app, with front desk tools out of the loop?
→ Yes: Ship scheduling in MVP (missed visits and time-zone bugs become your new hobby)
→ No: Start with manual scheduling / simple appointment requests, integrate later
3) Do you need to collect payment inside the product at launch (cash-pay per visit or subscription)?
→ Yes: Ship payments in MVP (keep it simple; keep the “pay → join call” flow short)
→ No / billed elsewhere (insurance, invoicing, existing billing ops): Defer payments; integrate later
4) If you answered “Yes” to EHR integration: is your requirement “we need Epic/Cerner/Athena integration” but the workflows are still fuzzy?
→ Yes: Treat “integrate the EHR” as a scope trap. Integrate 1–2 workflows first (rule of thumb: demographics + encounters) and expand after pilots
→ No (clear workflows + mapping): Proceed with a phased EHR integration plan
What this usually means in practice
- Visits-first MVP (most common): video + chat + basic scheduling; payments only if you’re cash-pay; EHR later
- Clinic-embedded MVP: scheduling + identity model + narrow EHR integration early; video/chat still core
Build notes (so it doesn’t blow up later)
- Start with FHIR where possible, isolate the integration layer, and design for queue + retries + mapping/normalization
- Treat patient matching as a product workflow with its own UI and review step
Related: Virtual Nurse App Development Guide
How to build a telemedicine app step by step
How to build a telehealth app and how to build a telemedicine platform come down to the same five moves. Telemedicine app development on this scale is mostly sequencing, and each step carries the timing we use on a first release. Together they add up to the 16-to-32-week range above.

Steps four and five start while three is still running, which is why the plan compresses to 16 weeks.
-
-
- Step 1: Choose a platform: where patients open the app decides everything that follows.
- Step 2: Design the perfect telehealth app – The experience decides whether patients finish the visit.
- Step 3: Choose APIs you can use to integrate into your app: four APIs cover most builds.
- Step 4: Test your telemedicine app – a dropped call is a lost patient.
- Step 5: Deploy and maintain your app: launch is the start of the maintenance work.
-
Work through them in order. The decisions in step 1 constrain everything that follows.
Week-by-week timeline to develop a telehealth application
Weeks 1-2: discovery and planning
- Define HIPAA requirements
- Choose video API (Twilio vs Agora)
- Map user journeys for patients/doctors
- Security architecture planning
Weeks 3-4: design phase
- Patient app wireframes (15-20 screens)
- Doctor dashboard design (10-15 screens)
- Appointment flow prototyping
- HIPAA-compliant UI elements
Weeks 5-8: backend development
- Set up HIPAA-compliant cloud (AWS/Google)
- Implement authentication (2FA required)
- Video call infrastructure
- Database encryption setup
Weeks 9-12: frontend development
- React Native app development
- Doctor web portal
- Real-time chat implementation
- Payment gateway integration
Weeks 13-16: integration, QA and release
- EHR, pharmacy and device integrations connected and load-tested
- Regression and accessibility pass on real devices
- App Store review and Google Play review submission, with the screenshots and privacy declarations both stores require
- Monitoring, alerting and an on-call runbook for launch week
That is the 16-week fast end of the range. EHR access, BAA negotiation and vendor approvals push a build toward 32.
Step 1: choose a platform
Typical timing: Weeks 1–2 (Discovery & Planning)
Before you commission your designers and start coding, you need to decide which platforms to custom develop your app for whether you’re building a fitness app, or a meditation app, etc. iOS and Android for mobile, web and native for desktop. Your target geography and app functions will direct your choices.
If you remember our recent article about making health apps for the iPhone, we discussed why an iOS-only approach works best for the USA, and an Android-first approach for the rest of the world.
We’re staying on the US market, where the platform question comes first.
Mobile: iOS or Android?
Have you considered support for iOS/Android?
In the United States, iOS accounts for 53.6% of mobile browsing and Android for 46.4% (Statcounter, September 2026).
That split is close enough to even that an iOS-only launch writes off almost half the market. The two stores also review on different timelines, so plan both submissions together.
At 46%, Android users are too many to be ignored, so you need to factor this into your long-term planning. In fact, when you think about telemedicine mobile app development, it’s clear that catering to both sides of the fence can really pay off in the long run.
React Native is the sensible default here for healthcare application development, given the likely need to cater to both iOS and Android devices.
Related: Swift or React Native: Which to Choose?
Choosing the right platform for your mobile app
Desktop: native or web?
You will need a web app for patients who cannot access an iOS or Android device, as well as for physicians to manage their workflows and patient files.
The cost of building a web app and a native app is almost the same. In fact, a web app can be converted into a native desktop app that works on Mac, Windows, and Linux using tools like Electron. Slack is an example of software built with Electron. Another consideration on your list is mobile web – should the application be accessible through mobile browsers?
Choosing between SaaS and custom build
A SaaS solution does not give you the liberty to personalize the front-end experience beyond a logo and name change. Other than that, the app is identical to all their other customers’ apps.
If you want to control exactly how your app looks and functions, or you need to build an app for telemedicine that fits a specialty workflow SaaS vendors simply don’t support, you’ll need a custom telehealth app. In this case, say, telenursing app development services from healthcare app development experts may come handy.
A custom mobile app is developed using a technology stack of open source and paid APIs. This gives you granular control over your entire app and ties it into your existing infrastructure. By using TURN servers and protocols such as WebRTC to handle your videotelephony, we can create a telehealth platform that works just the way you want it.
If you’re debating white-label vs custom, jump to the decision guide in the White Label section.
Is SaaS cheaper than a custom build?
SaaS solutions typically support the business model based on a monthly subscription fee. They can be deployed relatively quickly because there is little to no programming involved. The monthly payment is usually adjusted according to user volumes. This is an overhead you have to maintain indefinitely.
SaaS may initially appear to be the cheaper option, but it can become the more expensive choice once you outgrow the capabilities of your SaaS product. When you reach that stage, you’ll be back searching for a custom solution to meet your growing business needs.
Also, you have no control as to when or what changes your SaaS provider makes to your app. They can remove features and update policies on a whim. And because they have to support many clients, this may lead to some uncomfortable compromises for everyone.
A custom build costs more up front in development and maintenance and pays that back over the years you run it. As part of this strategy you’ll have to create a mobile telehealth app and a web dashboard for providers.
Compare the three-year cost against product-market fit before you sign. A custom-built app offers absolute authority over every aspect of your app, including branding.
Step 2: design the perfect telehealth app
Typical timing: Weeks 3–4 (Design)
User experience design
The user experience design is the most critical aspect of the entire health app design phase.
Many entrepreneurs come up with great app ideas and build apps that work very well from a technical standpoint but end up failing because the user experience is out of touch with the target audience.
Understanding the people you’re trying to help matters more than the technology you pick.
The UX design stage is where this can be prevented.
You will be designing two sides of your app – a provider backend and a front-facing patient side.
Be sure to simplify the onboarding process as much as possible by limiting the number of screens to a maximum of three. Too much information and you could make it difficult for your users. The copy must be written in 3rd grade English. Everyone can understand that level of English. Write to be understood, so users do exactly as you say without second-guessing.
Time spent on every call will be charged, so strive to make the app as easy to use as possible. The provider and patient need to concentrate on the consultation. Every extra tap competes with that.
After your UX wireframes are completed, you need to set up a focus group and conduct user testing. Get user feedback, revise the UI design according to their recommendations. Repeat the process until you are satisfied.
Once this stage is complete, you’re ready for the next one – User Interface Design.
User interface design
The User Interface Design stage adds skin to the UX wireframes. Colors, buttons, fonts, and all other visual aspects of the app come to life in this stage of mobile application development.
Different colors and button sizes need to be tested. User behavior is affected by colors and the position of components on a screen. The UI then becomes a clickable prototype, built the way our rapid prototyping process works, and that prototype goes in front of users too.
Like the UX stage, revisions must be made as needed until you are satisfied.
This is a brief glimpse of the whole design process. For a more in-depth look, please read our 7-Step Ultimate Guide to Mobile App Design. Read it before you wireframe anything.
Step 3: choose APIs you can use to integrate into your app
Typical timing: Weeks 1–2 for selection, Weeks 5–12 for integration
Building a telehealth app in the absence of market-ready APIs can easily take 1 to 2 years. But with the components now readily available in the market, a telehealth app can be built in 3-6 months.
This doesn’t diminish the fact that it is still a very difficult and time-consuming task to make third-party APIs work as desired (make sure you work with a tech-savvy project manager). Most of these builds come down to four APIs:
VSee SDK
VSee SDK is a rich telemedicine API that integrates end-to-end encrypted video calls into your mobile app for iOS and Android, as well as native apps on Mac and PC.
It’s HIPAA compliant and has its own server-client, so you don’t need to provision a server to set it up. It cuts the technical workload, so you can spend that time on user experience and interface design.
However, the drawback is that it’s not open source, and there’s a significant cost barrier to get the customizable codebase. Access to the codebase can cost as much as $20,000. Failure to get that would mean you have to settle for their SaaS option, which provides no personalization besides a name and logo.
WebRTC
WebRTC is a free and open-source platform that enables real-time communication in web and native apps. It has simple APIs tuned to transmit audio, video, and data. Supported browsers are Firefox, Opera, and Chrome on desktop and Android.
Native support is also available for Android and iOS. macOS and Windows are not supported.
The setup of this API is more involved than the others, but it’s very customizable.
OpenTok and Vonage
OpenTok is a cloud-based WebRTC platform. While WebRTC is an open-source, the software that powers OpenTok is not. It offers all the customization potential you’d have on your own WebRTC deployment.
Owned and developed by Vonage, OpenTok also allows you to integrate video, voice, text messaging, and screen sharing into your app on the web, iOS, Android, and Windows. It doesn’t support macOS.
OpenTok supports HIPAA-compliant app development. The development company building your app is responsible for configuring the app per HIPAA requirements and choosing the appropriate tech stack.
Twilio
The Twilio Programmable Video API runs in every major browser without a plugin, and on iOS and Android. Twilio prices group rooms at about $0.004 per participant-minute.
It hooks into platform APIs such as iOS CallKit and ARKit, which widens what you can put inside the call. Twilio also sells SMS, voice and email APIs beside it, so one vendor can carry the visit and the reminders around it.
Choosing video APIs
Video APIs are one of those “looks cheap on a pricing page, gets expensive in production” choices, mostly because vendors bill differently (participant-minutes vs archive minutes vs flat per-provider plans) and because telehealth adds compliance overhead (BAAs, security configuration, and data retention). The quick table below is meant to help you sanity-check tradeoffs fast, then the two mini scenarios underneath show how the same product can land in a very different monthly range depending on call volume, average participants, and whether you record sessions.
Video API Comparison for Telehealth
| API | Cost (USD) | HIPAA Compliant | Setup Time | Best For |
|---|---|---|---|---|
| Twilio Video | $0.004 per participant-minute (Group Rooms). Recording: $0.004 per participant-minute. | HIPAA-eligible with BAA + proper config | ~1–2 weeks | Mature SDKs, global scale, predictable usage-based billing |
| Agora (RTE) | $3.99 / 1000 participant-minutes for HD video (≈ $0.00399 per participant-minute). First 10,000 min/month free. Recording: $0.99/1000 min. | Yes with BAA + secure config | ~1 week | Cost-effective MVPs + scaling when you want low list prices and a free tier |
| Vonage Video API (OpenTok) | $0.00410 per participant-minute. Recording (composed): ~$0.026 (SD) to $0.0363 (HD) per archive-minute (higher for FHD). | Yes, but typically Enterprise + BAA | ~2–3 weeks | Feature-heavy builds (broadcast, SIP, add-ons) where you accept “enterprise pricing gravity” |
| VSee (SDK / platform) | $0–$49 per provider/month (subscription; not per-minute). Enterprise: contact sales. | Yes, BAA included | Days–1 week | Fast telehealth rollout (platform approach) when you want “telehealth features included,” not raw video primitives |
| Custom WebRTC (self-managed) | Infrastructure cost (servers + bandwidth + ops). AWS egress ~$0.09/GB; cost scales with video bitrate + TURN usage. | Self-managed (you own BAA/security/compliance posture) | ~4–6+ weeks (often months) | Full control + bespoke requirements (but you pay in engineering time and ops complexity) |
Two quick sanity-check scenarios (monthly video + recording, list prices)
(Not quotes. Real pricing varies with discounts, regions, and recording modes.)
| Vendor | MVP clinic (500×20min, 2 ppl, no recording) | Scaling (5,000×25min, 3 ppl avg, 20% recorded) | What drives the bill |
|---|---|---|---|
| Twilio | ~$80 | ~$1,800 | Participant-minutes; recording scales linearly |
| Agora | ~$40 (first 10k free) | ~$1,530 | Lower list price + separate (cheap) recording rate |
| Vonage | ~$82 | ~$3,487–$4,260 | Recording/composed archive can dominate total cost |
| VSee | $0–$29 | $49/provider/mo (× providers) | Predictable budgeting; not usage-based |
| Custom WebRTC | ~$20–$40 (infra only) | ~$500–$1,000+ (infra only) | Bandwidth + TURN + ops/support become the “real bill” |
How that lands on the monthly bill:
- If you don’t record, Twilio/Agora/Vonage are in the same ballpark; your choice is mostly SDK maturity + ops preference.
- If you do record, Vonage can get expensive fast (recording mode matters more than the base call rate).
- “Custom” looks cheap on infra but you pay in engineering + ongoing ops (monitoring, scaling, compliance, troubleshooting).
(All costs USD, as-of late 2025. Actual bills may vary with volume discounts, regional rates, and contract terms.)
Decision guide: which video stack should you pick for telehealth?
(Rule of thumb based on vendor list pricing + your scenarios; real pricing can change with BAAs, regions, volume discounts, and recording mode.)
1) Are you trying to ship a compliant telehealth experience fast (days → 1 week) with “telehealth features included,” not raw video primitives?
→ Yes: VSee (platform/subscription approach; BAA included; per-provider pricing model)
→ No / you want raw video API building blocks: go to #2
2) Do you need full control / bespoke requirements that don’t fit vendor constraints (custom media routing, unusual topology, specialized infra/security posture), and you’re okay owning ops + compliance?
→ Yes: Custom WebRTC (self-managed) (expect longer setup + ongoing ops)
→ No: go to #3
3) Will recording be a meaningful part of the product (e.g., >10–20% of visits recorded, or you need composed recordings)?
→ Yes: go to #4
→ No (mostly live visits): go to #5
4) Recording-heavy path
- Need recording, but want to keep list-price costs down for an MVP or early scale?
→ Agora (lower list price per participant-minute; separate lower recording rate)
- Need a feature-heavy “enterprise add-ons” ecosystem and accept enterprise pricing gravity?
→ Vonage (but watch recording and composed archive costs, which can dominate the total)
- Need predictable, mature SDKs and broad ecosystem; recording costs are acceptable and you value reliability + docs
→ Twilio
5) Mostly live visits (little/no recording)
Is your top priority “mature SDKs + global scale + predictable usage-based billing”?
→ Yes: Twilio
→ No / you’re cost-sensitive and want a lower list price + free tier for early usage: Agora
→ No / you specifically want feature-heavy enterprise add-ons (broadcast/SIP/etc.) and can tolerate longer setup: Vonage
What’s your pricing model preference?
- If you hate per-minute variability and want “per provider” budgeting → VSee
- If your usage is uncertain and you want usage-based alignment → Twilio / Agora / Vonage
- If you want infra-based costs and accept engineering/ops complexity → Custom WebRTC
Acuity: scheduling
Acuity has been designed to support the healthcare industry’s needs and, as such, is HIPAA-compliant. You’ll need a Powerhouse plan for you to enter into a BAA with Acuity Scheduling.
How do you or your development team select the right APIs?
This depends on your choice of platform and what functions you need. The best combination is React Native as your platform, Twilio for video and chat. The chat must be encrypted with Virgil Security’s end-to-end encryption SDK.
Step 4: test your telemedicine app
Typical timing: weeks 5–16, with a final regression pass in week 16
Testing is the milestone that matters in telehealth app development. An app that holds up under load launches clean; one that doesn’t costs you the first week. You should have your app developers execute peer code reviews. At the same time, the QA team carries out unit tests on various devices.
Even though a properly setup QA process implies frequent testing after each sprint, do plan for a final quality assurance round that includes regression testing and covers everything you’ve already tested during previous sprints. We recommend performing stress testing early on during telemedicine platform development and certainly before the launch to see if the app can hold an inflow of new users.
Related: Complete Guide to QA Testing
Step 5: deploy and maintain your app
Typical timing: week 16 onward, for release and monitoring
Finally, once the app has been developed, it’s time to move it to a live environment and into the app stores where customers can download it. Now you’re fully ready for starting a telemedicine app.
IOS and Android receive updates every year. It’s essential to update the app accordingly to make sure it continues providing the best user experience and vigilant data security.
That’s the gist of the development process for creating a telemedicine application.
Also Read: How to build a medical startup and succeed in healthcare
White label telemedicine solutions
Teams working out how to create a telehealth app quickly, or needing to prove demand before committing budget, start here. A ready-made telehealth solution covers the most critical features of virtual care out of the box:

The fork is real, and most teams should start on the left and migrate when the workflow stops fitting.
- user authentication
- scheduling
- video calling
- voice calling
- real-time chat
White-label components can trim your time to market from 9 months to 1-2 months, depending on the level of customization you need.
These components give you:
- A clean UI for both web and mobile platforms
- Compatibility across the components you already run
- Drop-in support for common stacks such as NodeJS, ReactJS and React Native
- Consistent and dependable performance at scale
- HIPAA compliance
- Encryption and data protection that hold up in a security review
- Quality control
- Features that meet the majority of user needs and match those of leading SaaS providers
- Fully customizable user experience and functionality
White-label telemedicine platforms are the fastest way to get to a real pilot, especially if you’re validating demand or need a working product before you invest in a fully custom build. The tradeoff is flexibility: once you need specialty workflows, deep integrations, or a differentiated patient experience, you may end up fighting the platform. Use the quick decision guide below to sanity-check which path fits your situation.
Decision guide: should you build custom or use white-label?
(Rule of thumb, exact breakpoints vary by specialty, integrations, and compliance scope.)
1) Do you need to launch in ≤ 60 days (pilot/MVP)?
→ Yes: Start with white-label
→ No: Go to #2
2) Annual patient visits under ~10,000?
→ Yes: White-label is often the fastest ROI path (validate demand and workflows first)
→ No: Go to #3
3) Do you need custom workflows? (e.g., specialty intake logic, triage/routing rules, care plans, role-based task queues, complex billing rules beyond standard scheduling + video)
→ Yes: Custom build is typically required
→ No: Go to #4
4) Do you need deep integrations now? (EHR/EMR, SSO, payer/eligibility, enterprise scheduling, device/RPM feeds)
→ Yes: Lean custom (or expect enterprise-grade white-label pricing + constraints)
→ No: Go to #5
5) Is your budget comfortable in the ~$150k+ range for v1? (Rule of thumb.)
→ Yes: Custom build for control and differentiation
→ No: Start with white-label, prove traction, then migrate to custom once requirements and ROI are clear
Rule-of-thumb cost note: White-label plans often start in the hundreds to low-thousands per month, but pricing can rise quickly with provider count, usage, integrations, security/compliance add-ons, and support tiers.
How much does it cost to build a telehealth app?
The cost of developing a telehealth app may vary from US$80,000 and all the way to US$349,000, depending on its complexity. Teladoc-like app development will easily run into millions of dollars because it’s a huge platform for virtually all platforms and lots of APIs.
Cost breakdown 2026 to develop a telehealth application
| Feature Set | Development Time | Cost Range | Monthly Maintenance |
|---|---|---|---|
| Basic MVP (video + chat) | 3–4 months | $80,000–$120,000 | $2,000–$3,000 |
| Standard (+ scheduling, payments) | 4–6 months | $120,000–$180,000 | $3,000–$5,000 |
| Advanced (+ EHR, RPM, AI) | 6–9 months | $180,000–$300,000 | $5,000–$8,000 |
| Enterprise (multi-platform) | 9–12 months | $300,000–$500,000 | $8,000–$15,000 |
On the lower end, we are talking cross-platform mobile apps that reuse as much as possible from a rather simple web telemedicine app. Also, remember that no-code telehealth app development is a perfect shortcut that saves a lot of money and expedites time to market. This approach will help you keep the telemedicine app development cost on a lower side.
And on the higher end, we mean an advanced web platform with native mobile apps built for smartphones and tablets. How long it takes to develop your app will depend on various factors like the features needed, cross platform vs native, where in the development stage you are and more.
Comparing approaches for creating a telehealth app
| Approach | Time to Launch | Total Cost Year 1 | Customization | Best For |
|---|---|---|---|---|
| Doxy.me white-label | 1–2 weeks | $20,000–$40,000 | Minimal | Quick launch |
| Custom React Native | 4–6 months | $150,000–$200,000 | Full | Unique features |
| Hybrid (APIs + custom) | 2–3 months | $80,000–$120,000 | Moderate | Balance |
| No-code platforms | 2–4 weeks | $10,000–$30,000 | Limited | Testing market |
For the line-by-line breakdown behind these two numbers, read cost to develop a telemedicine app.
Also read: The Health App Founder’s Dilemma: Achieving traction without over-investing

Two rows is all the budgeting most teams need, because the scope you pick sets the price and the calendar together.
Monetization strategies of a telehealth app
Knowing what it costs to build a telehealth app is half the equation. The other half is how the app earns its keep once it is live, and telehealth business profitability usually comes from stacking two or three of the four models below. The real question is which one leads, and in what order.

Most telehealth products stack two or three lanes, and the order they arrive in matters more than the mix.
Subscription models
Subscriptions are the default for direct-to-consumer telehealth (think mental health, weight-loss/GLP-1, men’s and women’s health verticals) and for B2B2C plays selling to employers or clinics on a per-seat basis.
- What works: predictable MRR, clean LTV math, lower support overhead per visit. Patients who convert tend to stick, especially in chronic-care categories.
- What to watch: CAC is brutal in crowded verticals, so your subscription has to include something more than “access to a doctor” (content, coaching, device loans, structured programs).
- Tiering that tends to convert: a lightweight $19–$39/mo tier for async messaging and one visit, then a $79–$149/mo tier that adds unlimited visits and/or RPM.
Per-visit fees
Plain cash-pay: patient pays $50–$150 per visit, you keep the margin. This is the fastest path to revenue when you’re creating a telemedicine app and haven’t yet negotiated payer contracts.
- What works: no insurance plumbing, no eligibility checks, no claims. If you’ve already connected Stripe for checkout, you’re done.
- What to watch: repeat rate. Per-visit without a subscription wrapper tends toward urgent-care economics: high-intent, low-frequency, expensive to re-acquire. Pair with a light membership to smooth revenue.
- Pricing reality: FAIR Health’s commercial claims data puts median telehealth allowed amounts around $24, and that’s insurance-reimbursed. Cash-pay prices run higher because you’re capturing the convenience premium directly.
Insurance integration revenue
The longest path, and the one with the biggest ceiling. You contract with commercial payers, Medicare, and/or Medicaid, bill claims (CPT codes for E&M visits, plus RPM codes like 99453/99454/99457 where applicable), and collect allowed amounts.
- What works: access to a much larger patient pool, and reimbursement that scales with volume without price-sensitivity pushback. RPM codes in particular yield $100–$180+ per patient per month on Medicare, which is real recurring revenue at scale.
- What to watch: payer contracting takes 6–18 months. You’ll need clean eligibility checks, claim scrubbing, denial management, and a billing ops function (in-house or outsourced to an RCM partner). Budget accordingly: this is an operations build as much as a software build.
- Sequence it right: most telehealth startups get to product-market fit on cash-pay or subscription first, then add insurance once utilization justifies the ops overhead.
Marketplace and add-on services
The fourth lane: revenue that rides alongside the clinical visit.
- E-prescriptions routed to partner pharmacies (mail-order, specialty, compounding), revenue share or fulfillment margin on the prescription itself.
- Lab orders through Quest/Labcorp/direct-access partners, referral fees or bundled pricing.
- Device sales or rentals: blood pressure cuffs, CGMs, pulse oximeters, scales. Either margin on the hardware or a rental stream that pairs with RPM billing.
- Content and program add-ons: coaching, structured courses, group sessions.
- Employer/clinic B2B licensing: sell the white-label or multi-tenant version of your stack to employers, clinics, or health systems.
Add-ons tend to be higher-margin than the visit itself and compound nicely with subscriptions. A DTC weight-loss telehealth app that sells the visit, the GLP-1 prescription fulfillment, and a structured coaching program is monetizing the same patient three ways, which is why those unit economics tend to work.
For teams adding pharmacy fulfillment as a revenue lane, working with a focused pharmaceutical app development company keeps eRx, eligibility, and partner integrations from becoming the bottleneck.
Related: How to build a GLP-1 virtual clinic, a worked example of stacking subscription, visit, RPM, and prescription-fulfillment revenue streams in one of telehealth’s fastest-growing verticals.
How Topflight fast-tracks telehealth app success
Telehealth now spans remote patient monitoring, computer-vision-powered rehab, and asynchronous consults that slot into a clinician’s day like email. Topflight has shipped that full spectrum, from RTHM’s long-COVID ecosystem that marries wearables with provider dashboards to Allheartz’s computer-vision RTM platform that cuts in-person check-ups by up to 50% and slashes clerical work 80%. We treat every telehealth build as a revenue engine, so founders reach proof-of-value before their runway blinks red.
More than $200 million in follow-on funding and acquisitions has landed in our clients’ bank accounts, showing that VCs reward apps that ship fast and clear the HIPAA, FDA, and payer gauntlets on day one.
Why telehealth teams pick Topflight
- Async & RPM ready-made – Video annotation, SMART-on-FHIR data pulls, and device integrations come as drop-ins, so you start clinical pilots in weeks.
- Computer-vision expertise – Pose-estimation models (MoveNet, TensorFlow) already battle-tested in production rehab workflows.
- Compliance baked in – End-to-end encryption, 2-factor auth, and PHI-safe cloud pipelines mean no “security tax” right before launch.
- Built-for-fundraising UX – The metrics that matter (reduced visits, injury prevention, provider time saved) are wired into dashboards from sprint one, arming you with investor-grade traction data.
Our experience developing telehealth apps
Telehealth is a category where the gap between “working demo” and “production-grade platform” is enormous, and bridging it is what we’ve spent the last decade doing. When founders first approach us to make a telehealth app, the questions they expect us to lead with (“which video SDK? which EHR?”) are rarely the ones that matter most. Compliance architecture, clinical workflow design, and scope sequencing are what separate a pilot from a platform. The projects below are a cross-section of real engagements: different budgets, different care models, different risk profiles.
AlgoRx: HIPAA-compliant telemedicine marketplace and EMR
AlgoRx needed a custom web platform combining a HIPAA-compliant EMR with a telemedicine marketplace, a build that required us to get the regulatory and clinical-workflow foundations right before layering on the consumer-facing experience. Within a month of MVP launch, AlgoRx was generating $100K in monthly revenue across 400+ orders, evidence that HIPAA-ready foundations and product velocity aren’t a tradeoff when the team knows where to spend time and where not to.
From AlgoRx’s CEO Jim Gibson in a verified Clutch review: “their team delivered a better project than what we were asking for” and “their knowledge has guided us in the right way to make good decisions.”
Subscription-based mobile telehealth platform (iOS + Android)
A telehealth startup engaged us to design and build a cross-platform mobile application for iOS and Android. The build spanned UX/UI, API integration, RevenueCat for subscription billing, AWS for HIPAA-ready hosting, and full deployment to both app stores. Mid-project scope evolution, a common reality when founders discover what their users actually want, required us to rebalance timeline and cost, and communicate openly about both.
In a verified Clutch review, the founder credited the team as “open, communicative, and worked diligently” even when scope changes extended the timeline. An honest picture of a mid-stakes telehealth build, including the parts that don’t go according to the original Gantt chart.
Web-based telehealth platform with patient-tracking dashboard
A San Francisco–based telehealth platform hired us for product discovery, UI/UX, and web-based application development. The result: a mobile-responsive React Native app that lets patients log daily symptoms, medications, and diet, feeding a provider-facing dashboard for trend analysis. This is the “chronic care meets RPM” workflow that’s become a core telehealth use case, and one of the clearest paths to recurring reimbursement via CPT RPM codes (covered earlier in this post).
The CEO’s verified Clutch review praised the team’s ability to “take apart complex functionality” and ship a strong v1, with a rigorous QA loop when early-stage bugs surfaced.
What these projects have in common
A few patterns show up across every telehealth engagement we’ve shipped:
- Compliance treated as architecture from sprint one. HIPAA-ready foundations (BAAs, encryption, audit logs, RBAC, MFA) are built from sprint one, not bolted on pre-launch. Retrofitting audit logs into a live PHI system is a special kind of pain.
- Scope is negotiated openly. Every build hits surprises. The difference is whether timeline and cost adjustments are surfaced transparently in the next standup or appear as a line item on an invoice three weeks later.
- Investor-grade metrics wired in early. Utilization, retention, time-to-care, no-show rates. Founders raising follow-on rounds don’t have to retrofit a measurement layer when the dashboards were already built against real events from day one.
Founders creating a telehealth app from scratch tend to learn the most from the first pattern; founders migrating off a white-label or rescuing a half-built project tend to care most about the third.
Time to make a telemedicine app
Now that you know how to build a telehealth app and what it costs, it’s time to custom build your app. At Topflight Apps, we specialize in building health apps for iOS, Android, and the web. We’ve helped dozens of founders make a telemedicine app that ships on schedule, on compliance, and on brand.
Do you have a telehealth app project? We’d like to help you with it. Explore our telemedicine website development services and get in touch here. We’re happy to help you build your own telemedicine application. Our telehealth app development services cover patient apps, provider portals and EHR connections.
Related Articles:
[Reviewed October 2026]
Frequently Asked Questions
What are the key distinctions between telehealth applications and telemedicine applications?
The terms are often used interchangeably, and most regulations (including HIPAA) don’t distinguish between them. The technical difference: telemedicine refers specifically to clinical activity delivered remotely (diagnosis, treatment, prescribing), while telehealth is the broader umbrella that also covers non-clinical services like remote patient monitoring, provider-to-provider consultation, patient education, and clinical training. In product terms, if you’re enabling virtual visits plus anything around them (RPM, messaging, education), you’re building a telehealth app; “telemedicine” is the subset focused strictly on the visit itself.
What does an average telemedicine app consist of?
Typically: a patient app (mobile or web), a clinician app (mobile or web), an admin console, and a secure back end with a database. The core stack usually also includes secure video or audio, messaging, scheduling, notifications, audit logging, and role-based access controls.
What is the minimum feature set for a telehealth MVP?
A practical MVP usually includes: patient onboarding and consent, provider profiles, appointment scheduling, secure video or audio visits, secure messaging, basic documentation notes, and an admin panel for user and content management. If you handle any PHI, include encryption in transit and at rest, access controls, and audit logs from day one.
How long does it take to develop a telemedicine app?
Whether you are working out how to make a telemedicine app for the first time or replacing a service you already run, most MVPs land in the 16-to-32-week range. That range depends on the scope of scheduling, payments, roles and permissions, and the complexity of the visit workflows. EHR integration, RPM device connectivity, and multi-location administration push toward the top of that range.
What drives telehealth development cost up the fastest?
The biggest multipliers are integrations and operational complexity: EHR connectivity, insurance and billing workflows, RPM devices and alerting, multi-tenant setups for multiple clinics, and advanced security controls with formal audits and documentation. Video is rarely the hard part; everything around the visit usually is.
Do I need FDA approval for my telehealth app?
It depends on intended use and on the claims you make. Software counts as a medical device when its intended use is diagnosis or treatment, and connecting to a device does not by itself make your app one. Our SaMD certification guide walks the line.
How long does HIPAA compliance add to development?
Plan about four weeks of HIPAA work inside the build. A formal security audit and its documentation is a separate track that adds six to eight weeks on top.
Can I use Zoom for telehealth?
Yes, on Zoom’s HIPAA-eligible healthcare plan with a signed BAA. Consumer Zoom carries no BAA, so it cannot handle PHI.
Can I develop a telehealth solution as a mobile app without a web component?
Yes, but most real-world deployments still need at least a lightweight web layer for administration (user management, content and settings, audit review, support workflows). Clinicians also often prefer a web view for documentation and back-office tasks, even if visits happen on mobile.
Can I develop a cross-platform telemedicine app?
Yes. Cross-platform can work well for many telehealth apps, especially when you prioritize speed and consistency across iOS and Android. The main watch-out is real-time media quality and device-level capabilities; if you need top-tier video performance, complex camera flows, or deep hardware usage, native builds are often safer.